
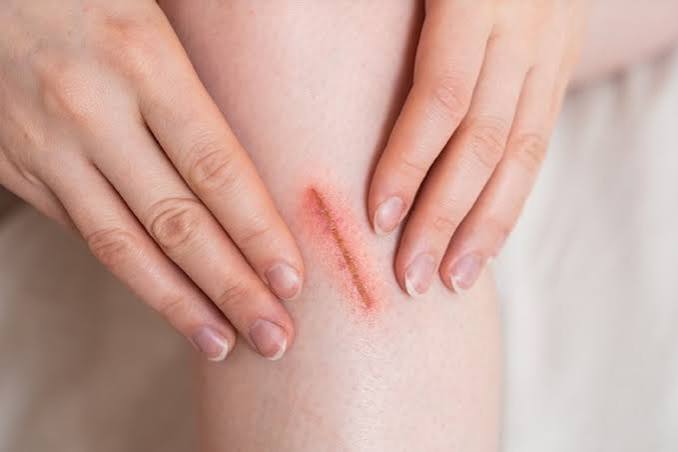
Slow wound healing is one of the most consequential and most visible manifestations of diabetes wound healing impairment — a problem that transforms minor injuries into medical emergencies and extends the recovery time from even routine surgical procedures. For adults without diabetes, a small skin laceration typically progresses through the four phases of wound healing — hemostasis, inflammation, proliferation, and remodeling — in 2–3 weeks. For adults with poorly controlled diabetes, the same wound may stall in the inflammatory phase, fail to develop adequate granulation tissue, remain open for months, and eventually become infected — creating the trajectory from minor injury to deep infection, osteomyelitis, and amputation that claims over 100,000 limbs annually in the United States. Diabetes wound healing is impaired not by a single defect but by the convergence of at least six simultaneous pathological processes — reduced blood flow, immune dysfunction, peripheral neuropathy, growth factor deficiency, collagen synthesis impairment, and a hyperglycemic wound environment that supports bacterial growth while suppressing tissue repair. Understanding each of these mechanisms, recognizing when a wound needs medical attention, and applying the evidence-based wound care practices that compensate for these defects is critical knowledge for every adult living with diabetes.
Approximately 15% of adults with diabetes will develop a chronic wound (typically a foot ulcer) during their lifetime. Diabetic foot ulcers account for more than 60% of all non-traumatic lower extremity amputations in the United States. Adults with a history of diabetic foot ulcer have a 5-year survival rate of approximately 50% — reflecting the severity of the underlying vascular and systemic disease. Even non-foot wounds heal more slowly in adults with diabetes: post-surgical wound complications (dehiscence, infection, delayed healing) are two to three times more common in adults with diabetes, and elective surgeries are frequently delayed when pre-operative A1C exceeds 8–8.5% because of the significantly elevated wound complication risk at higher glucose levels.
The Six Defects That Impair Wound Healing in Diabetes
Each of the following defects independently slows the diabetes wound healing process — and their simultaneous presence in adults with poorly controlled diabetes creates a wound environment in which the normal healing cascade is disrupted at every phase:
- Reduced tissue perfusion — oxygen and nutrient delivery failure: The proliferation phase of wound healing — in which fibroblasts migrate into the wound, produce collagen, and form new tissue — is absolutely dependent on adequate oxygen delivery. Fibroblast proliferation, collagen synthesis, and epithelial cell migration all require oxygen partial pressures above 30–40 mmHg in the peri-wound tissue. In adults with peripheral arterial disease (PAD) — which affects 20–30% of adults with long-standing diabetes — transcutaneous oxygen pressure (TcPO2) in the foot skin may fall below 20–30 mmHg, a level below which wound healing essentially cannot proceed. Even in adults with diabetes without frank PAD, microvascular disease (from the same capillary damage that causes retinopathy and nephropathy) reduces tissue perfusion at the capillary level — impairing oxygen and nutrient delivery despite patent larger vessels. This microvascular barrier to healing is one reason that many diabetic foot wounds fail to progress even after large vessel revascularization successfully restores macrovascular flow to the foot. The vascular assessment included in comprehensive diabetes care is covered in our annual diabetes care checklist.
- Immune dysfunction — chronic inflammation without resolution: In normal wound healing, the inflammatory phase (days 1–5) is characterized by neutrophil infiltration that clears bacteria and debris, followed by macrophage arrival that transitions the wound from debris clearance to healing promotion — releasing growth factors (PDGF, TGF-beta, EGF, VEGF) that stimulate fibroblast and epithelial cell migration. In diabetic wounds, this transition is disrupted: neutrophil function is impaired (as described in the context of diabetes and infections), macrophage polarization is abnormal (hyperglycemia skews macrophages toward the inflammatory M1 phenotype and away from the healing-promoting M2 phenotype), and the protease burden in the wound (particularly matrix metalloproteinases — MMPs) is dramatically elevated. The high MMP levels in chronic diabetic wounds degrade the growth factors and extracellular matrix proteins that are being produced, creating a futile cycle in which healing signals are generated but immediately destroyed. This is why chronic diabetic wounds are characterized by elevated MMP levels and reduced growth factor activity — both mechanistically explaining their chronicity and pointing toward therapeutic targets (MMP inhibitors, exogenous growth factor application).
- Peripheral neuropathy — the wound the person cannot feel: Neuropathy contributes to diabetes wound healing impairment in two distinct ways. First, loss of protective sensation prevents the behavioral responses that would normally protect an injured area from further trauma — a person with sensory neuropathy continues to walk on a developing foot ulcer, applying thousands of pounds of cumulative plantar pressure that disrupts the wound bed, prevents granulation tissue from forming, and mechanically re-injures the healing margin with every step. Second, autonomic neuropathy affects the neurovascular control of blood flow to the skin — in the healthy wound, local vasodilation (mediated by neuropeptides released by sensory nerve endings — substance P, CGRP) increases blood flow to the healing wound. This neurogenic vasodilation is absent in autonomic neuropathy, reducing the wound’s ability to regulate its own blood supply. The denervated wound also produces fewer neuropeptides that stimulate keratinocyte migration and fibroblast proliferation — creating a “neuropathic wound” phenotype with flat wound margins, reduced fibroblast activity, and impaired epithelialization. Our diabetic neuropathy guide covers the neurological mechanisms underlying wound healing impairment.
- Growth factor deficiency and receptor resistance: Wound healing is orchestrated by a complex network of growth factors — PDGF (platelet-derived growth factor), TGF-beta (transforming growth factor beta), EGF (epidermal growth factor), VEGF (vascular endothelial growth factor), IGF-1 (insulin-like growth factor 1), and FGF (fibroblast growth factor) — each of which directs specific healing processes. In adults with diabetes, several of these growth factors are produced in reduced quantities, are degraded more rapidly (by elevated MMPs), and face receptor resistance in target cells (similar to the insulin receptor resistance in Type 2 diabetes). VEGF — the primary driver of new blood vessel formation (angiogenesis) needed to vascularize healing tissue — is particularly important: in the non-ischemic wound, hypoxia stimulates VEGF production which drives new capillary ingrowth into the granulating wound. In the hyperglycemic wound environment, VEGF response to hypoxia is paradoxically blunted despite chronic tissue ischemia — a phenomenon called “angiogenesis impairment in diabetes” that directly explains the poor vascularization of chronic diabetic wounds. Becaplermin (REGRANEX) — recombinant PDGF-BB — is the only FDA-approved growth factor for diabetic wound healing, demonstrating 43% higher incidence of complete wound closure compared with placebo in randomized trials for neuropathic diabetic foot ulcers.
- Collagen synthesis and remodeling defects: The strength and structural integrity of the repaired wound depend on collagen — primarily type I collagen synthesized by fibroblasts and crosslinked into organized fibrils by lysyl oxidase. In adults with diabetes, fibroblast collagen production is reduced because: hyperglycemia impairs fibroblast proliferation and migration (the cells that produce collagen); AGE-modified collagen molecules crosslink abnormally, producing disorganized matrix that lacks the tensile strength of normal collagen; and elevated MMP activity degrades newly synthesized collagen before it can be incorporated into the wound matrix. The result is a healed wound with significantly lower tensile strength than a wound healed in a non-diabetic individual — increasing the risk of wound breakdown (dehiscence) after surgical wound closure and explaining the higher rates of incisional hernia and fascial dehiscence in surgical patients with poorly controlled diabetes. Vitamin C (ascorbic acid) is an essential cofactor for the hydroxylation steps of collagen synthesis — its deficiency (which can occur in adults with diabetes who have poor dietary habits) further impairs collagen cross-linking and wound strength.
- Hyperglycemia as a direct wound toxin — creating a growth medium for bacteria: The wound environment in adults with poorly controlled diabetes is rich in glucose — wound fluid glucose concentrations correlate with blood glucose levels. This glucose-rich wound environment provides an ideal growth medium for bacteria: Staphylococcus aureus, Pseudomonas aeruginosa, and anaerobic organisms grow exponentially faster in high-glucose conditions than in normoglycemic wound fluid. Hyperglycemia also directly impairs keratinocyte migration (the epithelial cells that resurface the wound), reduces keratinocyte proliferation, and impairs the formation of the migrating epithelial sheet that covers the wound surface. Each 1% reduction in A1C significantly reduces the bacterial burden in chronic diabetic wounds and accelerates epithelialization. The A1C monitoring schedule fundamental to wound healing support is in our A1C testing schedule guide. The NIDDK’s diabetic wound and foot problems information and the CDC’s diabetes wound care resources provide authoritative clinical guidance on wound healing management in adults with diabetes.
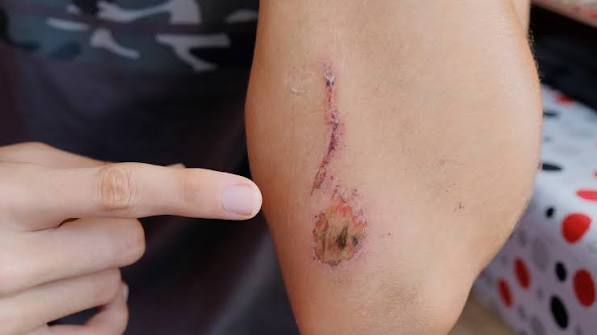
Wound Care Principles That Support Healing in Adults With Diabetes
Effective wound care in adults with diabetes compensates for the multiple healing defects described above through a combination of wound bed preparation, infection management, offloading, and systemic metabolic optimization:
- Wound bed preparation — the foundation of effective wound care: The concept of wound bed preparation — creating the optimal wound environment for healing — encompasses four domains captured by the TIME acronym: T — Tissue (removal of devitalized tissue through debridement); I — Infection/Inflammation (identification and aggressive treatment of wound infection, and management of chronic wound inflammation); M — Moisture imbalance (maintaining a moist wound environment to support cell migration while removing excess exudate that inactivates growth factors); E — Edge (the wound edge advancement, or lack thereof, that indicates whether healing is progressing). In diabetic wounds, tissue debridement is particularly important: devitalized, hyperkeratotic wound edges and wound base material harbor bacteria, contain the elevated MMPs that degrade healing signals, and physically impede epithelial cell migration. Sharp surgical debridement (using a scalpel or curette to excise necrotic and fibrinous material) is the most effective debridement method, and diabetic wounds typically require serial debridement (every 1–2 weeks in active wound care) rather than a single initial debridement. Our diabetic foot problems guide covers wound assessment and wound care techniques in detail.
- Infection management — distinguishing contamination from infection: All chronic wounds are colonized with bacteria (presence of bacteria without tissue invasion or host response), but not all colonized wounds are infected (bacteria invading tissue and eliciting a host immune response). Treating colonized wounds with systemic antibiotics is not only ineffective but promotes antibiotic resistance — yet failing to treat true wound infection allows the infection to spread and prevents healing. Signs of true wound infection in a diabetic foot wound include: increased warmth, erythema, or edema around the wound; purulent (pus-containing) exudate; increased pain in wounds that were previously non-painful; foul odor; new or worsening systemic signs (fever, elevated white count, elevated CRP); and failure to reduce in size by 50% after 4 weeks of optimal wound care. When infection is present, antibiotic selection should be based on wound culture (swab culture is less reliable than tissue biopsy culture for deep infections) and continued for the minimum duration that achieves clinical resolution — extended antibiotic courses beyond infection clearance do not improve wound healing and promote resistance. The cholesterol management relevant to wound healing — because hyperlipidemia impairs endothelial function in healing wounds — is in our cholesterol monitoring guide.
- Moisture management and wound dressings: The wound dressing selection in diabetic wound care is guided by wound characteristics: exudate level, depth, infection status, and peri-wound skin fragility. The moist wound healing environment — first established by George Winter’s landmark 1962 experiments showing that epithelialization occurred twice as fast under moist occlusive dressings as under dry ones — remains the foundational principle. Highly exudative wounds require absorbent dressings (foam dressings, alginate dressings, hydrofiber dressings) that remove excess exudate without desiccating the wound. Dry or minimally exudative wounds require moisture-donating dressings (hydrogels, hydrocolloids) that maintain the moist environment needed for cell migration. Wounds at high infection risk may benefit from dressings containing antimicrobial agents — silver-containing dressings reduce bacterial biofilm and have shown benefits in infected diabetic wounds, though evidence for their superiority over standard dressings in non-infected wounds is limited. Dressing changes should occur at the minimum frequency needed to maintain an optimal wound environment — excessive dressing changes disrupt healing tissue and cause thermal cooling of the wound bed that impairs cell function. The blood pressure monitoring relevant to perfusion-supported wound healing is in our blood pressure monitoring guide. The ADA’s foot and wound complication resources provide additional clinical guidance on wound care in adults with diabetes.
When a Wound Requires Immediate Medical Attention
Adults with diabetes should seek prompt medical evaluation for any wound that meets the following criteria — delaying evaluation of these warning signs significantly increases the risk of deep tissue infection, osteomyelitis, and amputation:
- Wounds that do not begin healing within 2–4 weeks: Any wound in an adult with diabetes that has not reduced in size by at least 30–50% after 4 weeks of optimal wound care (appropriate dressing, offloading, glucose control, and infection management) should be evaluated by a wound care specialist or podiatrist for more advanced interventions. A wound that is not progressing may have unrecognized osteomyelitis, inadequate blood flow requiring vascular assessment, or occult infection requiring wound culture and antibiotic adjustment. Remaining on the same wound care regimen for months without progress — while the wound gradually deepens or develops periwound cellulitis — is the pattern that most commonly precedes amputation. The 4-week failure threshold is internationally recognized in diabetic wound care guidelines as the point at which the care approach must change.
- Any wound with spreading redness, warmth, or swelling: Cellulitis spreading beyond the immediate wound margin — particularly if accompanied by red streaking (lymphangitis), new fever, or systemic symptoms — represents invasive soft tissue infection requiring immediate medical evaluation and likely IV antibiotics. Adults with diabetic neuropathy may not experience increasing pain as the infection spreads, making visual inspection of the peri-wound skin the critical early warning system. Any adult with diabetes who notices that the redness around a wound is larger than it was yesterday requires same-day medical evaluation — not next-week evaluation. Adults with diabetes who have diabetic foot wounds and who feel unwell (even without specific localizing symptoms) should have their wound evaluated promptly, because systemic sepsis from a foot infection can develop before local signs are dramatic.
- Wounds reaching bone, tendon, or joint: Any wound deep enough to probe bone, feel tendon, or reach a joint space is a surgical emergency — osteomyelitis (bone infection) is highly probable, and joint involvement (septic arthritis) is a limb-threatening emergency requiring immediate surgical drainage. The probe-to-bone test — inserting a sterile blunt-tipped probe into the wound base — has a positive predictive value of 89% for osteomyelitis when the probe contacts bone directly. MRI is the most sensitive and specific imaging test for osteomyelitis in diabetic foot wounds and should be obtained whenever deep infection is suspected. The comprehensive annual diabetes monitoring that supports wound prevention through vascular and neuropathy assessment is in our annual diabetes care checklist. The NIDDK’s diabetic wound care information covers the full spectrum of wound recognition and treatment guidance for adults with diabetes.
Advanced Wound Therapies and Blood Sugar Control During Wound Healing
When standard wound care does not produce measurable progress within 4 weeks, advanced wound therapies can accelerate diabetes wound healing in wounds that would otherwise progress to amputation. The selection of advanced therapy depends on wound characteristics, vascular status, and infection control:
- Negative pressure wound therapy (NPWT — wound VAC): NPWT applies continuous or intermittent sub-atmospheric pressure (typically -75 to -125 mmHg) to the wound bed via a foam dressing and sealed adhesive drape connected to a vacuum pump. The mechanical action removes excess exudate, reduces wound edema, mechanically stimulates granulation tissue formation, and draws wound edges toward the center — accelerating wound bed preparation and facilitating subsequent skin grafting or flap closure. NPWT is particularly effective for deep diabetic foot wounds following surgical debridement and for post-amputation stumps in which the wound cannot be closed primarily. The ADA and Society for Vascular Surgery both include NPWT in their guidelines for managing complex diabetic foot wounds that have not responded to conventional wound care. NPWT requires frequent wound assessments (every 48–72 hours during active treatment) and should not be used on wounds with untreated osteomyelitis or in wounds with poor wound bed vascularity below the level needed to support granulation tissue formation.
- Aggressive blood glucose management as the primary wound intervention: Achieving normoglycemia during the wound healing period is the single most impactful intervention available for accelerating diabetes wound healing — more impactful than any topical dressing, growth factor application, or advanced therapy. Research from surgical wound healing has demonstrated that maintaining postoperative blood glucose below 150–180 mg/dL reduces surgical site infection rates by approximately 50–60% in adults with diabetes. The mechanism is direct: each reduction in ambient glucose reduces the hyperglycemic wound environment that impairs keratinocyte migration, promotes bacterial growth, and degrades growth factors. Adults with chronic diabetic foot wounds who achieve A1C below 8% close their wounds at significantly higher rates than those with A1C above 9%. For adults with active wounds, glucose management should be escalated — including insulin initiation if needed — rather than accepting habitual glycemic control that was adequate before the wound developed. Our A1C testing schedule guide covers the monitoring framework that supports wound healing glucose targets. The blood pressure control relevant to vascular perfusion during wound healing is in our blood pressure monitoring guide.
Sources: American Diabetes Association — Standards of Medical Care in Diabetes, wound care and foot complications; NIDDK — diabetic wound healing and foot problem prevention; CDC — diabetes foot and wound care statistics; ADA — foot and wound complication clinical resources; wound healing phases in diabetes — hemostasis, inflammation, proliferation, remodeling disruption; neutrophil dysfunction and M1 macrophage polarization in diabetic wounds; matrix metalloproteinase (MMP) elevation and growth factor degradation in chronic diabetic wounds; VEGF impairment and angiogenesis defects in diabetic wounds; becaplermin (recombinant PDGF-BB) — 43% higher wound closure rate in randomized trial; collagen synthesis defects — AGE cross-linking, fibroblast impairment, lysyl oxidase dysfunction; peripheral arterial disease transcutaneous oxygen pressure (TcPO2) below 30 mmHg and wound healing threshold; neurogenic vasodilation impairment in autonomic neuropathy and wound blood flow; keratinocyte migration impairment by hyperglycemia; wound infection vs. colonization distinction — IDSA diabetic foot infection classification; TIME wound bed preparation framework; moist wound healing — George Winter 1962 epithelialization study; silver dressing evidence in infected diabetic wounds; probe-to-bone test positive predictive value 89% for osteomyelitis; MRI sensitivity and specificity for osteomyelitis in diabetic foot; elective surgery wound complication risk at A1C above 8–8.5%; post-surgical dehiscence two to three times higher in adults with diabetes; 4-week wound healing threshold for advanced intervention referral; wound biofilm and antibiotic resistance in chronic diabetic wounds; A1C reduction and bacterial burden in diabetic wounds.
I shared this article on diabetes and wound healing with my doctor and they appreciated the level of detail. The practical tips made this immediately actionable, not just theoretical. Appreciate the effort that went into researching and writing this — it shows.
As someone dealing with this personally, the diabetes and wound healing section was very helpful. I especially valued the explanation of why these recommendations exist, not just what they are. This is going into my health folder that I bring to every doctor’s visit.
Came across this while researching diabetes and wound healing for a family member. This is the kind of evidence-based writing that actually changes how people approach their health. Shared this with three friends who are dealing with related issues. Very useful resource.