
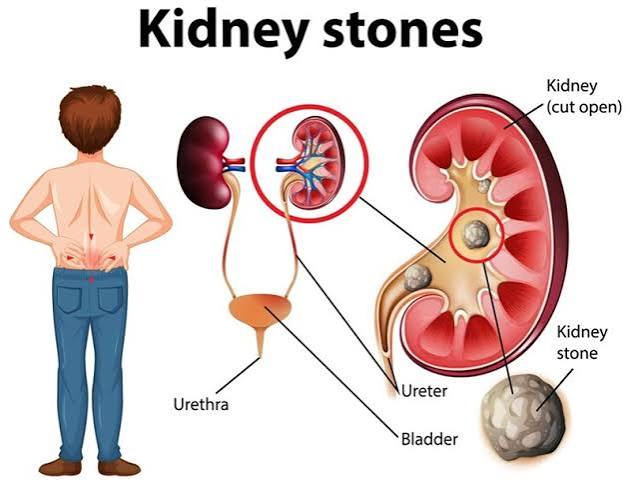
Receiving a diagnosis of Stage 5 chronic kidney disease — or being told that your eGFR has dropped below 15 — is one of the most significant moments in a patient’s medical journey. Numbers on a lab report can feel abstract, but Stage 5 CKD, also called kidney failure or end-stage kidney disease (ESKD), means that the kidneys are functioning at less than 15 percent of their normal capacity. At this level, the kidneys can no longer maintain the chemical balance the body needs without external help. What that external help looks like — dialysis, a transplant, or a different path entirely — is a decision that requires understanding, time, and active preparation. This guide explains what Stage 5 means in practical terms: what symptoms to expect, what treatment options exist, how to prepare before a crisis develops, and what questions to bring to your nephrologist at every appointment.
What Stage 5 CKD Actually Means
Stage 5 is defined by an estimated glomerular filtration rate (eGFR) below 15 ml/min/1.73m². The eGFR measures how well the kidneys filter waste from the blood each minute, adjusted for body size. A healthy young adult has an eGFR above 90. At Stage 5, the filtration capacity has fallen so low that the kidneys can no longer remove the waste products, excess fluid, and electrolytes that accumulate from normal body function. The medical term end-stage renal disease (ESRD) or end-stage kidney disease (ESKD) is used interchangeably with Stage G5, though ESRD technically includes patients already receiving dialysis — sometimes designated G5D in research literature.
A common misconception is that dialysis begins automatically when the eGFR hits 15. It does not. The decision to start dialysis is made based on symptom burden — not on a specific eGFR number. The landmark IDEAL trial, published in 2010, compared early dialysis initiation (eGFR 10–14) versus later initiation (eGFR 5–7) and found no survival advantage to starting early. The current KDIGO guideline position is clear: dialysis is started when the patient has significant symptoms impairing quality of life, or when a medical emergency arises — not at a fixed eGFR threshold. This distinction matters because it means that reaching an eGFR of 10 does not mean dialysis starts tomorrow. It means symptom management and preparation become the priority.
The kidneys perform several critical functions simultaneously: filtering waste, regulating fluid volume, controlling electrolyte levels (potassium, sodium, phosphate, bicarbonate), producing erythropoietin (the hormone that stimulates red blood cell production), and activating vitamin D. At Stage 5, all of these functions are severely impaired. The clinical picture is dominated by the accumulation of uremic toxins — compounds that healthy kidneys excrete — and by the loss of the kidneys’ hormonal and regulatory roles. Understanding this multisystem impact helps patients make sense of why their symptom list at Stage 5 is so broad.
Symptoms Patients Experience at Stage 5
The syndrome caused by kidney failure-level waste accumulation is called uremia. Uremic symptoms affect virtually every organ system and represent the clearest signal that the kidneys’ filtration capacity has been overwhelmed. The particular combination and severity of symptoms varies between patients, but several are nearly universal at Stage G5.
Fatigue and anemia are among the most disabling symptoms at Stage 5. The kidneys produce erythropoietin, which signals the bone marrow to make red blood cells. At G5, erythropoietin production is near zero, and uremic toxins additionally suppress bone marrow response. Hemoglobin levels commonly fall to 7–9 g/dL without treatment — low enough to cause severe fatigue, shortness of breath with minimal activity, and impaired cognitive function. Treatment with erythropoiesis-stimulating agents (ESAs) such as darbepoetin or epoetin, combined with intravenous iron supplementation, is standard; the target hemoglobin is 10–11.5 g/dL. Many patients note that anemia management is the single intervention most immediately affecting their quality of life.
Nausea, vomiting, and appetite loss are driven by uremic gastroenteropathy. Urea, which accumulates when kidneys fail to excrete it, is converted by gut bacteria into ammonia — causing the characteristic metallic or ammonia-like taste many Stage 5 patients describe. Nausea may be constant rather than intermittent. Weight loss and muscle wasting occur because patients eat less while metabolic demands remain high; uremic catabolism further accelerates muscle breakdown. Dietitian support focusing on high-quality protein intake and managing electrolyte restrictions is critical at this stage.
Fluid overload and swelling affect most Stage 5 patients to some degree. When kidneys cannot excrete water adequately, fluid accumulates in the legs, ankles, abdomen, and — in serious cases — the lungs. High doses of loop diuretics (furosemide, torasemide) are used to manage fluid volume, but their efficacy diminishes as kidney function falls. Strict sodium and fluid restriction becomes essential.
Neurological symptoms at Stage 5 include impaired concentration and memory (uremic encephalopathy in mild forms), peripheral neuropathy (numbness and tingling in the hands and feet from uremic nerve damage), and restless legs syndrome. Restless legs — the irresistible urge to move the legs, especially at night — affects a large proportion of advanced CKD patients and is one of the most quality-of-life-impairing symptoms, often interfering severely with sleep. It is treated with gabapentin (at reduced doses for kidney function), dopamine agonists, or iron supplementation when iron stores are low.
Uremic pruritus — severe itching without a rash — affects 40 to 70 percent of patients at Stage 5 and on dialysis. Its mechanism involves κ-opioid receptor activation by uremic toxins, and it can be debilitating. Treatment options include difelikefalin (FDA-approved in 2021 for dialysis patients; given intravenously), nalbuphine ER, and gabapentin. The intensity of pruritus often prompts patients to question whether dialysis will provide relief — and in many cases it does improve with effective dialysis.
Uremic pericarditis deserves special attention as a cardiac emergency at Stage 5. This is inflammation of the membrane surrounding the heart, caused directly by uremic toxin accumulation. Symptoms include chest pain that worsens when lying flat and improves leaning forward, and a characteristic pericardial friction rub heard on auscultation. Uremic pericarditis is a classical indication for urgent dialysis initiation — it should not be managed with watchful waiting. Any Stage 5 patient experiencing chest pain should contact their nephrologist the same day.
Kidney Replacement Therapy: Understanding Your Options
When dialysis becomes necessary, or when patients are evaluating their options before that point, the four pathways are hemodialysis, peritoneal dialysis, kidney transplant, and conservative kidney management. No single option is universally best — the right choice depends on the patient’s age, comorbidities, support system, lifestyle priorities, and values. Understanding each option in detail, ideally well before reaching the crisis point, allows for a genuinely informed decision.
Hemodialysis (HD) is the most common form of kidney replacement therapy in the United States. Blood is removed from the body through vascular access, passed through a dialysis machine that filters waste and excess fluid, and returned to the body. Standard in-center HD runs three sessions per week, typically three to four hours each. Vascular access for HD requires creation of an arteriovenous (AV) fistula — a connection between an artery and vein in the arm that develops into a robust, high-flow vessel suitable for repeated needle access. AV fistulas require three to six months to mature and are the preferred access type because of their lower complication rate compared to AV grafts and tunneled catheters. Home hemodialysis — performed five to six times per week — is associated with better blood pressure control, fewer hospitalizations, and improved quality of life compared to in-center three-times-weekly HD, and is an option worth exploring for motivated patients with a capable caregiver at home.
Peritoneal dialysis (PD) uses the lining of the abdominal cavity (the peritoneum) as a natural filter. Dialysis fluid is instilled into the abdomen through a surgically placed soft catheter, dwells for a set period while waste diffuses across the peritoneal membrane, and then drains. Continuous ambulatory peritoneal dialysis (CAPD) involves four manual exchanges per day. Automated peritoneal dialysis (APD) uses a cycling machine overnight while the patient sleeps, leaving the daytime largely free. PD allows patients to manage their treatment at home, maintain greater dietary flexibility, and preserve residual kidney function longer than hemodialysis. It is particularly well-suited to patients who value independence and want to avoid three-times-weekly travel to a dialysis center.
Kidney transplant offers the best long-term outcomes of all kidney replacement therapy options. A functioning transplanted kidney provides continuous, 24-hour filtration — far superior to the intermittent nature of dialysis. Ten-year graft survival rates are 60 to 70 percent for deceased-donor kidneys and 70 to 80 percent for living-donor kidneys. Pre-emptive transplantation — receiving a kidney before starting dialysis — produces the best outcomes and should be the goal whenever a living donor is available. For deceased-donor transplant, patients must be listed before crisis; UNOS policy allows waitlist registration when eGFR falls to 20 or below, and time on the waitlist counts from registration. Living donor evaluation typically takes three to six months and should begin as early as possible — ideally at Stage G4. Transplant recipients require lifelong immunosuppression (standard regimen: tacrolimus + mycophenolate + low-dose prednisone), which carries risks of infection, certain cancers, and the metabolic effects of corticosteroids, but for most patients these are substantially outweighed by the quality of life and survival benefits compared to dialysis.
Conservative kidney management (CKM) is the path that focuses on symptom relief and quality of life without pursuing dialysis. It is appropriate for a subset of patients — typically older individuals with significant additional health conditions such as advanced heart failure, dementia, or metastatic cancer — for whom dialysis would impose significant burden without meaningful life extension or quality of life benefit. Conservative kidney management is not giving up; it is an active care plan that includes aggressive symptom management, palliative nephrology, advance care planning, and often hospice coordination. It is increasingly recognized in nephrology literature as a valid, dignity-preserving choice that deserves the same weight as dialysis options in shared decision-making conversations. Patients considering CKM benefit greatly from early conversations with both their nephrologist and a palliative care team.
How to Prepare for Dialysis Before It Starts
The patients who navigate Stage 5 with the least crisis are those who prepared for kidney replacement therapy before it became urgent. Planning ahead requires understanding the timelines involved in access creation and transplant evaluation, and acting on them well before an emergency forces a rushed decision.
For hemodialysis, vascular access planning is the critical preparation step. An AV fistula — the gold standard — requires a surgeon to connect an artery and vein, then three to six months of maturation time before it can be used for dialysis. If a patient is at eGFR 15 today and is expected to need dialysis within six to twelve months, fistula creation should be discussed immediately. Starting dialysis with a tunneled central venous catheter — the backup access when no mature fistula is available — is associated with significantly higher rates of infection, hospitalization, and mortality. The urgency of fistula timing is one of the most important practical preparation messages at Stage G5.
For peritoneal dialysis, a PD catheter is placed surgically or laparoscopically and requires approximately two weeks of healing before use. PD training — learning to perform exchanges safely at home — typically takes one to two weeks. The lead time for PD is shorter than for HD fistula creation, but still requires advance planning.
For transplant, the preparation timelines are the longest. Deceased-donor waitlist registration should occur at eGFR 20 or below, since time on the waitlist accrues from registration. Complete transplant evaluation — cardiac testing, infectious disease screening, cancer screening, psychosocial evaluation — can take several months. Living donor evaluation for a family member or friend typically takes three to six months. Every month of delay in beginning this process is a month of potential dialysis time that might otherwise have been avoided through pre-emptive transplant. Patients at Stage G4 or early G5 with willing potential living donors should initiate the conversation with their transplant center immediately. A detailed walkthrough of what monitoring and preparation look like across earlier CKD stages is in our overview of chronic kidney disease stages explained.
Managing Stage 5 Before Dialysis Begins
The period between reaching eGFR 15 and actually starting dialysis can span weeks to over a year, depending on symptom burden and the rate of kidney function decline. During this interval, medical management focuses on controlling the complications of near-total kidney failure while delaying dialysis start as long as symptoms permit and preparing access.
Anemia is managed with ESA injections (darbepoetin alfa or epoetin alfa) plus intravenous iron, since oral iron is poorly absorbed in advanced CKD. The hemoglobin target is 10 to 11.5 g/dL — enough to relieve symptoms without the higher cardiovascular risk associated with targeting a normal hemoglobin of 13–14 g/dL.
Metabolic acidosis becomes increasingly difficult to control at Stage 5 as bicarbonate production capacity is essentially lost. Oral sodium bicarbonate in increasing doses is used, but its efficacy decreases as kidney function falls further. Untreated acidosis accelerates muscle protein catabolism and worsens bone disease, so maintaining serum bicarbonate above 22 mEq/L remains an active treatment goal even at G5.
Hyperkalemia is managed with potassium binders (patiromer or sodium zirconium cyclosilicate, taken daily) and strict dietary potassium restriction to under 2 grams per day. Potassium binders allow patients to continue ACE inhibitors and ARBs — which remain kidney-protective even at G5 — despite the hyperkalemia risk. This is generally preferable to stopping RAAS agents, which would accelerate blood pressure deterioration and proteinuria.
Fluid overload is managed with high-dose furosemide — sometimes 160 to 320 mg per day — combined with sodium restriction to under 2 grams per day and fluid restriction. When diuretics become ineffective, dialysis may need to begin for fluid management alone, even if other symptoms are not yet severe.
Secondary hyperparathyroidism and bone disease (CKD-MBD) at Stage 5 requires phosphate binders (calcium-based or non-calcium-based, taken with meals), active vitamin D analogs (calcitriol or paricalcitol), and in some cases cinacalcet to suppress parathyroid hormone. Uncontrolled CKD-MBD contributes to vascular calcification and cardiovascular risk — one of the leading causes of death in CKD patients.
Monitoring at Stage G5 is intensive. Lab tests — eGFR, electrolytes, bicarbonate, CBC, iron studies, PTH, phosphate, calcium — typically occur every one to two months. Nutritional assessment by a renal dietitian is conducted every one to three months because malnutrition is a significant independent risk factor for mortality in Stage 5 patients. The detailed checklist of what is monitored and when is outlined in our annual kidney health checklist guide.
Urgent Symptoms That Require Immediate Medical Attention
Most symptom management at Stage 5 is handled at scheduled appointments. However, several situations require same-day contact with a nephrologist or an emergency department visit, because they represent conditions where urgent or emergent dialysis initiation is the treatment:
- Uremic pericarditis: Chest pain that worsens lying down and improves leaning forward, potentially with a fever. This is a dialysis emergency — do not wait for the next appointment.
- Severe confusion, altered consciousness, or seizure: Uremic encephalopathy from extreme toxin accumulation. Requires urgent evaluation and usually emergent dialysis.
- Severe hyperkalemia (potassium >6.5 mEq/L): Unresponsive to home potassium binders; risk of life-threatening cardiac arrhythmia. Requires emergency management.
- Severe fluid overload: Difficulty breathing at rest or with minimal exertion, particularly if this represents a change from baseline. Pulmonary edema is a dialysis indication.
- Uremic bleeding: Unexplained nosebleed, GI bleeding, or easy bruising from platelet dysfunction. Requires urgent evaluation.
Stage 5 patients and their caregivers benefit enormously from knowing in advance which symptoms to watch for and who to call. Asking the nephrology team for explicit guidance on when to call versus when to go to the emergency department is a conversation worth having at every Stage 5 appointment. The question template in our guide on questions to ask during a kidney checkup includes prompts for exactly this discussion.
Emotional and Practical Aspects of Kidney Failure
The emotional impact of a Stage 5 diagnosis is real and deserves acknowledgment alongside the medical logistics. Grief, fear, uncertainty about the future, and anxiety about becoming dependent on a machine or on family members are normal responses — not signs of weakness or poor adjustment. Patients frequently describe a mourning process for the life they anticipated and the independence they may need to modify. This is a legitimate psychological response to a significant loss, and it is worth addressing directly with the care team.
Building a multidisciplinary care team at Stage 5 is practical as well as important. The core team includes the nephrologist, a renal dietitian, and ideally a social worker who is familiar with the insurance, transportation, and family support challenges that dialysis creates. Many advanced CKD programs now include a palliative care team member as well — not as a signal that death is imminent, but because palliative care specializes in exactly the symptom management, decision support, and advance care planning that Stage 5 patients need regardless of which treatment path they choose.
Advance directives — legal documents that specify what medical interventions a patient wants or does not want if they are unable to communicate — become urgently important at Stage 5. These include a durable power of attorney for health care (identifying who makes decisions if the patient cannot) and a living will or POLST form (specifying preferences around CPR, mechanical ventilation, and dialysis continuation). Having these documents in place before a crisis protects patient autonomy and spares family members from impossible decisions. Many nephrology practices can connect patients with social workers who help complete these documents.
For patients exploring living donation, family conversations about the possibility are best started early. The evaluation process is lengthy, and donors need time to understand what they are committing to — including a six-week recovery and the lifelong requirement for their own kidney function monitoring. Organizations like the National Kidney Foundation and the American Kidney Fund provide resources for patients and potential donors navigating this decision.
What to Ask Your Nephrologist at Stage 5
The appointments at Stage 5 carry significant weight, and arriving prepared with specific questions helps ensure that the most important decisions are addressed rather than deferred. Key questions at Stage G5 appointments include:
- Based on my current eGFR decline rate, when do you estimate I will need to start dialysis?
- Am I eligible for transplant evaluation now, and how do I get referred to a transplant center?
- Should I schedule access surgery (fistula or PD catheter) now, and with whom?
- If I am interested in home dialysis (home HD or PD), what is the process for evaluating that option?
- What specific symptoms should prompt me to call today rather than waiting for my next appointment?
- What does conservative kidney management look like for patients in my situation, and who would I speak with to understand it better?
- Are my current medications still appropriate at this kidney function level?
These questions signal active engagement and often unlock more thorough conversations than a passive appointment allows. The complete framework for what information to gather at each stage of CKD — from lab target questions to medication review questions — is in the companion guide on Stage 4 kidney disease: what to expect, which covers the preparation steps ideally completed before reaching G5.
A Note on Living Well With Stage 5 CKD
Stage 5 kidney disease is a serious medical condition that requires major life adjustments and significant medical management. It is also a stage that many thousands of patients navigate successfully for years — on dialysis, post-transplant, or through careful conservative management — with maintained dignity, meaningful relationships, and considerable quality of life. The key distinction between patients who feel overwhelmed and patients who feel prepared is almost always the depth of their understanding of their options, the quality of their care team, and the degree to which they made decisions proactively rather than reactively.
The medical framework at Stage 5 is demanding but navigable: manage your complications actively, prepare your access or transplant pathway before crisis forces the decision, attend every monitoring appointment, and engage your nephrology team with specific questions at every visit. The full range of what tests, medications, and checkup items should be reviewed at each stage of CKD is covered in our guide to how doctors diagnose kidney disease, which explains what each measurement means and why it is tracked. The NIDDK’s kidney failure resource page provides additional information on treatment options directly from the National Institutes of Health.
Sources: National Institute of Diabetes and Digestive and Kidney Diseases (NIDDK); KDIGO 2024 CKD Guidelines; National Kidney Foundation; American Kidney Fund; Cooper BA et al., IDEAL Trial, NEJM 2010.
Came across this while researching stage 5 kidney disease: what patients for a family member. I appreciated how the article addressed both the clinical side and the practical adjustments. Exactly the kind of evidence-based information that is hard to find in one place.
Bookmarked this article on stage 5 kidney disease: what patients immediately — going to reference it regularly. I appreciated how the article addressed both the clinical side and the practical adjustments. This is exactly why I prefer this website over generic health platforms.
Really well-written article on stage 5 kidney disease: what patients. The article answered questions I didn’t even know I had until I started reading. Looking forward to reading more articles from this website.