
Stage 3 chronic kidney disease marks a significant transition: it is the first CKD stage where patients may begin to feel that something is wrong, where laboratory complications require active management, and where the intensity of medical monitoring substantially increases. At Stages G1 and G2, kidney disease is nearly always silent — identified only through screening, with no symptoms from the kidney disease itself. At Stage G3, that changes. Fatigue, nocturia, edema, and difficulty maintaining electrolyte balance begin to emerge as the kidneys lose the ability to fully compensate for their reduced capacity. The stage is divided into G3a (eGFR 45 to 59) and G3b (eGFR 30 to 44), and the clinical difference between these two sub-stages is substantial enough that most nephrologists treat them as distinct clinical entities despite sharing a stage number.
Understanding what Stage 3 kidney disease means, what symptoms to expect, what complications require treatment, and what the monitoring schedule looks like is important for patients at this stage. The window for preserving kidney function is still meaningfully open at Stage 3, and the interventions applied here — controlling blood pressure, managing anemia, correcting metabolic acidosis, and reducing proteinuria — make a measurable difference in how long it takes to reach more advanced stages, if ever.
What Stage 3 Kidney Disease Means — G3a and G3b
Stage G3 CKD is defined as an eGFR of 30 to 59 ml/min/1.73m². At this level of kidney function, the filtration capacity is 30 to 59 percent of what a young healthy adult would have, and the consequences of that reduction — in terms of waste product clearance, electrolyte regulation, acid-base balance, and hormone production — are beginning to become clinically detectable. The complete staging framework and how G3 fits within the overall CKD classification is covered in our guide to chronic kidney disease stages.
Stage G3a (eGFR 45–59) represents moderate CKD. The kidneys are functioning at 45 to 59 percent of normal. At this level, complications such as anemia and early mineral metabolism disturbances may begin to appear, but many patients still feel relatively well. The monitoring interval at G3a is every 6 months. Nephrology referral is recommended when the cause of CKD is unclear, when progression is faster than expected (more than 3 to 5 ml/min per year), or when albuminuria is in the A3 category (above 300 mg/g). Primary care physicians can appropriately manage straightforward G3a CKD, particularly in diabetic or hypertensive patients with an established cause.
Stage G3b (eGFR 30–44) represents moderately severe CKD and is a substantially different clinical situation from G3a. Complications are common and frequently symptomatic: anemia requiring active treatment, metabolic acidosis requiring bicarbonate supplementation, secondary hyperparathyroidism requiring mineral metabolism management, and hyperkalemia requiring dietary modification or medication. Blood pressure is often difficult to control. A renal dietitian referral is appropriate at this stage. Nephrology involvement is strongly recommended for virtually all G3b patients because of the complexity of managing multiple simultaneous complications alongside kidney-protective therapy. Monitoring at G3b is every 3 to 6 months. The KDIGO system recognized the clinical distinction between G3a and G3b precisely because lumping them together obscured the different management requirements of these two clinical situations.
Symptoms That May Begin at Stage 3
Stage 3 is the first CKD stage where kidney-related symptoms may emerge, though the relationship between eGFR and symptom severity varies considerably between individuals. Some patients with G3b feel only mildly different from how they felt at G2; others experience substantial fatigue and reduced exercise capacity. The variability is real and important to understand: the absence of symptoms at Stage 3 does not mean disease is stable, and the presence of symptoms does not necessarily indicate rapid progression. Laboratory trends are more reliable indicators of disease trajectory than symptom severity.
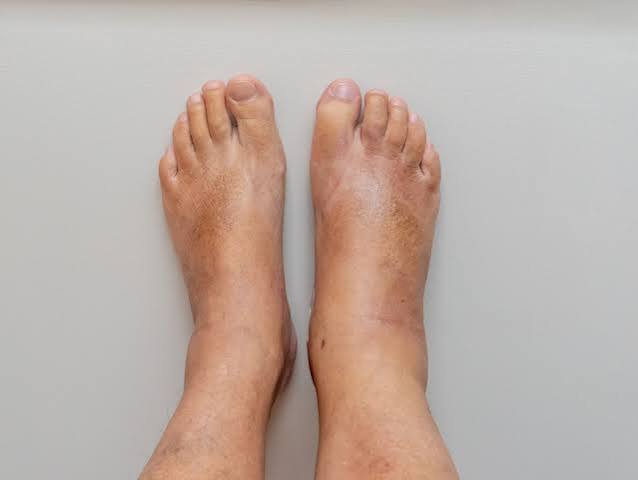
At Stage G3a, the symptoms most commonly reported — when any are present — include: fatigue (often driven by developing anemia, but also by the metabolic burden of poorly controlled diabetes or hypertension); nocturia (waking to urinate at night, reflecting the kidneys’ reduced ability to concentrate urine); mild ankle swelling if blood pressure or fluid management is suboptimal; and foamy or frothy urine in patients with significant proteinuria, which reflects the albumin being lost into the urine. Many G3a patients report no symptoms at all, particularly those who have been managing their underlying condition (diabetes, hypertension) for years and have adapted to their energy level changes gradually.
At Stage G3b, the symptom picture typically broadens. Fatigue is more pronounced as anemia becomes more established, often with hemoglobin levels in the 9 to 11 g/dL range. Dyspnea on exertion — breathlessness with physical activity — reflects the combined effects of anemia (reduced oxygen-carrying capacity), fluid retention (increased cardiac preload), and in some cases, cardiovascular disease that has progressed alongside CKD. Muscle cramps, often nocturnal, reflect electrolyte imbalances related to calcium, magnesium, and potassium changes and sometimes to metabolic acidosis. Mild pruritus (itching) may begin, though severe uremic itching is more characteristic of G4 and G5. Restless legs syndrome — an uncomfortable urge to move the legs at rest, typically at night — occurs more frequently in CKD patients than in the general population and can significantly disrupt sleep. Mild cognitive changes, including difficulty concentrating or slower mental processing, can begin at G3b in some patients, reflecting early uremic effects on the brain.
Complications That Develop at Stage 3
The complications of Stage G3 CKD are not coincidental — they reflect the kidneys’ inability to perform their multiple regulatory functions at full capacity. Each complication has a specific physiological mechanism and a corresponding management strategy.
Anemia of CKD is caused primarily by reduced production of erythropoietin, the hormone the kidneys make to stimulate red blood cell production by the bone marrow. As eGFR falls through the G3 range, erythropoietin output declines in proportion to the loss of functional kidney mass. The result is a normocytic, normochromic anemia (normal-sized, normal-colored red blood cells in reduced numbers) that develops gradually. Concurrent iron deficiency — common in CKD due to inflammation, dietary restriction, and blood loss from frequent lab draws or gastrointestinal sources — compounds the anemia. At G3a, anemia is evaluated and iron deficiency treated first (with oral or intravenous iron). Erythropoiesis-stimulating agents (ESAs) are generally reserved for patients who have hemoglobin below 10 g/dL despite iron repletion, a threshold that more often occurs at G3b and beyond.
Metabolic acidosis develops as the kidneys lose the ability to excrete the daily acid load generated by normal metabolism. At reduced GFR, less ammonium is excreted per unit time, and the net result is a gradual accumulation of acid and a fall in serum bicarbonate (HCO3) below the normal range of 22 to 29 mEq/L. KDIGO guidelines recommend initiating sodium bicarbonate supplementation when serum bicarbonate falls below 22 mEq/L. Untreated metabolic acidosis accelerates muscle protein catabolism (leading to sarcopenia and loss of functional strength), promotes bone mineral dissolution (worsening bone disease), and independently accelerates CKD progression. Treatment is simple — sodium bicarbonate tablets 650 mg two to three times daily — and the benefit in terms of slowing CKD progression has been demonstrated in multiple clinical trials.
Secondary hyperparathyroidism arises because the kidneys are responsible for the final activation of vitamin D (conversion of 25-hydroxyvitamin D to calcitriol) and for excreting phosphate. As eGFR falls, phosphate is retained in the blood. Elevated phosphate suppresses calcitriol production and directly stimulates the parathyroid glands to produce more parathyroid hormone (PTH). The parathyroid glands, attempting to compensate, enlarge and become more active. PTH acts on bone to release calcium (compensating for the low calcitriol-driven calcium absorption), but the net result is accelerated bone resorption and vascular calcification — a major driver of cardiovascular risk in CKD patients. Management at G3 includes monitoring PTH, phosphate, calcium, and 25-hydroxyvitamin D; treating vitamin D deficiency with ergocalciferol or cholecalciferol; using active vitamin D analogs (calcitriol, alfacalcidol) when PTH is elevated; and reducing dietary phosphate intake by limiting processed foods, cola drinks, and foods with phosphate additives.
Hyperkalemia (elevated blood potassium) becomes a clinically relevant risk at Stage G3, particularly in patients taking ACE inhibitors or ARBs — both of which reduce aldosterone activity and thus reduce urinary potassium excretion. At reduced eGFR, the kidneys also excrete less potassium per unit time. The combination of RAAS blockade and reduced GFR creates a meaningful hyperkalemia risk. The appropriate response to mild hyperkalemia in a CKD patient on an ACE inhibitor or ARB is usually dietary potassium restriction and, when needed, a potassium binder (patiromer or sodium zirconium cyclosilicate) — not stopping the ACE inhibitor or ARB, whose kidney-protective benefit is too important to sacrifice if manageable alternatives exist.
Monitoring Schedule at Stage 3
The monitoring frequency and panel at Stage G3 is substantially more intensive than at earlier stages, reflecting the emergence of active complications that require tracking and treatment adjustment. More on what each test measures is in our guide to kidney function tests.
At Stage G3a, monitoring is recommended every 6 months. The monitoring panel includes: serum creatinine (for eGFR calculation); urine ACR (for proteinuria trend); complete blood count (CBC) with hemoglobin (for anemia detection); serum electrolytes including potassium and bicarbonate (for hyperkalemia and metabolic acidosis); serum phosphate, calcium, PTH, and 25-hydroxyvitamin D (to establish a mineral metabolism baseline); blood pressure (at every visit); and HbA1c every 3 to 6 months in diabetic patients. The PTH and vitamin D measurements at G3a establish the baseline from which mineral metabolism monitoring will continue at more frequent intervals as the disease progresses.
At Stage G3b, monitoring is recommended every 3 to 6 months — more frequently when complications are being actively treated or when eGFR is declining. The same panel as G3a applies, but with greater attention to: hemoglobin trends (monthly in patients on ESA therapy); potassium (monthly or more frequently in patients at high hyperkalemia risk); bicarbonate (closely tracked as treatment response to sodium bicarbonate is assessed); and PTH (every 6 months at minimum, more often if significantly elevated). A renal dietitian referral at G3b allows individualized guidance on sodium, potassium, phosphate, and protein intake that accounts for the patient’s specific lab values and comorbidities. The annual health monitoring framework for all CKD stages is outlined in our guide to the annual kidney health checklist.
Treatment Priorities at Stage 3
Treatment at Stage G3 is more complex than at earlier stages because multiple simultaneous targets require management. The order of priority is: blood pressure control, proteinuria reduction, complication management (anemia, acidosis, mineral metabolism), and cardiovascular risk reduction.
Blood pressure control to below 130/80 mmHg is often more difficult at Stage G3b than at earlier stages, requiring 2 to 3 antihypertensive agents in many patients. The combination of an ACE inhibitor or ARB with a calcium channel blocker and a thiazide or loop diuretic is commonly used. SGLT2 inhibitors contribute to blood pressure reduction as well as providing independent kidney protection, and KDIGO 2024 recommends their use for patients with eGFR ≥25 and ACR ≥200 mg/g — which includes many G3a and G3b patients. A practical concern at G3b is that ACE inhibitors and ARBs both raise potassium, and this effect compounds the reduced potassium excretion of lower eGFR. Using a potassium binder to maintain RAAS blockade is preferable to stopping the ACE inhibitor or ARB.
Anemia management follows a stepwise approach: confirm iron deficiency (ferritin below 100 ng/mL or TSAT below 20%), supplement iron (oral iron sulfate or fumarate as first-line; IV iron if oral is not tolerated or absorbed), and reassess hemoglobin after 8 to 12 weeks. If hemoglobin remains below 10 g/dL despite iron repletion, ESA therapy (epoetin, darbepoetin) is considered, with a hemoglobin target of 10 to 11.5 g/dL (KDIGO recommends against targeting above 11.5 due to increased stroke risk). NSAIDs should be avoided at G3 for the same reasons as earlier stages — they acutely reduce GFR and are particularly dangerous at reduced baseline eGFR. Renally cleared medications require dose adjustment based on the current eGFR. More on how treatment decisions at this stage are guided by test results is in our guide to how doctors diagnose kidney disease.
When to Start Seeing a Nephrologist at Stage 3
At Stage G3a, nephrology referral is recommended in specific situations: when the cause of CKD is unclear and requires evaluation for possible glomerulonephritis or other diagnosable condition; when eGFR is declining faster than 3 to 5 ml/min per year; when albuminuria is A3 (above 300 mg/g); or when the patient has a condition requiring specialist management such as lupus nephritis, ANCA vasculitis, or rapidly progressive glomerulonephritis. Primary care can appropriately manage straightforward diabetic or hypertensive G3a CKD with clear cause and stable trajectory.
At Stage G3b, nephrology involvement is strongly recommended for virtually all patients because of the complexity of simultaneously managing anemia, metabolic acidosis, secondary hyperparathyroidism, hyperkalemia, blood pressure with multiple agents, and kidney-protective therapies while tracking eGFR trends and beginning education about future kidney replacement options. Introducing kidney replacement therapy education at G3b is not an emergency measure — no patient at G3b needs dialysis — but it is the appropriate time to provide information so that patients can make informed decisions over the years ahead, rather than facing these choices under crisis conditions when eGFR reaches G4 or G5. The questions worth raising with the nephrology team at this stage are outlined in our guide to questions to ask during a kidney checkup.
Frequently Asked Questions
Can you live a normal life with Stage 3 CKD? Yes — most people with Stage G3 CKD, particularly G3a, live active and full lives without significant limitation from their kidney disease. Fatigue may be present and manageable, and dietary adjustments (sodium restriction, possibly potassium and phosphate awareness at G3b) are part of daily life, but most G3 patients work, exercise, travel, and engage in normal activities. The key is consistent management of blood pressure, medications, and monitoring appointments. Kidney failure is not inevitable at Stage G3 — many G3 patients remain stable for years to decades with appropriate care.
How quickly does Stage 3 CKD progress to Stage 4? The rate of progression varies enormously and is largely determined by how well underlying causes and risk factors are controlled. A G3a patient with controlled blood pressure, treated proteinuria, and optimal SGLT2 inhibitor and RAAS blockade therapy may progress at less than 1 ml/min per year, meaning it could take 15 to 25 years to reach Stage G4 — if ever. A G3b patient with uncontrolled hypertension, significant proteinuria, and poor glucose control might progress at 5 to 10 ml/min per year, reaching G4 in 2 to 5 years. The eGFR slope — the annual rate of eGFR change — is the most important prognostic metric at this stage, and it responds meaningfully to the interventions applied.
What diet changes are needed at Stage 3 CKD? The dietary priorities at Stage G3 depend on the specific complications present. Sodium restriction below 2 grams per day helps blood pressure and reduces proteinuria and is appropriate for all G3 patients. Potassium restriction (below 40 to 60 mEq/day, roughly equivalent to avoiding high-potassium foods like bananas, potatoes, oranges, and tomatoes in large quantities) is appropriate for G3b patients with elevated potassium levels or on RAAS agents. Phosphate restriction — limiting processed foods, cola drinks, and foods with phosphate additives — is relevant at G3b if phosphate is elevated. Protein intake should be moderate (0.6 to 0.8 g/kg/day), neither severely restricted (which causes malnutrition) nor excessive (which accelerates progression). A renal dietitian can tailor these recommendations to the individual patient’s lab values, underlying diagnosis, and food preferences.
Cardiovascular Risk at Stage 3
At Stage G3, one of the most important facts about disease trajectory is that a CKD patient is more likely to die from cardiovascular disease than to reach kidney failure. The mechanisms are multiple: CKD accelerates atherosclerosis through uremia-related endothelial dysfunction, hypertension, dyslipidemia, hyperphosphatemia causing vascular calcification, anemia increasing cardiac workload, and chronic systemic inflammation. The result is that G3 patients have substantially elevated rates of heart attack, heart failure, atrial fibrillation, and stroke compared to the general population.
Cardiovascular risk management at Stage G3 therefore runs in parallel with kidney protection. Statin therapy is recommended for CKD patients with cardiovascular risk factors regardless of LDL level, based on the SHARP trial data. Blood pressure control protects both the kidneys and the heart. Anemia treatment with iron and (when needed) ESA reduces the cardiac strain of chronic low hemoglobin. Treating metabolic acidosis reduces the inflammatory and catabolic state that accelerates vascular disease. SGLT2 inhibitors provide independent cardiovascular protection alongside their kidney effects — the EMPA-REG OUTCOME and CANVAS trials demonstrated reductions in major adverse cardiovascular events in patients with high cardiovascular risk, many of whom had CKD. For G3 patients with established cardiovascular disease (prior heart attack, heart failure, stroke), anti-platelet therapy and cardiovascular-specialist co-management are part of the care framework.
Understanding that kidney disease and heart disease share risk factors, mechanisms, and treatment strategies — and that addressing one often benefits the other — helps G3 patients make sense of why their treatment regimen addresses so many different systems simultaneously. It is not redundancy; it is recognition that these conditions are biologically intertwined. A comprehensive annual review of these overlapping risks is outlined in our guide to the annual kidney health checklist, and the types of tests used to track both kidney and cardiovascular parameters are in our guide to kidney function tests.
Stage G3 CKD requires patients to take a more active role in their health than most people are accustomed to. Monitoring laboratory values, adjusting medications, following dietary recommendations, attending more frequent clinic visits — all of these demands are real. What makes the effort worthwhile is that Stage 3 is still a stage where meaningful intervention changes outcomes. The kidneys at G3 still have 30 to 59 percent of their filtering capacity, which represents significant residual function worth preserving. Every year of stability at G3 is a year not spent at G4, and for many patients, particularly those at G3a, the goal of avoiding kidney failure entirely over their lifetime is realistic and achievable. Building the management habits at Stage 3 — consistent medication adherence, dietary awareness, regular monitoring, and open communication with the care team — creates the foundation for long-term kidney health. What to discuss at each monitoring appointment is outlined in our guide to questions to ask during a kidney checkup.
Sources: NIDDK — Chronic Kidney Disease | KDIGO CKD Guidelines 2024 | National Kidney Foundation | American Kidney Fund | Related: CKD Stages Explained | Stage 2 Kidney Disease | Kidney Function Tests | Annual Kidney Health Checklist | Questions to Ask at Your Checkup
Finally a resource that explains stage 3 kidney disease: symptoms and in plain language. The practical tips made this immediately actionable, not just theoretical. Forwarding this to others in my support group who are dealing with similar issues.
As someone dealing with this personally, the stage 3 kidney disease: symptoms and section was very helpful. I appreciate that the article is careful about distinguishing between what is known and what is still being researched. Keep up this kind of thorough health journalism — it genuinely helps patients like me.
Really well-written article on stage 3 kidney disease: symptoms and. The article answered questions I didn’t even know I had until I started reading. Thank you for making complex medical information accessible without dumbing it down.