
Celiac disease is one of the most common autoimmune conditions worldwide, yet estimates suggest only 20–30% of affected individuals have received a formal diagnosis. It is not a food preference or simple sensitivity: it is a chronic immune-mediated condition in which ingesting gluten — the proteins found in wheat, barley, and rye — triggers a T-cell immune response that progressively destroys the lining of the small intestine. This causes malabsorption of essential nutrients and produces a spectrum of symptoms ranging from diarrhoea and bloating to iron deficiency anaemia, bone loss, and skin rashes that at first glance seem unrelated to the gut. The good news is that celiac disease responds completely to a strict gluten-free diet — but that treatment depends on first achieving an accurate diagnosis.
What Is Celiac Disease?
Celiac disease is an autoimmune enteropathy — an immune-mediated disease of the small intestinal mucosa. When a genetically predisposed person consumes gluten, partially digested gliadin peptides cross the intestinal epithelial barrier and interact with tissue transglutaminase (tTG), an enzyme that modifies them into a form that triggers an abnormal CD4+ T-cell immune response. This response damages the intestinal villi — the finger-like projections that massively increase mucosal surface area for nutrient absorption.
Damage is graded by the Marsh classification: Marsh 1 (increased intraepithelial lymphocytes), Marsh 2 (crypt hyperplasia), and Marsh 3a/b/c (partial, subtotal, and total villous atrophy). Total villous atrophy — the hallmark of active celiac disease — eliminates most of the proximal small bowel’s absorptive capacity, causing malabsorption of iron, calcium, folate, fat-soluble vitamins (A, D, E, K), and B12.
The genetic basis is well established: HLA-DQ2 is present in 90–95% of celiac patients; HLA-DQ8 accounts for ~5%. However, approximately 30% of the general population carries one of these alleles — only ~1% develops celiac disease. Genetic susceptibility is necessary but not sufficient; environmental and immunological triggers are also required to initiate the autoimmune cascade.
Symptoms of Celiac Disease
Celiac disease presents in two broad patterns. The classic presentation is more common in children; the non-classic picture — dominated by extra-intestinal manifestations — accounts for the majority of adult diagnoses.
Classic GI symptoms: chronic diarrhoea (often pale, greasy, and floating — steatorrhoea from fat malabsorption); abdominal bloating and excessive flatulence; cramping abdominal pain; nausea and vomiting; significant weight loss or failure to thrive.
Non-classic (extra-intestinal) presentations in adults:
- Iron deficiency anaemia: the most common presentation in adults — the duodenum is the primary site of iron absorption and the primary site of celiac damage; iron deficiency that fails to respond to oral supplementation or recurs should always prompt celiac testing
- Osteopenia/osteoporosis: calcium and vitamin D malabsorption cause reduced bone mineral density; DEXA scan is recommended at diagnosis
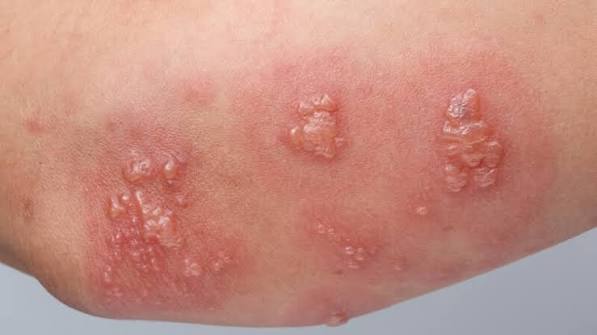
- Dermatitis herpetiformis (DH): intensely pruritic vesicular rash on extensor surfaces (elbows, knees, buttocks, scalp); the skin manifestation of celiac; caused by IgA immune complex deposition in the dermis; skin biopsy confirming IgA deposits also confirms the celiac diagnosis — duodenal biopsy is not required
- Elevated liver transaminases: unexplained ALT/AST elevation (“cryptogenic hypertransaminasaemia”) that resolves on a strict GFD; celiac should be included in the workup of unexplained liver enzyme elevation
- Peripheral neuropathy / gluten ataxia: neurological manifestations of celiac; respond to strict GFD if caught early
- Infertility and recurrent miscarriage: normalise with strict GFD
- Aphthous ulcers and dental enamel hypoplasia
Silent/asymptomatic celiac: many patients have minimal or no symptoms and are diagnosed through screening of high-risk groups or incidentally during investigation of anaemia or bone density loss.
Who Is at High Risk of Celiac Disease?
Certain groups have a substantially elevated risk and should be offered serological screening (anti-tTG IgA + total IgA) even without classical symptoms:
- First-degree relatives of confirmed celiac patients: ~10% risk
- Type 1 diabetes mellitus: ~5–10% prevalence; shared HLA-DQ genetic susceptibility
- Down syndrome, Turner syndrome, Williams syndrome
- Autoimmune thyroid disease (Hashimoto’s, Graves’): bidirectional association
- IgA deficiency: total IgA must always be checked alongside celiac serology — IgA-deficient patients have false-negative anti-tTG IgA results; IgG-based tests (DGP IgG) must be used instead
- IBS-like symptoms: celiac disease is found in approximately 1–3% of patients given an IBS label; serological exclusion is recommended before confirming IBS
How Celiac Disease Is Diagnosed
Starting a gluten-free diet before serological testing or endoscopic biopsy will normalise results and make diagnosis impossible. If you have already started a GFD, discuss a supervised gluten challenge with your doctor before proceeding with testing.
First-line serology:
- Anti-tTG IgA: sensitivity ~93%, specificity ~97%; single best first-line test; always order with total serum IgA
- Total serum IgA: essential companion — if low, switch to IgG-based tests (DGP IgG)
- Anti-endomysial IgA (EMA IgA): highly specific (~99%); used as confirmatory test; more operator-dependent
- DGP IgG: for IgA-deficient patients and children under 2 years
Upper GI endoscopy + duodenal biopsy (gold standard): positive serology is followed by OGD with at least 4 duodenal biopsies (2 from D2, 2 from the duodenal bulb — distribution of atrophy can be patchy). Marsh 3 villous atrophy on histology confirms the diagnosis. Endoscopic features (scalloping, reduced folds, nodularity) are suggestive but require histological confirmation.
Genetic testing (HLA-DQ2/DQ8): primarily an exclusion tool — a negative result has near-100% negative predictive value; useful when the patient has already started a GFD before diagnosis, or when serology and histology are equivocal. Per NICE guideline NG20, genetic testing should be used selectively, not as a routine first-line investigation.
For upper abdominal symptoms that might prompt investigation for celiac among other conditions, see our overview of when stomach pain needs evaluation.
Celiac Disease vs Similar Conditions
vs Non-coeliac gluten sensitivity (NCGS): symptoms improve on a GFD but serology and histology are completely normal — no villous atrophy, no IgA anti-tTG elevation, no nutritional deficiencies. NCGS does not cause intestinal damage or malabsorption. It is an exclusion diagnosis made after ruling out both celiac disease and wheat allergy.
vs Wheat allergy: IgE-mediated immediate hypersensitivity — urticaria, angioedema, or anaphylaxis within minutes to hours of wheat ingestion. Diagnosed by skin prick testing and wheat-specific IgE. Entirely different mechanism from the T-cell-mediated autoimmune damage of celiac disease.
vs IBS: functional GI symptoms (cramping, bloating, altered bowel habits) without mucosal damage or malabsorption. Normal serology and histology. Celiac disease should always be excluded before confirming IBS — the presentations overlap considerably. For the distinction between functional upper GI symptoms and structural conditions, see our article on H. pylori infection and stomach health and gastritis: symptoms and causes.
vs IBD: Crohn’s disease and ulcerative colitis cause mucosal inflammation visible and confirmed on colonoscopy; associated with elevated CRP and faecal calprotectin. Crohn’s disease involving the small bowel can mimic celiac but is distinguished by serology, histological pattern, and colonoscopic findings.
Complications of Untreated Celiac Disease
Untreated celiac disease carries significant long-term risks that extend well beyond digestive symptoms:
- Osteoporosis and fracture: years of calcium and vitamin D malabsorption cause progressive bone loss; fracture risk is substantially elevated in untreated patients
- Refractory celiac disease (RCD): persistent villous atrophy despite strict GFD for more than 12 months after excluding ongoing gluten exposure; Type 2 RCD is pre-malignant
- Enteropathy-associated T-cell lymphoma (EATL): rare but serious; risk substantially elevated in non-adherent patients; adherence to strict GFD normalises risk toward the general population over time
- Small bowel adenocarcinoma: rare; risk elevated in longstanding untreated disease
- Neurological complications: peripheral neuropathy, gluten ataxia — may only partially reverse if diagnosed late
Treatment and Living with Celiac Disease
The sole proven treatment for celiac disease is a strict, lifelong gluten-free diet (GFD). The internationally accepted threshold is less than 20 parts per million (ppm) of gluten — the Codex Alimentarius standard. This requires complete avoidance of wheat (including spelt, kamut, semolina, durum), barley, rye, and their derivatives. Hidden gluten sources — soy sauce, malt vinegar, most beers, many processed foods, some medications — require label literacy and ongoing vigilance.
Oats: uncontaminated certified gluten-free oats are tolerated by most celiac patients, but a small subset reacts to avenin (the oat protein). Standard practice is to avoid oats initially, confirm mucosal healing, then cautiously reintroduce certified gluten-free oats while monitoring serology.
Nutritional correction: iron, folate, B12, calcium, and vitamin D supplementation according to deficiency levels at diagnosis. Many deficiencies correct on GFD alone; supplementation bridges the initial recovery period.
Monitoring: anti-tTG IgA at 6 and 12 months to assess GFD adherence; DXA scan at diagnosis for baseline bone density; repeat duodenal biopsy at 12–24 months for RCD or persistent symptoms. Dietitian referral with expertise in celiac disease is essential at diagnosis and is recommended by NICE guideline NG20 for all newly diagnosed patients. For functional GI symptoms that may persist even on a strict GFD, see our article on functional dyspepsia explained.
The Diagnostic Delay Problem in Celiac Disease
One of the most significant challenges in celiac disease is the length of time between symptom onset and diagnosis. Studies consistently report a median diagnostic delay of 6–10 years in Western countries. During this period, patients accumulate nutritional deficiencies, bone loss, and in some cases neurological damage that may not fully reverse even after treatment begins. The diagnostic delay is driven by several overlapping factors.
First, the clinical presentation is highly variable — the majority of adult presentations are non-classic (anaemia, fatigue, bone loss, elevated liver enzymes), and these are far less likely to prompt celiac testing than the classic diarrhoea picture. A patient presenting with iron deficiency anaemia in primary care is far more likely to receive empirical iron supplementation than a celiac screen, even though recurrent or treatment-refractory iron deficiency should always raise the possibility of proximal small bowel malabsorption.
Second, many patients receive alternative diagnoses — IBS is the most common misdiagnosis — before celiac disease is considered. The overlap between IBS symptoms and functional bloating, diarrhoea, and abdominal pain means that clinicians familiar with the high prevalence of IBS may not proceed to serological testing. Current guidelines from NICE NG20 and the ACG explicitly recommend anti-tTG IgA as part of the workup for suspected IBS to exclude celiac disease before that functional label is applied.
Third, the dietary intervention (GFD) is accessible and, for some patients, produces symptomatic improvement even without a formal diagnosis — leading many people to self-initiate a GFD before testing, which invalidates the serology and biopsy. Anyone considering a GFD for suspected celiac disease should be strongly advised to complete serological testing first, then proceed to OGD if serology is positive, before making any dietary change. This preserves the diagnostic pathway and avoids the need for a prolonged and uncomfortable gluten challenge.
Monitoring and Long-Term Follow-Up in Celiac Disease
Celiac disease is a lifelong condition requiring structured long-term follow-up, not simply a one-time diagnosis and dietary advice. The monitoring framework after diagnosis serves several purposes: assessing GFD adherence, detecting nutritional deficiencies, monitoring bone density, and screening for complications including refractory celiac disease.
Serology follow-up: anti-tTG IgA should be rechecked at 6 and 12 months after starting a GFD. Falling serology indicates mucosal healing and GFD adherence; persistently elevated serology after 12 months on a reported strict GFD suggests ongoing inadvertent gluten exposure (the most common cause), or less commonly refractory celiac disease. Completely normal serology does not guarantee complete histological healing in adults — repeat biopsy at 12–24 months is recommended by most gastroenterology societies for adults with confirmed celiac, particularly if symptoms persist.
Bone density: DEXA scan at diagnosis; repeat at 3–5 years depending on baseline BMD and GFD response. Calcium and vitamin D supplementation should be maintained until bone density normalises. Weight-bearing exercise is an important adjunct to pharmacological and dietary interventions for bone health.
Annual review: NICE NG20 recommends an annual review of nutritional status, GFD adherence (serology + dietary interview), symptoms, and psychological wellbeing for all people with celiac disease. This review should include assessment for new symptoms that might indicate complications, and support for the considerable psychological burden of a lifelong restrictive diet — anxiety around eating out, label reading fatigue, and social isolation are underappreciated aspects of living with celiac disease. Peer support through organisations such as Coeliac UK (coeliac.org.uk) provides practical resources, restaurant guidance, and community support.
Gluten Cross-Contamination and Hidden Gluten Sources
For people with celiac disease, the challenge of a gluten-free diet extends well beyond avoiding obvious wheat-containing foods. Even tiny amounts of gluten — as little as 10–50 mg per day — can perpetuate villous damage in sensitive individuals. Cross-contamination during food preparation, manufacturing, or handling represents the most common cause of ongoing mucosal damage in patients who believe they are following a strict GFD.
Common hidden and cross-contamination sources include: soy sauce (traditionally wheat-fermented — tamari is typically gluten-free); malt vinegar (barley-derived); most commercial beers; many stock cubes, gravies, and sauces; communion wafers (wheat-based in many denominations); some medications (excipients including wheat starch); and “oat” products without certified gluten-free labelling. Shared cooking surfaces, toasters, colanders, and wooden utensils can transfer sufficient gluten to cause intestinal damage. Eating out poses particular risks — even dishes without obvious gluten ingredients may be cross-contaminated during preparation in shared kitchen environments.
Practical strategies for minimising cross-contamination: maintain separate preparation surfaces and utensils; use dedicated toasters and colanders; verify all packaged foods carry certified gluten-free labelling (<20 ppm); communicate clearly with restaurant staff about the severity of the requirement (not a preference); choose restaurants with experience managing celiac disease; and use validated apps and resources from organisations such as Coeliac UK to identify safe products and venues.
Celiac Disease and Mental Health
The psychological burden of celiac disease is frequently underestimated in clinical settings. Living with a condition that requires strict lifelong dietary vigilance — with no tolerance for errors, no “cheat days,” and constant social navigation around food — carries a significant mental health impact. Rates of anxiety and depression are elevated in people with celiac disease compared with the general population, and these psychological complications persist even in patients with well-managed disease on a strict GFD.
Social eating presents a particular challenge. Shared meals are a central part of social and cultural life, and the restrictions of a GFD can lead to social withdrawal, anxiety about eating out, and a sense of isolation — particularly in adolescence and early adulthood, when social eating is most significant. Health anxiety around potential gluten exposure (“What if I accidentally ate gluten?”) can itself contribute to GI symptoms via the gut-brain axis, creating diagnostic uncertainty in patients who appear serologically well but continue to report GI symptoms.
Psychological support — whether through individual counselling, CBT, or peer group support — is a recognised component of comprehensive celiac management. NICE NG20 notes that healthcare providers should be sensitive to the psychological impact of celiac disease and offer appropriate support. Many patients find that connecting with others through organisations like Coeliac UK helps normalise the experience and reduce the isolation that can accompany a lifelong restrictive dietary condition.
Frequently Asked Questions
No. “Gluten intolerance” is a colloquial term often used for non-coeliac gluten sensitivity (NCGS) — where symptoms improve on a GFD but serology and histology are completely normal. Celiac disease is a distinct autoimmune condition confirmed by elevated anti-tTG IgA and Marsh 3 villous atrophy on biopsy. Celiac disease causes measurable intestinal damage and nutritional malabsorption; NCGS does not. Both are managed with a GFD but for different reasons, with different clinical monitoring requirements.
Yes. Although the genetic basis is present from birth, celiac disease can remain clinically silent for decades and first become apparent in adulthood — often precipitated by surgery, infection, pregnancy, or significant stress. The median age at diagnosis in many Western countries is in the fourth decade of life. Adult-onset presentations are more likely to be non-classic (anaemia, bone loss, liver enzyme elevation, neurological symptoms) than the classic childhood diarrhoea picture.
Confirmation requires: (1) positive anti-tTG IgA with normal total IgA, and (2) duodenal biopsy showing Marsh 3 villous atrophy on OGD — both performed while on a normal gluten-containing diet. In children meeting strict ESPGHAN 2020 criteria (anti-tTG IgA >10× ULN + EMA positive + symptomatic + HLA-DQ2/DQ8 positive), biopsy can be avoided. Genetic testing (HLA-DQ2/DQ8) is a valuable exclusion tool but does not confirm the diagnosis.
Untreated celiac disease causes progressive intestinal damage, nutritional deficiencies (iron, calcium, vitamin D, folate, B12), and an elevated risk of serious complications including enteropathy-associated T-cell lymphoma, small bowel adenocarcinoma, and osteoporotic fracture. Quality of life is substantially impaired. A strict GFD reverses mucosal damage, corrects deficiencies, and normalises cancer risk — but delay in diagnosis translates to years of accumulated damage that may only partially reverse.
Certified gluten-free uncontaminated oats are tolerated by most celiac patients, as the avenin protein in oats has lower immunogenicity than wheat gliadin. However, a small subset of patients reacts to avenin itself. The standard approach is to avoid oats initially, confirm mucosal healing on GFD, then reintroduce certified gluten-free oats gradually while monitoring anti-tTG IgA serology. Patients who react to certified oats should avoid them permanently.
Most patients notice symptom improvement within 2–4 weeks of starting a strict GFD. Serological normalisation (anti-tTG IgA returning to the normal range) takes 6–12 months. Mucosal healing (histological recovery of villous atrophy) takes longer — typically 1–2 years in adults, and may be incomplete in some. Nutritional deficiency correction depends on the degree of depletion and concurrent supplementation. Persistent symptoms after 6–12 months on a strict GFD should prompt review for ongoing gluten exposure, SIBO, or refractory celiac disease.
No. Approximately 30% of the general population carries HLA-DQ2, HLA-DQ8, or both — but only ~1% develops celiac disease. HLA predisposition is necessary but not sufficient: additional environmental triggers, changes in intestinal permeability, and immune factors are required to initiate the autoimmune cascade. HLA testing is most useful as an exclusion tool — if neither allele is present, celiac disease is virtually excluded. A positive HLA result alone does not warrant a GFD or further investigation without clinical symptoms or positive serology.
Medical Disclaimer: This article is for educational purposes only and does not constitute medical advice. If you suspect celiac disease, consult a healthcare professional before starting a gluten-free diet — testing must be performed while on a normal gluten-containing diet to be valid.
References
- NICE guideline NG20. Coeliac disease: recognition, assessment and management. 2015. Available at: nice.org.uk.
- Rubio-Tapia A et al. ACG clinical guidelines: diagnosis and management of celiac disease. Am J Gastroenterol. 2013;108(5):656–676. Available at: PubMed.
- Husby S et al. ESPGHAN guidelines for diagnosing coeliac disease 2020. JPGN. 2020;70(1):141–156. Available at: PubMed.
- Catassi C et al. The overlapping area of non-celiac gluten sensitivity (NCGS) and wheat-sensitive irritable bowel syndrome (IBS). Nutrients. 2017;9(11):1268. Available at: PubMed.
- NHS. Coeliac disease. Available at: nhs.uk.
I was diagnosed with celiac disease 8 years after my symptoms started — I was repeatedly told it was IBS. The section about the diagnostic delay problem is so accurate and frustrating to read. Recurrent iron deficiency that didn’t respond to iron tablets was eventually what triggered the coeliac screen. Thank you for explaining this so clearly.
Thank you for sharing your experience, Priya — and 8 years is unfortunately not unusual in the diagnostic delay data. The key lesson your case illustrates is exactly what the article covers: recurrent iron deficiency that fails to respond to oral supplementation is a proximal small bowel absorption problem until proven otherwise, and coeliac disease should be near the top of that differential. We hope the earlier diagnosis has made a real difference to how you feel, and that the article helps others push for earlier testing.
The explanation of anti-tTG IgA testing alongside total IgA is something I’ve never seen clearly explained before. My daughter has IgA deficiency so the standard coeliac test was always negative even though she has the HLA genes and symptoms. The DGP IgG explanation is exactly what her gastroenterologist eventually used. Really thorough article.