
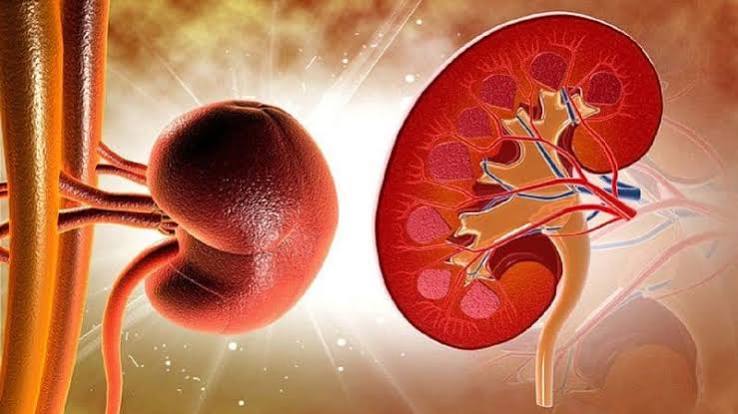
Urinating 6 to 8 times a day is considered normal for most adults with typical fluid intake. When trips to the bathroom become noticeably more frequent — more than 8 times a day, or repeatedly through the night — the cause ranges from something as simple as caffeine to conditions that require medical evaluation. For many people, frequent urination quietly erodes sleep quality, limits activities, and goes unaddressed for years. Understanding what is behind it is the first step toward actually fixing it.
What Counts as Frequent Urination?
Frequent urination — medically called pollakiuria — means urinating more than 8 times within a 24-hour period, or waking at night to urinate two or more times consistently. The nighttime version, called nocturia, is particularly important: it disrupts restorative sleep and, in older adults, increases fall risk.
Before assuming a medical cause, it is worth accounting for the most common non-medical drivers: high fluid intake (especially large amounts of water, tea, or other beverages), caffeine and alcohol (which act as mild diuretics), cold weather (which reduces perspiration and shifts fluid toward urine production), and anxiety (which can produce an urge to urinate that is not driven by bladder fullness).
When those explanations don’t fit, the most useful first distinction is between frequency with small volumes and frequency with large volumes. Small volumes, frequent trips points toward the bladder or urethra: a UTI, overactive bladder, interstitial cystitis, or prostate enlargement. Large volumes, frequent trips points toward a kidney or systemic cause — diabetes driving osmotic diuresis, or a kidney that can no longer concentrate urine properly. This pattern is called polyuria (total daily urine output above 3 liters) and its causes differ entirely from bladder-driven frequency.
Urinary Tract and Bladder Causes
Urinary Tract Infection (UTI)
The most common acute cause of frequent urination is a urinary tract infection — bacterial colonization of the bladder (cystitis) or, more severely, the kidneys (pyelonephritis). The bacteria inflame the bladder lining, which interprets that inflammation as an urgent need to void even when only a small amount of urine is present.
UTIs are far more common in women than men — approximately 50 to 60 percent of women will experience at least one in their lifetime, and recurrent infections are common. (NIDDK, 2023) The characteristic triad is burning during urination, sudden urgency, and frequency. When the infection has reached the kidneys, fever, chills, and flank pain appear. Antibiotic treatment typically resolves symptoms within 24 to 48 hours.
Overactive Bladder (OAB)
Overactive bladder is defined by urgency — a sudden, compelling need to urinate that is difficult to postpone — often with frequency and nocturia. It affects approximately 33 million adults in the United States, and its prevalence increases significantly with age. (AUA, 2023) Unlike a UTI, OAB produces negative urine cultures — there is no infection. The problem is the bladder muscle (detrusor) firing involuntary contractions before the bladder is full.
First-line treatment is behavioral: bladder training (gradually extending the time between voids), pelvic floor exercises, and limiting bladder irritants — caffeine, alcohol, and acidic foods. When behavioral approaches are insufficient, medications help: anticholinergics (oxybutynin, solifenacin) or the beta-3 agonist mirabegron. For refractory cases, intravesical botulinum toxin A injections provide significant and lasting relief.
Interstitial Cystitis / Bladder Pain Syndrome
Interstitial cystitis (IC) is a chronic condition involving bladder pressure, pain, and urinary urgency and frequency — without detectable infection. It affects an estimated 3 to 8 million Americans, predominantly women. (AUA) Because the symptoms overlap with UTI and OAB, it is often misdiagnosed or diagnosed late. Management includes dietary modification, pelvic floor therapy, and medications including pentosan polysulfate sodium (Elmiron) and intravesical instillations. Most patients achieve meaningful symptom control with a comprehensive treatment plan.
Bladder Stones and Bladder Cancer
Bladder stones irritate the bladder wall and cause frequency, urgency, and sometimes pain at the end of urination. They are most common in men with BPH or recurrent UTIs and are treated with cystoscopic fragmentation. Bladder cancer should be considered in adults over 50 — especially smokers — who experience painless blood in the urine with frequency or urgency. Any combination of urinary blood and frequency in a higher-risk individual warrants urologic evaluation.
Prostate Causes (Men)
Benign Prostatic Hyperplasia (BPH)
BPH is the most common cause of lower urinary tract symptoms in men over 50. The prostate surrounds the urethra at the bladder neck; as it enlarges, it narrows the urethral passage. The bladder compensates by contracting harder and more frequently — producing urgency, frequency, and incomplete emptying. Residual urine reduces the functional bladder volume, shortening the interval before the next urge.
BPH affects approximately 50 percent of men by age 60 and up to 90 percent by age 85. (AUA, 2023) Alpha-blockers (tamsulosin, alfuzosin) provide quick symptom relief by relaxing smooth muscle at the bladder neck. 5-alpha reductase inhibitors (finasteride, dutasteride) shrink the prostate over 6 to 12 months. Severe or refractory cases may require surgical intervention.
Prostatitis
Acute bacterial prostatitis presents urgently: high fever, perineal pain, and painful, frequent, difficult-to-initiate urination requiring prompt antibiotic treatment. Chronic prostatitis / chronic pelvic pain syndrome involves persistent pelvic discomfort, urinary frequency and urgency, and sometimes sexual symptoms lasting months. Management typically involves alpha-blockers, anti-inflammatories, and pelvic floor physical therapy.
Kidney and Systemic Causes
Diabetes Mellitus
Uncontrolled diabetes produces dramatic polyuria. When blood glucose exceeds the kidney’s reabsorption threshold (approximately 180 mg/dL), glucose spills into the urine. Glucose in the tubular fluid pulls water with it through osmosis — the result is large volumes of dilute urine, produced frequently. This classic triad — polyuria, polydipsia (intense thirst), and polyphagia (increased hunger) — is often what prompts a new diabetes diagnosis. The connection between uncontrolled diabetes and progressive kidney damage is described in the article on diabetes and kidney health.
Chronic Kidney Disease
As kidney function declines, the kidneys lose their ability to concentrate urine — particularly at night, when healthy kidneys produce very concentrated urine to allow uninterrupted sleep. This concentrating ability is often the first tubular function to deteriorate in progressive chronic kidney disease. The result is nocturia — waking repeatedly to urinate in dilute, pale urine, even when daytime frequency is not dramatically increased. Tracking kidney health numbers — eGFR and UACR — helps determine whether frequent urination reflects an underlying kidney issue.
Diabetes Insipidus
Diabetes insipidus (DI) — completely unrelated to diabetes mellitus — occurs when the body either fails to produce enough antidiuretic hormone (ADH), or when the kidneys cannot respond to it. ADH signals the kidney tubules to reabsorb water; when this signal is absent or ignored, enormous volumes of very dilute urine are produced — sometimes 10 to 20 liters per day. Central DI (caused by head trauma, pituitary tumors, or autoimmune damage) is treated with desmopressin. Nephrogenic DI (caused by lithium toxicity, hypercalcemia, or hypokalemia) is treated by removing the cause. The diagnosis is confirmed by finding very dilute urine (low osmolality) alongside elevated serum osmolality.
Medications
Loop diuretics (furosemide, bumetanide) and thiazide diuretics (hydrochlorothiazide, chlorthalidone) increase urine production as their mechanism of action — increased frequency after each dose is expected. SGLT-2 inhibitors (empagliflozin, dapagliflozin, canagliflozin) cause glucosuria that creates a mild osmotic diuresis; mild frequency increases in the first few weeks represent the medication working correctly and typically diminish over time. Caffeine and alcohol have milder diuretic effects and are a reasonable first thing to reduce in anyone with unexplained mild frequency.
Nocturia — Frequent Urination at Night
Nocturia deserves particular attention. It impairs sleep quality and significantly increases fall risk in older adults during nighttime bathroom trips. Multiple mechanisms can operate simultaneously:
- Nocturnal polyuria: the kidneys produce disproportionately large volumes of urine at night — common in adults over 60, driven by heart failure (peripheral fluid reabsorbed when lying flat is filtered as extra urine), sleep apnea (hypoxemia triggers atrial natriuretic peptide release, promoting sodium and water loss), and certain medications. A bladder diary reveals nocturnal polyuria when nighttime voids exceed one-third of total 24-hour output.
- Reduced bladder capacity: OAB, BPH with residual urine, or interstitial cystitis reduces the volume the bladder can store before triggering an urge, causing multiple small-volume wakeups.
- CKD-related concentrating failure: the kidneys produce dilute urine continuously, day and night, undermining the normal overnight urine suppression that allows uninterrupted sleep.
How Doctors Diagnose the Cause
Urinalysis and urine culture are always the first step — detecting infection, glucose (diabetes), protein (kidney damage), and blood. A negative culture is important for diagnosing OAB and IC by excluding infection.
Fasting blood glucose and HbA1c rule out diabetes in anyone presenting with polyuria. Simple, inexpensive, and should be obtained early.
Serum creatinine, eGFR, and UACR assess kidney function and detect early kidney damage. Nocturia in a person with declining eGFR points toward CKD-related concentrating impairment. A UACR above 30 mg/g suggests kidney stress. (NIDDK, 2023)
Bladder diary — 3 days of fluid intake, void timing, and void volume — distinguishes OAB from other causes and reveals whether nocturnal polyuria is present. It is one of the most informative diagnostics available for urinary symptoms and requires no laboratory equipment.
Post-void residual ultrasound measures urine remaining after voiding. A residual above 150–200 mL is significant, suggesting incomplete emptying from BPH, neurogenic bladder, or obstruction.
Serum and urine osmolality confirm diabetes insipidus when suspected: very dilute urine (low osmolality) combined with elevated serum osmolality confirms inappropriate free-water loss. (Mayo Clinic, 2024)
When to See a Doctor
Same day or urgent care if: frequent urination with fever, chills, or back/flank pain (possible kidney infection); visible blood in the urine with frequency or urgency.
Schedule an appointment if: frequency or nocturia has been present for more than 2 to 4 weeks; symptoms are disrupting sleep or daily life; associated increased thirst, unexpected weight loss, or fatigue (possible diabetes or kidney disease); men over 50 with frequency and weak stream, hesitancy, or incomplete emptying (BPH evaluation needed).
For people with known diabetes or chronic kidney disease: any new or worsening nocturia is worth reporting — it may signal a change in kidney function. The article on foamy urine describes another urinary symptom of kidney disease that often accompanies frequency changes in CKD.
Frequently Asked Questions
Is it normal to urinate every 2 hours?
Urinating every 2 hours — roughly 8 to 12 times per day — is at the borderline of normal. If it is associated with moderate fluid intake, no urgency or discomfort, no leakage, and has always been the person’s pattern, it may simply be their individual normal. If it represents a change from previous habits, comes with urgency, or involves large volumes, it warrants evaluation. A 3-day bladder diary is a useful first step to clarify whether the pattern is within normal range.
What causes frequent urination at night?
The most common causes are nocturnal polyuria (from heart failure, sleep apnea, or fluid redistribution in older adults), BPH in men, overactive bladder, and CKD-related loss of urine concentrating ability. Whether the kidneys are making too much urine at night or the bladder cannot store a normal nighttime volume determines which treatment is most effective — a bladder diary and basic labs help make this distinction.
Can kidney disease cause frequent urination?
Yes — particularly nocturia. As kidney function declines, the tubules lose their ability to concentrate urine overnight. This means the kidneys continue producing significant volumes of dilute urine through the night, overriding the body’s normal overnight urine suppression. Nocturia developing in a person with CKD risk factors is one reason UACR and eGFR testing are important — kidney disease can progress before eGFR declines to the level that triggers clinical concern.
What is the difference between frequent urination and polyuria?
Frequent urination means voiding more than 8 times per day, regardless of volume. Polyuria specifically means total urine output above 3 liters per day. A person with OAB may void 12 times per day in small amounts — frequent, but not polyuria. A person with uncontrolled diabetes may void 8 times per day in very large amounts — polyuria that may not feel like extreme frequency. Both cause many bathroom trips, but their causes and treatments are completely different.
When is frequent urination an emergency?
Frequent urination with fever and back pain (possible kidney infection), with visible blood in the urine (possible cancer, stones, or kidney disease), or sudden-onset dramatic polyuria with severe thirst after a head injury or pituitary surgery (possible central DI) should all be evaluated urgently — the same day, or in an emergency department if other acute symptoms are present.
Frequent urination is one of the most common symptoms adults bring to their physicians — and the range of causes is wide. The distinction between small-volume frequency and large-volume polyuria, and between daytime and nighttime patterns, narrows that range considerably before a single test is run. Most causes respond well to treatment when accurately identified. Adapting to disrupted sleep or restricted activity without investigation means missing the opportunity to address something that is, in most cases, both findable and treatable.
The Role of the Nervous System in Urinary Frequency
Urinary frequency is not always driven by a structural problem with the bladder, prostate, or kidneys. The nervous system plays a central role in controlling when and how urgently the bladder signals the need to void — and disruption of those signals at any level of the nervous system can produce dramatic urinary symptoms, including frequency, urgency, and incomplete emptying.
The detrusor muscle — the muscle that contracts to expel urine — is innervated by both the parasympathetic (which contracts the bladder) and sympathetic (which relaxes the bladder and contracts the internal sphincter) divisions of the autonomic nervous system. The voluntary external sphincter is under somatic motor control via the pudendal nerve. Normal, controlled urination requires precise coordination of all three systems. Disruption at any point in this circuit produces what is collectively called neurogenic bladder — a broad category encompassing symptoms that range from urgency-frequency to urinary retention.
Multiple sclerosis (MS) affects bladder control in up to 80 percent of patients over the course of the disease. Depending on the level and location of demyelinating lesions, MS can cause urgency, frequency, urge incontinence, or urinary retention — often in the same patient at different times as lesion burden changes. Parkinson’s disease is associated with detrusor overactivity in up to 70 percent of patients; the basal ganglia normally suppress involuntary bladder contractions, and their dysfunction in Parkinson’s removes this inhibition, producing the urgency-frequency syndrome seen in many patients with the disease.
Spinal cord injury — depending on the level and completeness of injury — produces either a hyperreflexic bladder (above the sacral cord, with involuntary contractions and urgency) or a flaccid, areflexic bladder (at or below the sacral cord, with urinary retention). Diabetic autonomic neuropathy damages the peripheral nerves supplying the bladder, impairing the sensation of bladder fullness and the coordinated contraction of the detrusor. The result is a large-capacity, poorly contracting bladder that eventually causes overflow incontinence — frequent dribbling of urine from an overfull bladder — rather than the urgency pattern seen in OAB. This diabetic cystopathy is one of the less commonly recognized complications of long-standing poorly controlled diabetes.
Lifestyle Factors and Urinary Frequency
Beyond medical conditions and medications, several modifiable lifestyle factors influence urinary frequency — and addressing them is often the most effective first step before prescribing medications or ordering extensive tests.
Fluid intake is the most obvious lever. Adults who drink 2.5 to 3 liters or more per day will naturally urinate more frequently than those drinking 1.5 liters. Redistributing fluid intake to avoid consuming large amounts in the 3 to 4 hours before bedtime is a simple strategy that often substantially reduces nocturia. The type of fluid matters as well: caffeinated beverages (coffee, tea, energy drinks, many sodas) and alcohol both suppress antidiuretic hormone production temporarily, increasing urine output beyond what the fluid volume alone would produce. Carbonated beverages and citrus juices may irritate the bladder lining in people with OAB or IC.
Body weight affects urinary frequency through multiple mechanisms. Obesity increases intra-abdominal pressure on the bladder, reducing its effective capacity and triggering urgency at lower fill volumes. It is also an independent risk factor for OAB in both men and women. A reduction of 5 to 10 percent of body weight in overweight or obese adults with OAB symptoms produces a clinically meaningful reduction in urinary frequency and urgency in published trials.
Physical inactivity and constipation also contribute. Constipation increases rectal pressure on the bladder, reducing its functional capacity. Pelvic floor dysfunction — which can result from prolonged sitting, childbirth trauma, or lack of pelvic floor exercise — impairs the coordinated inhibition of bladder contractions during filling. Pelvic floor physical therapy addresses these structural contributions and is a recommended first-line intervention for both OAB and stress incontinence in clinical guidelines.
Using a Bladder Diary: A Practical Guide
Among all the tools available to evaluate frequent urination, the bladder diary is the most informative and the most underused. It costs nothing, requires no laboratory visit, and produces data that no single clinical encounter can replicate. Most urologists and urogynecologists ask patients with urinary frequency to complete a 3-day bladder diary before their first appointment — yet the majority of patients arrive without one because nobody explained how to do it or why it matters.
A bladder diary records: (1) the time of each urination, (2) the volume of urine produced (measured by urinating into a measuring container, available at any pharmacy for a few dollars), (3) the time and volume of each drink consumed, (4) any episode of urgency (the sudden, hard-to-defer urge), and (5) any episode of leakage. Keeping this record for three consecutive days — at least one of which should be a typical workday and one a rest day — gives the physician a dataset that reveals patterns invisible to a clinical interview.
From the bladder diary, the clinician can calculate: the total 24-hour urine volume (to determine if polyuria is present), the average voided volume per urination (small average volume suggests OAB or BPH with incomplete emptying; large average volume suggests polyuria from a kidney or systemic cause), the nocturnal urine volume as a proportion of total output (greater than one-third is diagnostic for nocturnal polyuria), and the maximum voided volume (which approximates functional bladder capacity). These numbers guide treatment selection more precisely than any single test can.
If completing a full diary feels burdensome, even a simpler version is helpful: write down the time and a rough sense of the volume (small / medium / large) for 24 to 48 hours. This still reveals whether the pattern is frequency with small volumes or frequency with large volumes — the single most important distinction in the initial evaluation of frequent urination. Sharing that record with your physician, even in an informal format, moves the diagnostic conversation forward considerably.
Sources: NIDDK (niddk.nih.gov), American Urological Association (auanet.org), Mayo Clinic (mayoclinic.org), CDC (cdc.gov)
My doctor recommended I look into frequent urination: possible kidney and urinary and this article covered it perfectly. What I liked most was that the article didn’t just say what to avoid — it also gave alternatives. Looking forward to reading more articles from this website.
I have been reading about frequent urination: possible kidney and urinary for weeks and this is the most thorough guide I found. The section on managing this condition day-to-day was especially useful for planning. Exactly the kind of evidence-based information that is hard to find in one place.
I never fully understood frequent urination: possible kidney and urinary until I read this. This is the kind of evidence-based writing that actually changes how people approach their health. I wish I had found this article earlier — would have saved a lot of confusion.