
UTI vs Kidney Infection: What Is the Difference?
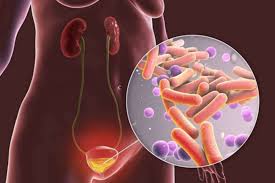
Urinary tract infections (UTIs) and kidney infections are related but distinct conditions that differ fundamentally in their location, severity, symptoms, and potential consequences. A UTI is a broad term that encompasses any infection of the urinary tract — including the urethra, bladder, and kidneys. In common clinical usage, however, “UTI” most often refers specifically to a bladder infection (cystitis), which is confined to the lower urinary tract. A kidney infection (pyelonephritis), by contrast, is an upper urinary tract infection that involves the kidney tissue itself. Understanding the distinction between these two conditions is important because they require different treatment approaches and carry very different risks of serious complications.
Both conditions are caused predominantly by bacteria — most commonly Escherichia coli, which accounts for 70 to 90% of uncomplicated urinary tract infections. The bacteria typically originate from the gastrointestinal tract, colonize the periurethral area, and ascend through the urethra into the bladder. If the infection remains in the bladder, it is a lower UTI (cystitis). If bacteria continue ascending through the ureters to reach one or both kidneys, the result is a kidney infection. This ascending pathway is the most common mechanism for both conditions, which is why almost any kidney infection begins as — or coexists with — a bladder infection.
Location: Where the Infection Is Makes All the Difference
The most fundamental difference between a UTI and a kidney infection is anatomical. A bladder infection (lower UTI) is confined to the bladder — a hollow organ whose lining can become inflamed and irritated but which does not have the vital metabolic functions of the kidneys. Because the infection is localized to the bladder mucosa, it typically does not cause systemic symptoms unless it spreads upward.
A kidney infection involves the renal parenchyma — the functional tissue of the kidney responsible for filtering blood, regulating fluid balance, removing waste products, and producing hormones. When bacteria invade the kidney tissue, the resulting inflammation can impair kidney function, cause bacteremia (bacteria entering the bloodstream), and potentially lead to permanent scarring. The kidneys are also richly vascularized, which means bacterial products and toxins can disseminate into the bloodstream rapidly, creating the risk of sepsis that does not exist with a simple bladder infection. This anatomical difference — organ tissue versus hollow organ lining — explains almost all the clinical differences between the two conditions.
Symptoms: How to Tell the Two Conditions Apart
The symptom profiles of bladder infections and kidney infections overlap partially but differ in important ways. Both conditions cause the classic lower urinary tract symptoms that most people associate with a UTI: burning or pain with urination (dysuria), increased frequency and urgency to urinate, cloudy or dark urine, and sometimes blood in the urine (hematuria). These symptoms arise from bacterial irritation of the bladder lining and urethral inflammation, and they are present in most cases of bladder infection and in most — though not all — cases of kidney infection.
The key distinguishing symptoms of a kidney infection are systemic and reflect the involvement of organ tissue and the inflammatory response it generates. Fever — typically 38.5°C (101.3°F) or above — is present in the majority of patients with pyelonephritis and is essentially absent in uncomplicated bladder infections. A fever in someone with urinary symptoms is a strong indicator that the infection has reached the kidneys and is no longer confined to the lower tract. Chills and rigors — particularly severe, uncontrolled shaking — suggest that bacteria have entered the bloodstream and that bacteremia or early sepsis may be developing.
Flank pain or back pain at the costovertebral angle (the junction of the lowest rib and the spine, on one or both sides) is the anatomical signature of kidney involvement. Unlike the lower abdominal cramping or suprapubic discomfort that accompanies bladder infections, flank pain reflects inflammation of the kidney capsule and surrounding tissue. It is often described as a constant, aching, or throbbing pain and may radiate toward the groin. Costovertebral angle tenderness — elicited when a clinician taps gently on the back at this location — is one of the most reliable physical examination findings in pyelonephritis.
Nausea and vomiting are significantly more common in kidney infections than in bladder infections and occur in approximately half of patients with pyelonephritis. They are driven by the systemic inflammatory response and by vagal stimulation from the inflamed kidney. Severe nausea that prevents oral fluid and medication intake is itself a reason to seek emergency care, because it makes outpatient oral antibiotic treatment impractical.
General malaise and fatigue — feeling profoundly unwell, weak, and exhausted beyond what the urinary symptoms alone would explain — is a hallmark of systemic infection and strongly favors kidney infection over a simple bladder infection. A patient with a bladder infection typically feels uncomfortable and bothered but is otherwise functional. A patient with a kidney infection often feels genuinely ill and may have difficulty carrying out normal daily activities.
Severity and Risk: Why Kidney Infections Are More Serious
Bladder infections, while painful and disruptive, are generally not dangerous in otherwise healthy adults. They rarely cause permanent harm, do not spread to other organs when confined to the bladder, and resolve fully with a short course of appropriate antibiotics (typically 3 to 7 days for women). The primary risk of undertreated bladder infection is progression to kidney infection — which is why it is important to treat lower UTIs promptly and completely.
Kidney infections carry a meaningfully higher risk of serious complications. Urosepsis — sepsis originating from a urinary source — occurs when bacteria or their toxins enter the bloodstream and trigger a systemic inflammatory response. Urosepsis accounts for approximately 25% of all sepsis cases and carries a mortality rate of 10 to 30% once septic shock develops. Patients with high fever, rigors, and hemodynamic instability (low blood pressure, rapid heart rate) require immediate emergency evaluation and IV antibiotics — delay in treatment significantly worsens outcomes.
Renal abscess is a localized collection of pus within the kidney that forms when bacterial infection cannot be cleared by the immune system or by standard antibiotic therapy. Small abscesses may resolve with prolonged antibiotic courses, but larger abscesses typically require percutaneous drainage guided by CT imaging or ultrasound. Permanent renal scarring can follow repeated or severe kidney infections, particularly in individuals with structural abnormalities or vesicoureteral reflux. Over years, scarring can lead to chronic kidney disease, hypertension, and in severe cases, end-stage renal disease requiring dialysis. Emphysematous pyelonephritis, a rare but life-threatening gas-forming kidney infection that occurs almost exclusively in patients with diabetes, carries a mortality rate exceeding 40% without surgical intervention.
Diagnosis: Different Tests, Different Thresholds
For uncomplicated bladder infections in otherwise healthy women, diagnosis is primarily clinical — based on characteristic symptoms — and a urine dipstick or urinalysis showing nitrites and white blood cells is often sufficient to start empiric treatment without formal culture. This is a well-validated approach that avoids unnecessary testing and delays in treatment for what is a self-limited and predictable condition.
Kidney infections require a higher diagnostic standard. A urine culture with sensitivity testing is essential for pyelonephritis — unlike a bladder infection, where empiric treatment without culture is often acceptable, a kidney infection involves organ tissue and carries a risk of serious complications from inadequate treatment. Knowing which specific organism is causing the infection and which antibiotics it is sensitive to guides appropriate antibiotic selection, especially in an era of increasing antibiotic resistance. Blood cultures are indicated when bacteremia is suspected (high fever with rigors, hemodynamic instability), and inflammatory markers such as C-reactive protein and procalcitonin help assess infection severity and response to treatment.
Imaging is not required for uncomplicated bladder infections but plays a more important role in kidney infection management. A renal ultrasound is often the first imaging step to rule out hydronephrosis (ureteral obstruction) and gross abscess. CT urogram provides greater anatomical detail and is the imaging modality of choice when the diagnosis is uncertain, when the patient fails to respond to initial antibiotic therapy within 48 to 72 hours, or when complications are suspected. Cystoscopy — direct visual inspection of the bladder — is generally not indicated for either acute UTI or acute kidney infection but may be performed in the workup of recurrent infections.
Treatment: Tailored to Severity and Location
Treatment of bladder infections is typically straightforward: a short course of oral antibiotics — nitrofurantoin (5 to 7 days), trimethoprim-sulfamethoxazole (3 days), or fosfomycin (single dose) for uncomplicated infections in women. The antibiotic selected should be matched to local resistance patterns, and culture-guided therapy is used when empiric choices fail or when risk factors for resistant organisms are present.
Treatment of kidney infections requires longer antibiotic courses and, in many cases, hospitalization for IV antibiotics. Oral fluoroquinolones (ciprofloxacin or levofloxacin, typically 7 days) remain first-line for mild to moderate outpatient pyelonephritis where local resistance rates are acceptable. Patients who are unable to take oral medications due to nausea and vomiting, who have high fever with rigors suggesting bacteremia, who are pregnant, or who have immune compromise require inpatient IV antibiotic therapy. Extended-spectrum cephalosporins (ceftriaxone), piperacillin-tazobactam, or carbapenems are used for resistant organisms in the inpatient setting. The total treatment course for pyelonephritis ranges from 7 to 14 days depending on the antibiotic used and the patient’s clinical response.
For both conditions, completing the full antibiotic course is essential. Stopping early — even when symptoms have resolved — allows the most antibiotic-tolerant bacteria to survive and multiply, risking recurrence with a more resistant strain. A test-of-cure urine culture after completing treatment is recommended for kidney infections, pregnant women, and patients with complicated or unusual presentations. For straightforward bladder infections with complete symptom resolution, a follow-up culture is not typically required.
When to Seek Urgent or Emergency Care
A bladder infection warrants a same-day or next-day appointment with a primary care provider or urgent care clinic. It does not typically require emergency department evaluation unless symptoms are unusually severe or there is a concern for kidney involvement based on the symptom pattern described above.
Kidney infection requires a higher level of urgency. Fever plus flank pain plus urinary symptoms is a combination that should prompt same-day evaluation — at a minimum. The following findings should trigger an emergency department visit without delay: high fever (above 39°C / 102.2°F), rigors (uncontrolled shaking chills), confusion or altered mental status, inability to keep fluids or medications down, pregnancy, signs of shock (rapid heart rate, low blood pressure), or any condition that severely compromises immune function. Urosepsis progresses rapidly and responds best to early aggressive treatment — waiting to “see if it gets better” is a meaningful risk factor for poor outcomes.
For practical guidance on recognizing UTI symptoms in different populations, see the UTI symptoms and causes guide on Horizon Health Guide. For a detailed clinical review of pyelonephritis, the kidney infection article on this site covers diagnosis and management in depth. The CDC’s UTI patient information page provides additional public health guidance, and the StatPearls pyelonephritis review is an authoritative clinical reference.
Special Situations: When the Line Between UTI and Kidney Infection Is Less Clear
In clinical practice, the distinction between bladder infection and kidney infection is not always clean. Some patients with documented pyelonephritis have minimal or no systemic symptoms — subclinical pyelonephritis, sometimes also called “occult” or “upper tract” UTI — particularly early in the course of infection before the inflammatory response has fully developed. Conversely, some patients with severe bladder infections develop significant pain and fever, making the clinical picture resemble kidney infection even when imaging confirms the infection has not reached the kidney.
In elderly patients, the classic symptom triad of fever, flank pain, and dysuria may all be absent or attenuated. Confusion, agitation, and functional decline may dominate the clinical picture, making it difficult to localize the infection clinically. In such cases, laboratory markers — particularly procalcitonin (elevated in systemic bacterial infection, not in asymptomatic bacteriuria) — combined with clinical judgment and careful physical examination provide the most reliable diagnostic pathway.
Children with UTI deserve special mention: they are at substantially higher risk of upper tract involvement than adults, and even what presents as a simple febrile UTI in a child may involve subclinical renal inflammation. The Kidney Disease Improving Global Outcomes (KDIGO) guidelines and American Urological Association pediatric UTI guidelines recommend imaging evaluation for children after a first febrile UTI to assess for vesicoureteral reflux and renal scarring — a recommendation that reflects the higher risk of long-term renal consequences from childhood pyelonephritis compared to adult disease.
A Practical Summary: Key Differences at a Glance
To summarize the core differences: a bladder infection (lower UTI) is localized to the bladder, causes urinary symptoms (burning, frequency, urgency, cloudy urine) without systemic signs, is generally not dangerous in healthy adults, responds to a short antibiotic course, and does not typically require emergency evaluation. A kidney infection (pyelonephritis) involves the kidney itself, adds systemic symptoms to the urinary picture (fever, chills, flank pain, nausea, malaise), can progress to bacteremia and urosepsis, requires longer antibiotic treatment — and often IV antibiotics in hospital — and warrants urgent to emergency evaluation depending on severity.
The practical rule: if you have urinary symptoms without fever and without back or flank pain, you probably have a bladder infection — call your doctor for same-day or next-day evaluation. If you have urinary symptoms with fever above 38.5°C (101.3°F) or with significant back or flank pain, you may have a kidney infection — seek care the same day. If you have high fever with rigors, confusion, very low blood pressure or very fast heart rate, or are pregnant, go to the emergency department immediately. This simple framework, combined with awareness of the symptom differences outlined in this article, can meaningfully speed up diagnosis and treatment and reduce the risk of serious complications.
Sources: CDC — Urinary Tract Infections · StatPearls — Pyelonephritis · StatPearls — Cystitis
Risk Factors: Who Is More Vulnerable to Each Condition?
Both bladder infections and kidney infections are significantly more common in women than in men, primarily due to the shorter female urethra — which is approximately 4 centimeters long compared to 20 centimeters in men — allowing bacteria to reach the bladder and kidneys more easily. Among women, the risk of lower UTI increases substantially with sexual activity, use of spermicide-containing contraceptives, a new sexual partner, and a personal or family history of recurrent UTIs. Postmenopausal women face elevated risk from declining estrogen levels that reduce the protective Lactobacillus-dominant vaginal flora and thin the urethral epithelium. Pregnancy increases the risk of kidney infection specifically because the ureters dilate under hormonal influence, allowing bacteria that colonize the bladder to ascend more easily to the kidneys — which is why screening for and treating asymptomatic bacteriuria in pregnancy is standard care.
For kidney infection specifically, additional risk factors beyond those for lower UTI include: vesicoureteral reflux (VUR), which allows urine to flow backward from the bladder into the ureters and kidneys; urinary tract obstruction from kidney stones, ureteral strictures, or an enlarged prostate in men; structural abnormalities of the kidney such as polycystic kidney disease or a horseshoe kidney; urinary catheterization and other urological instrumentation; diabetes mellitus, which impairs neutrophil function and predisposes to more severe and resistant infections; and immune-compromising conditions such as HIV infection, organ transplantation, or chemotherapy. Men who develop a kidney infection without an obvious precipitating cause (such as recent catheterization or known structural abnormality) should be evaluated for prostatic involvement, since chronic prostatitis can serve as a bacterial reservoir that perpetuates upper tract infection.
Prevention Strategies: Reducing Risk of Both UTI and Kidney Infection
The most effective prevention strategy for kidney infection is preventing lower UTIs from occurring in the first place — because almost every kidney infection begins as a bladder infection that ascends. The evidence-based behavioral interventions that reduce bladder infection risk therefore also reduce kidney infection risk: adequate daily fluid intake (at least 2 liters of water, with higher intake associated with lower UTI rates in clinical trials), regular voiding rather than holding urine for extended periods, post-coital voiding within 30 minutes of intercourse in women with sex-associated recurrence, avoidance of spermicide-containing contraceptives, and wiping from front to back after toileting.
For women with recurrent lower UTIs, low-dose prophylactic antibiotics — either taken daily or as a single post-coital dose — reduce recurrence rates by 80 to 95% and correspondingly reduce the risk of ascending kidney infection. Topical intravaginal estrogen for postmenopausal women restores the vaginal microbiome’s Lactobacillus dominance and has been shown in randomized controlled trials to significantly reduce recurrent UTI frequency. Non-antibiotic approaches including D-mannose supplementation (which competitively inhibits E. coli adhesion to bladder epithelium) and cranberry products containing proanthocyanidins have modest supporting evidence as adjunctive prevention measures, particularly for E. coli-related recurrence.
Addressing structural risk factors is important for preventing both lower and upper UTI recurrence. Treatment of kidney stones, management of benign prostatic hyperplasia in men, correction of vesicoureteral reflux (particularly in children and young adults with documented reflux nephropathy), and minimizing urinary catheter use all reduce the anatomical conditions that promote infection and ascending spread. For patients who have already experienced a kidney infection, a conversation with a urologist or primary care provider about structural risk factor evaluation and individualized prevention planning is a high-value step that many patients skip — often leading to preventable recurrence.
Antibiotic Resistance: An Increasingly Important Consideration
Antibiotic resistance is a growing challenge in the management of both bladder infections and kidney infections, but its consequences are more serious for kidney infections. For bladder infections, resistance to first-line antibiotics such as trimethoprim-sulfamethoxazole means a switch to a different agent — inconvenient and possibly leading to a slightly longer symptom duration, but generally not dangerous. For kidney infections, resistance to the empirically chosen antibiotic means that the patient is receiving inadequate treatment while the infection progresses in organ tissue — potentially allowing bacteremia and sepsis to develop before culture results confirm the resistant organism and guide appropriate therapy.
Extended-spectrum beta-lactamase (ESBL)-producing organisms — particularly ESBL-producing E. coli and Klebsiella — are increasingly common causes of complicated UTI and kidney infection, especially in patients with recent antibiotic exposure, recent hospitalization, or prior urological procedures. ESBL-producing bacteria are resistant to most penicillins and cephalosporins and typically require carbapenems for effective inpatient treatment. Carbapenem-resistant Enterobacteriaceae (CRE) represent the most concerning end of the resistance spectrum, with very limited treatment options. These organisms are rare in community-acquired UTI but are encountered in healthcare-associated settings. Obtaining a urine culture with full sensitivity testing for every kidney infection — and using culture results to confirm or adjust empiric antibiotic choices — is the essential safeguard against inadequate treatment of resistant organisms.
I went to urgent care last week with what I thought was a bad UTI — burning, frequency, the usual. But the doctor said my fever of 102.4°F and the tenderness in my lower back meant it had probably already reached my kidneys. She ordered a urine culture and sent me home with ciprofloxacin for 10 days instead of the 3-day course I expected. I didn’t realize how quickly a UTI could escalate. This article explains the progression so clearly. I would have waited longer to see someone if I hadn’t had the fever.
As a pharmacist I get questions about this distinction all the time. Patients assume that a UTI is a UTI and all they need is a short antibiotic course. The section on why culture-guided therapy matters more for kidney infections is especially important — I’ve had to counsel patients who were given a three-day TMP-SMX course for what turned out to be pyelonephritis caused by a resistant organism, and they came back two weeks later much sicker. Great clinical breakdown.
Thank you for raising that point, Kevin — the culture-guided therapy issue is really critical for kidney infections in a way it often isn’t for simple bladder infections. With a bladder infection in an otherwise healthy woman, empiric treatment without culture is widely accepted because the stakes of a mismatch are relatively low — you might need a second antibiotic, but the infection stays contained. With a kidney infection, inadequate antibiotic coverage means the infection continues progressing in organ tissue, and bacteremia can develop before you realize the first antibiotic isn’t working. Every kidney infection should get a culture drawn before antibiotics start, and clinicians should follow up on culture results to confirm the chosen antibiotic is appropriate. We appreciate your perspective!