
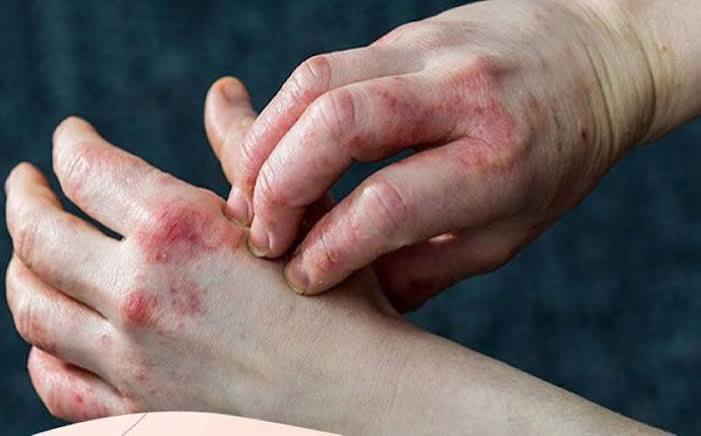
Every adult living with diabetes carries a risk that goes beyond daily blood sugar readings: the risk of long-term diabetes complications that develop silently over years and decades of elevated glucose. Diabetes complications are the primary reason that diabetes management matters — they determine whether a person living with the condition reaches older age with full function and quality of life, or faces premature disability, organ failure, or cardiovascular death. The CDC estimates that diabetes is the eighth leading cause of death in the United States, but its true toll is understated because most people with diabetes die of cardiovascular disease listed as the primary cause. Understanding which diabetes complications to watch for, why they develop, and what interventions actually reduce their risk is the foundation of informed, proactive diabetes management for every adult diagnosed with the condition.
According to the CDC, approximately 38 million Americans have diabetes, and a significant proportion will develop at least one serious complication during their lifetime. Adults with diabetes are two to four times more likely to develop cardiovascular disease than adults without diabetes. Diabetic kidney disease affects an estimated 1 in 3 adults with diabetes. Diabetic retinopathy is the leading cause of new blindness in working-age adults in the United States. Lower extremity amputations are performed in adults with diabetes at rates 10 times higher than in the general population — yet the vast majority are preventable with consistent foot care and glucose management.
How Elevated Blood Sugar Damages the Body
The link between elevated blood glucose and organ damage is not a simple linear relationship — it involves at least four distinct biological mechanisms that operate simultaneously and compound each other’s effects over time. Understanding these mechanisms explains why maintaining blood glucose as close to the normal range as possible is so important, and why every percentage point of A1C reduction translates into meaningful complication risk reduction across all organ systems:
- Endothelial dysfunction and vascular damage: The endothelium — the single-cell lining of every blood vessel in the body — is exquisitely sensitive to chronic hyperglycemia. When blood glucose is persistently elevated, the endothelium produces less nitric oxide (the primary vasodilatory and anti-inflammatory signal), becomes more permeable to LDL cholesterol, and upregulates adhesion molecules that recruit inflammatory cells into the vessel wall. This endothelial dysfunction is the earliest detectable step in atherosclerosis — occurring years before measurable plaque formation — and it underlies the dramatically elevated cardiovascular risk of adults with long-standing diabetes. The A1C test measures glycated hemoglobin, a direct marker of the overall glucose burden that drives endothelial damage; reducing A1C by 1% is associated with a 14% reduction in heart attack risk in adults with Type 2 diabetes. Our A1C testing schedule guide covers how often monitoring should occur and what A1C targets mean for complication prevention.
- Advanced glycation end-products (AGEs) and structural protein damage: Prolonged hyperglycemia drives the non-enzymatic glycation of proteins throughout the body — glucose molecules attach to and modify proteins, forming advanced glycation end-products (AGEs). AGEs cross-link with collagen in arterial walls, the glomerular basement membrane of the kidney, and the lens of the eye — stiffening these structures, impairing their function, and triggering RAGE (receptor for AGE) receptor-mediated inflammation that further damages surrounding tissue. In the kidney, AGE-driven glomerular basement membrane thickening is a central mechanism of diabetic nephropathy progression. In the lens, AGE accumulation contributes to earlier cataract formation. In arterial walls, AGE-mediated collagen cross-linking increases arterial stiffness and accelerates atherosclerosis. Unlike many acute effects of hyperglycemia, structural AGE accumulation is not rapidly reversible when glucose improves — which is one reason early glucose control produces a far greater complication-reduction benefit than identical glucose control started later in the disease course (the “legacy effect” or “metabolic memory” demonstrated in the UKPDS and DCCT/EDIC studies).
- Oxidative stress and mitochondrial dysfunction: Chronic hyperglycemia overwhelms the cell’s antioxidant defenses by dramatically increasing mitochondrial production of reactive oxygen species (ROS). These free radicals damage cell membranes, DNA, and proteins throughout the body — impairing endothelial function, oxidizing LDL cholesterol (a critical step in atherosclerotic plaque initiation), damaging nerve axon mitochondria (contributing to peripheral neuropathy), and injuring the specialized cells of the glomerulus in the kidney. In diabetic neuropathy specifically, mitochondrial ROS damage to peripheral nerve axons leads to progressive loss of both myelinated (pain/temperature sensing) and unmyelinated (autonomic) nerve fibers — which manifests as burning pain, numbness, and eventually loss of protective sensation that dramatically increases injury and infection risk in the feet.
- Polyol pathway activation and intracellular sorbitol accumulation: In cells that absorb glucose without insulin — including lens cells, retinal pericytes, Schwann cells of peripheral nerves, and glomerular mesangial cells — chronic hyperglycemia leads to glucose being metabolized through the polyol pathway rather than normal glycolysis. This produces sorbitol accumulation, osmotic stress, NADPH depletion (reducing antioxidant capacity), and myoinositol depletion. In peripheral nerves, polyol pathway activation contributes to nerve conduction slowing and axon degeneration. In the retina, sorbitol accumulation damages pericytes — the specialized cells that support retinal capillaries — leading to the microaneurysm formation that represents the earliest detectable sign of diabetic retinopathy. The comprehensive annual monitoring that tracks complications across all affected organ systems is in our annual diabetes care checklist. Authoritative information on how diabetes causes complications is available from the American Diabetes Association’s complications resources and the NIDDK’s diabetes complication prevention information.
Cardiovascular Disease: The Leading Cause of Death in Adults With Diabetes
Cardiovascular disease — including heart attack, stroke, heart failure, and peripheral arterial disease — is responsible for approximately 50% of all deaths in adults with Type 2 diabetes, making it by far the most consequential of all diabetes complications. Adults with diabetes face a two-to-four times higher risk of heart attack and stroke compared with adults without diabetes, and their cardiovascular events tend to occur earlier, present with fewer warning symptoms, and carry a higher mortality rate. The ACC/AHA classify Type 2 diabetes as a cardiovascular risk equivalent to established heart disease — meaning most adults with Type 2 diabetes are treated similarly to adults who have already had a heart attack, with aggressive LDL lowering, blood pressure control, and consideration of proven cardiovascular-protective medications:
- Coronary artery disease and heart attack: Coronary atherosclerosis in adults with diabetes is typically more diffuse, affects smaller vessel branches, develops at a younger age, and progresses faster than in adults without diabetes — driven by the simultaneous presence of hyperglycemia, insulin resistance, hypertension (present in 70% of adults with Type 2 diabetes), diabetic dyslipidemia (elevated triglycerides, low HDL, and an excess of small dense LDL particles), chronic inflammation, and a prothrombotic state. Adults with cardiac autonomic neuropathy — nerve damage affecting the heart’s pain signaling — frequently experience heart attacks without chest pain, presenting instead with unexplained fatigue, shortness of breath, or sudden blood sugar elevation (silent MI). Large outcome trials (EMPA-REG OUTCOME, LEADER, CANVAS) have demonstrated that SGLT2 inhibitors and GLP-1 receptor agonists — newer classes of diabetes medication — reduce major cardiovascular events by 12–26% in adults with established cardiovascular disease or very high cardiovascular risk, making medication selection in this population a critical clinical decision beyond glucose control alone.
- Stroke and cerebrovascular disease: Adults with diabetes have a two-to-four-fold higher risk of ischemic stroke compared with adults without diabetes, and their strokes tend to be more severe and more likely to result in permanent neurological disability. The risk is driven by the same atherosclerotic mechanisms as coronary disease, compounded by hypertension (a major stroke risk factor) and by the increased risk of atrial fibrillation in adults with diabetes and obesity. Managing blood pressure below 130/80 mmHg, treating dyslipidemia, controlling blood glucose, and addressing atrial fibrillation (with anticoagulation when indicated) each independently reduce stroke risk in adults with diabetes. Our blood pressure monitoring in diabetes guide covers target ranges and monitoring frequency; our cholesterol monitoring in diabetes guide covers lipid management in this population.
- Heart failure and diabetic cardiomyopathy: Adults with diabetes have twice the risk of heart failure compared with adults without diabetes — and this elevated risk exists even in the absence of coronary artery disease or hypertension, a condition known as diabetic cardiomyopathy. Diabetic cardiomyopathy involves AGE-mediated myocardial stiffening, mitochondrial dysfunction in cardiac muscle cells, and increased cardiac fibrosis — leading to diastolic dysfunction (the heart struggles to relax and fill) before systolic dysfunction (pumping weakness) develops. SGLT2 inhibitors have demonstrated 35% reductions in heart failure hospitalization in large outcome trials, and this benefit extends to adults with diabetes without established cardiovascular disease — making heart failure prevention one of the most compelling reasons to consider SGLT2 inhibitor therapy in adults with Type 2 diabetes and high cardiovascular risk.
Diabetic Kidney Disease: From Microalbuminuria to Kidney Failure
Diabetic kidney disease (diabetic nephropathy) affects approximately 1 in 3 adults with diabetes in the United States and is the leading cause of kidney failure requiring dialysis or transplantation. The kidneys’ glomeruli — tiny filtration units dependent on intact capillary structure — are particularly vulnerable to the vascular damage driven by hyperglycemia, hypertension, and AGE accumulation. Kidney disease in diabetes progresses through identifiable stages, and early intervention at the microalbuminuria stage can significantly slow or halt progression:
- Early diabetic kidney disease — microalbuminuria and hyperfiltration: The earliest detectable sign of diabetic kidney disease is the appearance of small amounts of albumin in the urine — “microalbuminuria” — at levels too low to detect on a standard urine dipstick but measurable with the urine albumin-to-creatinine ratio (UACR) test. This microalbuminuria occurs because hyperglycemia and hypertension increase pressure within the glomeruli, damaging their filtration membrane and allowing albumin to “leak” through. Simultaneously, the eGFR (estimated glomerular filtration rate) may be paradoxically elevated early in diabetic kidney disease — a state called hyperfiltration — as the remaining healthy glomeruli work harder to compensate. Both microalbuminuria and hyperfiltration are risk markers for progression to more advanced kidney disease, and both respond to ACE inhibitor/ARB therapy (which reduces intraglomerular pressure) and SGLT2 inhibitor therapy (which reduces hyperfiltration through a tubuloglomerular feedback mechanism). Our diabetic kidney disease: early warning signs guide covers the complete progression pathway and screening tests in detail.
- Progressive kidney disease — declining eGFR and macroalbuminuria: Without intervention, diabetic kidney disease typically progresses from microalbuminuria to macroalbuminuria (protein loss detectable on standard urine dipstick) and then to progressive eGFR decline — the gradual loss of the kidney’s filtering capacity. Each decade of poorly controlled diabetes doubles the rate of eGFR decline. Hypertension — which is both caused by kidney disease (reduced ability to excrete sodium and water) and a driver of kidney disease progression — becomes increasingly difficult to control as kidney function declines. Fluid retention, anemia (from reduced erythropoietin production), metabolic acidosis, hyperkalemia, and hyperphosphatemia all emerge as eGFR falls below 45 mL/min/1.73m² and worsen as eGFR approaches kidney failure (eGFR below 15). The urine albumin testing and eGFR monitoring that track kidney function are covered in our urine albumin test and diabetes guide and our eGFR and kidney function in diabetes guide.
- Kidney failure and renal replacement therapy: End-stage kidney disease (ESKD) requiring dialysis or kidney transplantation is a catastrophic complication that dramatically reduces quality of life and life expectancy. Adults with ESKD from diabetic nephropathy who are on dialysis have a 5-year survival rate of approximately 35% — lower than many cancers. Kidney transplantation provides significantly better survival outcomes but requires lifelong immunosuppression. The most important intervention is prevention: achieving A1C targets, blood pressure targets below 130/80 mmHg (with ACE inhibitor or ARB as first-line), treating microalbuminuria immediately, and using SGLT2 inhibitors (which have shown 30–40% reductions in progression to kidney failure in large outcome trials including CREDENCE and DAPA-CKD) in eligible adults with diabetic kidney disease.
Diabetic Retinopathy and Vision Complications
Diabetic retinopathy is the leading cause of new blindness in working-age adults in the United States — yet it is almost entirely preventable with early detection and treatment. The retina’s microvasculature is exquisitely sensitive to hyperglycemia, and pathological changes begin in the retinal capillaries years before any visual symptoms develop. Regular dilated eye examinations are the cornerstone of retinopathy prevention, because treatment is most effective when initiated in the pre-symptomatic or early symptomatic stage:
- Non-proliferative diabetic retinopathy (NPDR) — the early, treatable stage: Non-proliferative retinopathy encompasses the spectrum of retinal changes from microaneurysms (tiny outpouchings of retinal capillaries caused by pericyte loss) to intraretinal hemorrhages (small bleeds from damaged capillaries), hard exudates (lipid deposits from leaking capillaries), and cotton-wool spots (areas of nerve fiber layer infarction from capillary occlusion). Mild to moderate NPDR typically produces no visual symptoms — the person sees normally despite significant microscopic retinal damage. Vision impairment at this stage, when it occurs, usually results from diabetic macular edema (DME) — swelling of the central retina from leaking capillaries — rather than from the peripheral retinal changes themselves. Anti-VEGF injections into the vitreous are now the first-line treatment for DME with vision impairment, having replaced laser photocoagulation as the standard of care based on large randomized trials showing superior visual acuity outcomes. Our diabetic retinopathy: what to know guide covers the complete staging and treatment pathway.
- Proliferative diabetic retinopathy (PDR) — the advanced, vision-threatening stage: When retinal ischemia becomes severe enough, the retina releases VEGF to stimulate the growth of new blood vessels (neovascularization) — an attempt to restore blood supply. Unfortunately, these new vessels are fragile, grow in disorganized networks into the vitreous, and bleed easily — causing vitreous hemorrhage (sudden severe vision loss from blood filling the eye) and eventually tractional retinal detachment (the fibrovascular membranes contract, pulling the retina away from the pigment epithelium, causing permanent vision loss). Proliferative retinopathy requires urgent ophthalmologic evaluation and treatment — historically with panretinal laser photocoagulation and increasingly with intravitreal anti-VEGF therapy, which has shown efficacy equivalent to panretinal laser while better preserving peripheral vision and visual field.
- Other ocular complications in diabetes — cataracts and glaucoma: Adults with diabetes develop cataracts at a significantly younger age and at higher rates than adults without diabetes — driven by osmotic stress from sorbitol accumulation in the lens, oxidative protein modification, and AGE-mediated lens protein cross-linking. Cataract surgery in adults with diabetes carries a higher risk of postoperative macular edema and requires close ophthalmologic monitoring. Adults with diabetes also have a two-fold higher risk of open-angle glaucoma — both from VEGF-driven neovascularization that can close the trabecular meshwork (neovascular glaucoma in severe PDR) and from an elevated intrinsic risk of conventional open-angle glaucoma. Annual dilated eye examinations, as recommended by the ADA, are the essential intervention for detecting all of these conditions before vision loss occurs.
Diabetic Neuropathy: Nerve Damage in Feet, Hands, and Organs
Diabetic neuropathy is the most common of all diabetes complications, affecting an estimated 50% of adults with diabetes over the course of their lifetime, and it is the complication most directly responsible for the devastating loss of function that many people associate with long-standing diabetes. The peripheral nervous system’s dependence on intact microvasculature for oxygen and nutrient delivery makes it highly vulnerable to the vascular damage driven by chronic hyperglycemia, and axon degeneration begins before any symptoms are noticed:
- Distal symmetric peripheral neuropathy (the most common type): Distal symmetric peripheral neuropathy (DSPN) is the classic “stocking-and-glove” pattern of numbness, tingling, and burning that begins in the toes and feet, then ascends up the legs and (in severe cases) into the hands. The longest nerve fibers — those serving the feet and lower legs — are most vulnerable because they have the farthest distance from the cell body in the spinal cord and are thus most dependent on intact mitochondrial function and microvascular oxygen delivery along their entire length. DSPN damages both large myelinated fibers (responsible for vibration and position sense) and small unmyelinated fibers (responsible for pain and temperature sensation). Loss of small fiber protective sensation — the ability to feel a sharp pin, a hot surface, or a sharp-edged stone in a shoe — is the key risk factor for diabetic foot injury, infection, and amputation, because the person can no longer feel the damage accumulating. Our diabetic neuropathy: symptoms and prevention guide covers the complete clinical picture and treatment options.
- Autonomic neuropathy — when the body’s automatic functions are affected: Autonomic neuropathy occurs when the nerves controlling automatic body functions — heart rate, blood pressure, digestion, sweating, bladder, and sexual function — are damaged by diabetes. Cardiovascular autonomic neuropathy (CAN) — the most dangerous form — causes resting tachycardia, impaired heart rate variability (a risk marker for sudden cardiac death), exercise intolerance, and orthostatic hypotension (blood pressure dropping on standing, causing dizziness and falls). Gastroparesis — delayed gastric emptying from vagal nerve damage — causes nausea, vomiting, erratic food absorption, and unpredictable post-meal glucose excursions that make blood sugar management dramatically more difficult. Bladder dysfunction from autonomic neuropathy causes urinary retention, incomplete emptying, and recurrent urinary tract infections. Erectile dysfunction and female sexual dysfunction are common in adults with long-standing diabetes, mediated by both autonomic neuropathy and vascular disease affecting genital blood flow.
- Focal and multifocal neuropathies — sudden-onset nerve-specific syndromes: Beyond the diffuse peripheral and autonomic neuropathies, adults with diabetes can develop focal neuropathies — sudden-onset dysfunction of a single nerve or nerve root. Diabetic amyotrophy (lumbosacral radiculoplexus neuropathy) causes severe, asymmetric, proximal leg pain and weakness — often beginning with intense thigh and hip pain before profound muscle wasting — that is frequently misdiagnosed as a herniated disc. Cranial nerve palsies — most commonly of the oculomotor nerve (cranial nerve III), causing sudden double vision and drooping eyelid — occur in adults with diabetes and are usually self-resolving but require prompt evaluation to rule out intracranial aneurysm. Mononeuropathies affecting the median nerve (carpal tunnel syndrome), ulnar nerve, and peroneal nerve (foot drop) are also more common in adults with diabetes than in the general population.
Diabetic Foot Complications: Why Feet Deserve Special Attention
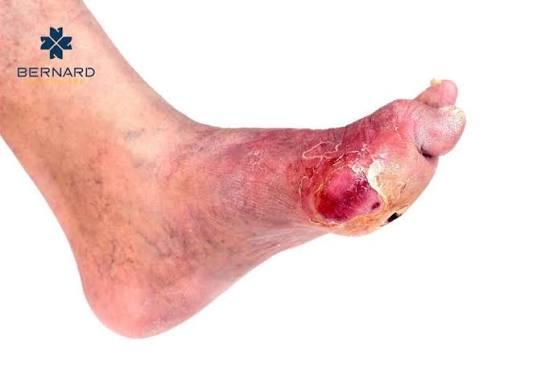
Diabetic foot complications — ulcers, infections, and lower extremity amputations — represent the confluence of neuropathy (loss of protective sensation), vascular disease (reduced healing capacity), and immune dysfunction (impaired infection fighting) that makes the diabetic foot uniquely vulnerable to injuries that would be minor nuisances in healthy adults. Approximately 15% of adults with diabetes will develop a foot ulcer during their lifetime, and diabetic foot disease accounts for more hospital bed-days than any other diabetes complication:
- The diabetic foot ulcer — how minor injuries become major crises: A typical diabetic foot ulcer begins with a pressure injury that the person cannot feel — a poorly fitting shoe rubbing the side of a toe, a pebble inside a shoe, or a plantar callus forming over a bony prominence. In a foot with intact sensation, these would cause pain that prompts attention and protective behavior. In a foot with severe neuropathy, the injury goes unnoticed for days or weeks while it deepens into a full-thickness wound. Once the skin is broken, impaired blood flow reduces the oxygen and immune cell delivery needed for healing, while elevated blood glucose impairs neutrophil function and promotes bacterial growth. The result is a wound that does not heal normally — and may rapidly progress from a superficial ulcer to a deep wound involving tendon, bone, or joint, at which point osteomyelitis (bone infection) is a major risk. Our diabetic foot problems: prevention and care guide covers the complete prevention and wound care framework.
- Peripheral arterial disease — the vascular component of foot risk: Peripheral arterial disease (PAD) — atherosclerosis of the arteries of the legs and feet — is dramatically more common in adults with diabetes than in the general population, occurring at a younger age, with more distal (below-the-knee) involvement, and with more severe calcification that makes interventions more technically challenging. PAD reduces blood flow to the feet, impairing wound healing and creating ischemic conditions where bacteria thrive and antibiotics penetrate poorly. The combination of neuropathy (loss of sensation) and PAD (loss of blood flow) is particularly dangerous — the person cannot feel the wound, and the wound cannot heal. Ankle-brachial index (ABI) measurement — comparing blood pressure at the ankle to the arm — is the standard screening test for PAD in adults with diabetes and lower extremity symptoms; calcification of tibial arteries in diabetes can falsely elevate ABI, requiring alternate tests (toe-brachial index, arterial Doppler waveform analysis) for accurate assessment.
- Charcot neuroarthropathy — bone destruction from neuropathy: Charcot neuroarthropathy (Charcot foot) is a severe, potentially disabling complication in which neuropathy leads to fractures and dislocations of the bones of the foot and ankle — usually in the midfoot — that the person cannot feel. The bone destruction is driven by undetected trauma on an insensate foot, combined with hyperemia (increased blood flow) from autonomic neuropathy that activates osteoclasts and increases bone resorption. The acute Charcot foot presents as a hot, swollen, red foot — often misdiagnosed as cellulitis or deep vein thrombosis — and requires immediate non-weight-bearing and specialist evaluation to prevent progressive collapse into the classic “rocker-bottom” deformity that dramatically increases ulceration risk. Early recognition and total contact casting, immobilization, and offloading are essential to preventing permanent structural foot deformity.
Evidence-Based Strategies to Prevent Diabetes Complications
The landmark diabetes trials — the UKPDS in Type 2 diabetes and the DCCT/EDIC in Type 1 diabetes — established definitively that intensive blood glucose control, applied early in the course of the disease, reduces microvascular complication rates by 25–76% and provides a sustained legacy of complication reduction even after glucose control is no longer strictly maintained. More recent evidence from cardiovascular and kidney outcome trials has added SGLT2 inhibitors and GLP-1 receptor agonists to the prevention toolkit, providing organ protection beyond glucose control alone:
- Glycemic control — the foundation of complication prevention: Every 1% reduction in A1C reduces microvascular complications (retinopathy, nephropathy, neuropathy) by approximately 25–37% in adults with Type 2 diabetes. The benefit for macrovascular complications (heart attack, stroke) is also present but requires longer follow-up to demonstrate because cardiovascular events occur over decades and are influenced by many factors beyond glucose alone. Current ADA targets recommend A1C below 7% for most non-elderly adults, with individualization for older adults or those with frequent hypoglycemia, limited life expectancy, or advanced complications. The A1C monitoring schedule and what different A1C levels mean for complication risk are covered in our A1C testing schedule guide.
- Blood pressure control — the second pillar of comprehensive diabetes risk reduction: Hypertension is both a cause and consequence of diabetic kidney disease, and it independently drives retinopathy progression, cardiovascular events, and stroke risk. The UKPDS demonstrated that tight blood pressure control (systolic below 150 mmHg, now recognized as insufficient) reduced stroke by 44%, heart failure by 56%, and diabetic retinopathy progression by 34% compared with less aggressive blood pressure management. Current guidelines target blood pressure below 130/80 mmHg in adults with diabetes and established cardiovascular disease or kidney disease. ACE inhibitors and ARBs are first-line antihypertensive agents in adults with diabetes because they reduce intraglomerular pressure and slow kidney disease progression beyond their blood pressure effects. SGLT2 inhibitors reduce blood pressure 3–5 mmHg systolic and have demonstrated kidney-protective effects independent of glucose and blood pressure lowering. Our blood pressure monitoring in diabetes guide covers home monitoring techniques and blood pressure targets.
- Lipid management — cardiovascular protection through LDL reduction: Statin therapy reduces major cardiovascular events by approximately 20–25% per 1 mmol/L (39 mg/dL) LDL reduction in adults with diabetes — a proportional benefit that is especially clinically significant given the high baseline cardiovascular risk in this population. The ADA recommends moderate-intensity statin therapy for all adults with diabetes aged 40–75, with high-intensity therapy for adults with established cardiovascular disease or very high cardiovascular risk, targeting LDL below 70 mg/dL. Adults who do not achieve LDL targets on maximally tolerated statin therapy are candidates for additional LDL-lowering therapy with ezetimibe or PCSK9 inhibitors. Our cholesterol monitoring in diabetes guide covers lipid targets and monitoring intervals. The CDC’s diabetes complications overview provides population-level data on complication prevalence and prevention impact.
- Consistent monitoring and specialist care — catching complications before irreversible damage: Regular screening for each major complication — annual dilated eye examination, annual urine albumin and eGFR measurement, annual comprehensive foot examination, regular blood pressure measurement at every diabetes visit — is the mechanism by which early-stage, reversible complications are identified before they progress to permanent organ damage. The NIDDK recommends that all adults with Type 2 diabetes undergo comprehensive complication screening at diagnosis (since many have had the condition for years before diagnosis) and annually thereafter. The complete monitoring schedule that integrates all complication screenings into a coordinated annual care plan is in our annual diabetes care checklist. The NIDDK’s diabetes complication prevention information provides authoritative clinical guidance on the full spectrum of evidence-based prevention strategies for each complication category.
Sources: American Diabetes Association — Standards of Medical Care in Diabetes, complication screening and prevention; CDC — diabetes complication statistics; NIDDK — diabetic kidney disease, retinopathy, neuropathy, and cardiovascular disease prevention; UKPDS (UK Prospective Diabetes Study) — blood glucose and blood pressure control reducing microvascular and macrovascular complications in Type 2 diabetes; DCCT/EDIC — intensive glucose control and legacy effect in Type 1 diabetes; cardiovascular risk equivalence of Type 2 diabetes (ACC/AHA guidelines); SGLT2 inhibitor cardiovascular and kidney outcome trials (EMPA-REG OUTCOME, CANVAS, CREDENCE, DAPA-CKD); GLP-1 receptor agonist cardiovascular trials (LEADER, SUSTAIN-6, HARMONY); statin CVD risk reduction in diabetes (CTT meta-analysis); diabetic retinopathy staging and anti-VEGF treatment (DRCR.net Protocol T, RISE/RIDE trials); diabetic neuropathy epidemiology and pathophysiology; Charcot neuroarthropathy diagnosis and management; peripheral arterial disease in diabetes; diabetic foot ulcer risk and amputation prevention.
Finally a resource that explains diabetes complications: what adults should know in plain language. I appreciate that the article is careful about distinguishing between what is known and what is still being researched. Exactly the kind of evidence-based information that is hard to find in one place.
Finally a resource that explains diabetes complications: what adults should know in plain language. The specific numbers and thresholds mentioned are exactly what I needed to understand my results. I wish I had found this article earlier — would have saved a lot of confusion.
I have been reading about diabetes complications: what adults should know for weeks and this is the most thorough guide I found. The connection between lifestyle choices and long-term outcomes is explained clearly here. Will definitely be coming back to this site for more health information.