
One of the most challenging aspects of diabetic kidney disease is that it gives no warning — not during its early stages, when it is most treatable, and not during its middle stages, when it is progressing toward kidney failure. The early warning signs of diabetic kidney disease are laboratory findings, not symptoms: trace amounts of albumin in the urine detected by a sensitive test, a subtle decline in eGFR measured by a blood test, or rising blood pressure that proves resistant to control. By the time symptoms appear — swelling in the legs, fatigue, shortness of breath, nausea — a person has typically lost more than half of their kidney function. This is why the NIDDK, the ADA, and the American Society of Nephrology all emphasize laboratory screening as the cornerstone of diabetic kidney disease management: detecting the disease when it is still microscopic — when interventions can stop its progression — requires testing that looks for what the person cannot feel.
Approximately 1 in 3 adults with diabetes in the United States has diabetic kidney disease (DKD) — representing over 12 million Americans. DKD is the leading cause of end-stage kidney disease (ESKD) in the United States, responsible for approximately 44% of all new ESKD cases each year. Adults with diabetes who develop ESKD requiring dialysis have a 5-year survival rate of approximately 35%, lower than many cancers. Yet early DKD — detected at the microalbuminuria stage — responds dramatically to treatment: ACE inhibitors or ARBs reduce the rate of progression to macroalbuminuria by 60–70%, and SGLT2 inhibitors reduce the risk of kidney failure progression by 30–40% in adults with DKD.
How Diabetic Kidney Disease Develops: The Glomerular Damage Cascade
The kidneys filter blood through approximately one million specialized filtration units called glomeruli — each consisting of a tightly coiled capillary tuft surrounded by specialized cells. These glomeruli are exquisitely sensitive to the combined assault of hyperglycemia, hypertension, and the downstream effects of both, which together drive a cascade of structural and functional changes that progressively destroy filtration capacity:
- Glomerular hyperfiltration — the paradoxical early phase: In the early months to years of diabetes, before any structural damage is visible, the glomeruli actually filter more than normal — a state called glomerular hyperfiltration. This occurs because hyperglycemia triggers tubuloglomerular feedback changes that dilate the afferent arteriole (increasing glomerular blood flow and pressure) while constricting the efferent arteriole — a hemodynamic change that increases the filtration fraction and raises intraglomerular hydraulic pressure. This elevated pressure damages the delicate glomerular filtration membrane, setting in motion the structural changes that eventually destroy filtration capacity. Paradoxically, adults in the hyperfiltration phase have a supranormal eGFR (above 120–130 mL/min/1.73m²) — making standard eGFR thresholds for kidney disease detection inadequate for identifying this earliest, most treatable phase. SGLT2 inhibitors reduce hyperfiltration by blocking sodium reabsorption in the proximal tubule, restoring the tubuloglomerular feedback mechanism that normally limits glomerular pressure — and this mechanism is likely a major contributor to their remarkable kidney-protective effects demonstrated in CREDENCE and DAPA-CKD trials.
- Glomerular basement membrane thickening and mesangial expansion: As hyperglycemia and glomerular hypertension persist, the glomerular basement membrane (GBM) — the filtration membrane through which blood is processed — progressively thickens from the accumulation of type IV collagen, laminin, and fibronectin driven by AGE formation and TGF-beta (transforming growth factor beta) signaling. Simultaneously, the mesangium — the supportive tissue between glomerular capillaries — expands as mesangial cells produce excess matrix in response to the same AGE and TGF-beta signals. GBM thickening reduces the permselectivity of the filtration barrier, allowing proteins (particularly albumin) to pass through that would normally be retained. Mesangial expansion compresses the capillary loops, reducing the filtration surface area and contributing to the eGFR decline that occurs in later disease stages. These structural changes are visible on kidney biopsy and represent the histological hallmarks of diabetic nephropathy.
- Podocyte loss and albuminuria: Podocytes are the specialized visceral epithelial cells that line the outer surface of glomerular capillaries — their interdigitating foot processes create the final barrier against protein loss. Podocytes are terminally differentiated (they cannot regenerate), making their loss irreversible and their injury a key driver of progressive proteinuria. In diabetic nephropathy, podocytes are damaged by the mechanical stress of glomerular hypertension, the direct toxic effects of AGEs, the inflammatory cytokines produced by mesangial cells, and angiotensin II (which causes podocyte contraction and foot process effacement). Podocyte loss correlates directly with albuminuria severity and with the rate of eGFR decline — and urinary podocyte markers (exfoliated podocytes in urine, measurable by specialized testing) may predict progression more sensitively than albuminuria alone. ACE inhibitors and ARBs reduce podocyte injury by reducing efferent arteriolar resistance (lowering intraglomerular pressure) and through direct anti-inflammatory effects on the glomerulus. Our urine albumin test and diabetes guide covers the UACR testing that detects podocyte-driven albuminuria at the earliest stage.
- Tubulointerstitial fibrosis and eGFR decline: In advanced diabetic kidney disease, damage extends beyond the glomeruli into the tubulointerstitium — the tubular structures and surrounding connective tissue that process the filtrate produced by glomeruli. Chronic glomerular protein leak (proteinuria) exposes tubular cells to high concentrations of albumin and other proteins, triggering inflammatory signaling that drives tubular cell injury and activation of interstitial fibroblasts. The result is progressive tubulointerstitial fibrosis — the replacement of functional kidney tissue with non-functional scar tissue — which directly reduces eGFR. Interstitial fibrosis, rather than glomerulosclerosis alone, correlates most strongly with the rate of eGFR decline and with long-term kidney function trajectory. This is why SGLT2 inhibitors — which reduce tubular protein reabsorption burden in addition to their glomerular hemodynamic effects — have shown superior kidney protection beyond what ACE inhibitors and ARBs alone provide in adults with DKD and heavy proteinuria. Our eGFR and kidney function in diabetes guide covers the eGFR measurements that track this progression. The NIDDK’s diabetic kidney disease information provides authoritative clinical guidance on pathophysiology and management.
Early Warning Signs of Diabetic Kidney Disease: What Testing Reveals
The early warning signs of diabetic kidney disease are detectable only through laboratory testing — the person typically feels completely normal during the years when intervention is most effective. Two tests form the foundation of DKD screening: the urine albumin-to-creatinine ratio (UACR), which detects glomerular protein leak, and the eGFR, which measures the kidney’s overall filtration capacity. The ADA recommends annual testing of both in all adults with Type 2 diabetes (beginning at diagnosis) and in adults with Type 1 diabetes after 5 years:
- Microalbuminuria detected by UACR — the earliest laboratory warning sign: Normal urine contains essentially no albumin — the glomerular filtration barrier prevents its passage. In early DKD, small amounts of albumin begin to leak through the damaged filtration membrane, appearing in the urine at concentrations too low to detect on standard urine dipstick but measurable with the sensitive UACR test. UACR below 30 mg/g creatinine is normal; UACR 30–299 mg/g indicates moderately increased albuminuria (formerly called “microalbuminuria”); UACR above 300 mg/g indicates severely increased albuminuria (formerly called “macroalbuminuria” or “overt nephropathy”). Microalbuminuria — the 30–299 mg/g range — is the critical early warning: it represents glomerular damage that has exceeded the threshold detectable by urine dipstick but has not yet progressed to the massive proteinuria of advanced nephropathy. Adults with microalbuminuria who receive ACE inhibitor or ARB therapy and achieve A1C and blood pressure targets have a 60–70% lower rate of progression to macroalbuminuria than those who do not — making this the highest-value intervention window in the entire DKD disease course.
- eGFR decline — detecting filtration capacity loss: The estimated glomerular filtration rate (eGFR) — calculated from serum creatinine, age, and sex using the 2021 CKD-EPI equation — measures the kidney’s overall filtration capacity. Normal eGFR is approximately 90–120 mL/min/1.73m² in young adults; eGFR naturally declines 1 mL/min/1.73m² per year with normal aging. In DKD, eGFR can decline at rates of 3–10 mL/min/1.73m² per year in adults with poorly controlled disease — leading to kidney failure in years rather than decades. Importantly, eGFR may remain normal (above 60 mL/min/1.73m²) in early DKD despite significant structural glomerular damage — the kidney’s ability to compensate by increasing single-nephron filtration rate masks the loss of nephrons until approximately 50% of filtration capacity is gone. This compensatory mechanism is why eGFR screening must always be combined with UACR testing: UACR detects early damage when eGFR is still normal, and eGFR tracks progression once compensation is exceeded.
- Blood pressure — the clinical sign that accompanies kidney damage: Hypertension is both a cause and consequence of diabetic kidney disease. Early DKD causes sodium and water retention (from reduced sodium excretion capacity) and activation of the renin-angiotensin-aldosterone system (RAAS) as ischemic kidney tissue signals for more blood flow — both of which raise blood pressure. As kidney disease progresses, blood pressure becomes increasingly difficult to control and often requires multiple antihypertensive medications. Conversely, existing hypertension significantly accelerates DKD progression by increasing intraglomerular pressure. New-onset or worsening hypertension in an adult with diabetes should prompt evaluation of kidney function and UACR, because it may represent the first clinical sign of DKD before any laboratory changes are detected. The blood pressure monitoring that is essential for DKD prevention and management is covered in our blood pressure monitoring in diabetes guide.
Symptoms of Advanced Diabetic Kidney Disease
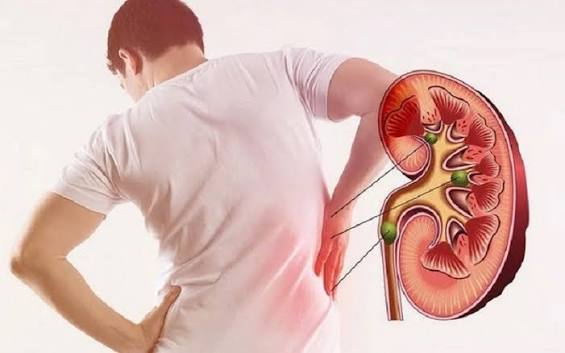
While early DKD is asymptomatic, moderate to advanced stages of the disease produce recognizable symptoms that — if the diagnosis of DKD has not already been established through screening — warrant immediate evaluation. The symptoms of advanced kidney disease in diabetes result from the kidney’s failure to perform its multiple functions: filtering waste, regulating fluid balance, maintaining electrolyte homeostasis, producing erythropoietin, and activating vitamin D:
- Fluid retention and edema — kidney failure to excrete sodium and water: As eGFR declines below 45 mL/min/1.73m², the kidney’s ability to excrete the sodium and water from a normal diet is reduced, leading to fluid accumulation. Peripheral edema — swelling of the feet, ankles, and lower legs — is often the first symptom adults notice. As disease progresses, fluid accumulation spreads to the hands, face, and abdomen. Pulmonary edema — fluid accumulation in the lungs causing shortness of breath, particularly when lying flat — can develop rapidly in adults with severe kidney function impairment and represents a medical emergency. Adults with new or worsening lower extremity edema in the setting of diabetes should have kidney function and UACR assessed promptly.
- Uremic symptoms — the accumulation of waste products: As eGFR declines below 20–25 mL/min/1.73m², uremic waste products accumulate in the blood to levels that impair organ function and produce characteristic symptoms: fatigue and weakness (from anemia of chronic kidney disease — reduced erythropoietin production — and from uremic inhibition of red blood cell production), nausea, vomiting, and loss of appetite (from uremic gastropathy), cognitive slowing and difficulty concentrating (uremic encephalopathy), metallic taste and uremic fetor (distinctive breath odor from urea metabolism), itching (uremic pruritus — from calcium phosphate crystal deposition in the skin), and muscle cramps (from electrolyte imbalances). Adults with these symptoms require urgent nephrology evaluation and discussion of renal replacement therapy timing.
- Electrolyte abnormalities — hyperkalemia and metabolic acidosis: The kidney is essential for excreting potassium and maintaining acid-base balance. In advanced DKD, reduced potassium excretion leads to hyperkalemia (elevated blood potassium), which increases the risk of potentially fatal cardiac arrhythmias. This risk is particularly relevant in adults on ACE inhibitors or ARBs (which reduce aldosterone-mediated potassium excretion) and in adults with reduced urine output. Metabolic acidosis — failure to excrete the daily acid load produced by normal metabolism — also develops in advanced DKD and contributes to bone disease, muscle wasting, accelerated kidney disease progression (acidosis itself is toxic to kidney tubular cells), and hyperkalemia exacerbation. Sodium bicarbonate supplementation for metabolic acidosis correction has been shown in randomized trials to slow DKD progression — a relatively simple intervention with meaningful impact on kidney disease trajectory. The comprehensive monitoring that detects these changes is outlined in our annual diabetes care checklist.
Treating and Slowing Diabetic Kidney Disease Progression
The past decade has produced a transformation in DKD treatment — the evidence base now includes not only ACE inhibitors/ARBs and glycemic control (the longstanding pillars) but also SGLT2 inhibitors, finerenone (a novel mineralocorticoid receptor antagonist), and GLP-1 receptor agonists, each with kidney outcome trial evidence. Comprehensive DKD management now targets glucose, blood pressure, the renin-angiotensin system, inflammation, and fibrosis simultaneously:
- ACE inhibitors and ARBs — the established renin-angiotensin system blockade: ACE inhibitors (lisinopril, ramipril, enalapril) and ARBs (losartan, irbesartan, valsartan) have been the cornerstone of DKD management since the RENAAL (losartan) and IDNT (irbesartan) trials demonstrated their ability to reduce progression to kidney failure by 16–28% in adults with Type 2 diabetes and macroalbuminuria. Their kidney protection derives from reducing efferent arteriolar constriction (lowering intraglomerular pressure), reducing podocyte injury, decreasing TGF-beta-driven fibrosis, and reducing proteinuria by 40–50%. ACE inhibitors and ARBs are first-line antihypertensive therapy in all adults with diabetes and albuminuria, and should be used even if blood pressure is already at target — because their kidney protection extends beyond their blood pressure-lowering effect. Potassium and creatinine must be monitored after initiation, and the medications should be held during episodes of volume depletion (illness with vomiting, diarrhea, or poor oral intake).
- SGLT2 inhibitors — the transformative new class for kidney protection: The CREDENCE trial (canagliflozin) and DAPA-CKD trial (dapagliflozin) demonstrated that SGLT2 inhibitors reduce the composite outcome of kidney failure, doubling of serum creatinine, or death from kidney causes by 30–40% in adults with DKD — benefits that are additive to those of ACE inhibitors/ARBs and that persist even in adults with eGFR as low as 25 mL/min/1.73m² (below which most SGLT2 inhibitors lose glucose-lowering efficacy, but kidney protection persists). The mechanisms include reduction of glomerular hyperfiltration, reduction of tubular protein reabsorption burden, reduction of intraglomerular pressure, anti-inflammatory effects, and metabolic effects (reduced mitochondrial oxidative stress). Current ADA guidelines recommend SGLT2 inhibitors for all adults with Type 2 diabetes and DKD who can tolerate them. Our diabetes complications: what adults should know guide covers the complete treatment landscape for all diabetes complications including DKD.
- Glycemic and blood pressure targets in DKD: Glycemic control targets in adults with DKD require individualization — intensive glucose lowering can increase hypoglycemia risk (because the kidney normally degrades insulin, and as eGFR declines, insulin levels rise and hypoglycemia becomes more frequent), and many oral diabetes medications require dose adjustment or are contraindicated at low eGFR (metformin should generally be stopped below eGFR 30; sulfonylureas accumulate and cause prolonged hypoglycemia). Blood pressure targets below 130/80 mmHg are appropriate for most adults with DKD, with ACE inhibitor or ARB as first-line and addition of a dihydropyridine calcium channel blocker or thiazide diuretic (or loop diuretic in advanced DKD) as needed for control. The A1C monitoring schedule and kidney-specific considerations are covered in our A1C testing schedule guide. The cholesterol management that reduces cardiovascular risk in adults with DKD is covered in our cholesterol monitoring in diabetes guide. The National Kidney Foundation’s DKD resources and the CDC’s diabetes and CKD information provide authoritative guidance on kidney protection in adults with diabetes.
When to See a Kidney Specialist (Nephrologist)
Primary care providers and endocrinologists manage the majority of diabetic kidney disease — but certain clinical situations warrant referral to a nephrologist (kidney specialist) for co-management or transfer of kidney care:
- eGFR below 30 mL/min/1.73m² (CKD Stage 4): At this level of kidney function, preparation for potential renal replacement therapy — dialysis or transplant — should begin. A nephrologist will discuss modality options (hemodialysis, peritoneal dialysis, transplant), assess transplant candidacy, place arteriovenous fistulas if hemodialysis is planned (which require 3–6 months to mature before use), and manage the complex metabolic disturbances of advanced CKD. Early referral at eGFR 30 rather than waiting for kidney failure significantly improves outcomes by allowing planned rather than emergency initiation of dialysis.
- Rapid eGFR decline (more than 5 mL/min/1.73m² per year): Diabetic kidney disease typically progresses slowly — 1–3 mL/min/1.73m² per year in well-controlled adults. Rapid decline — loss of 5 or more mL/min/1.73m² per year — suggests either accelerated DKD or a superimposed acute process (renovascular disease, acute tubular injury, nephrotoxic medication, or another glomerular disease) that warrants specialist evaluation. A kidney biopsy may be needed to distinguish diabetic nephropathy from another diagnosis.
- Heavy proteinuria, hematuria, or atypical presentation: Most DKD begins as microalbuminuria without blood in the urine. The presence of significant hematuria (blood in the urine) in addition to proteinuria raises the possibility of a non-diabetic glomerular disease — such as IgA nephropathy, membranous nephropathy, or ANCA-associated vasculitis — that requires biopsy confirmation and different treatment. Adults with heavy proteinuria (UACR above 1000 mg/g) out of proportion to their eGFR, or with rapidly declining eGFR despite appropriate treatment, should be evaluated by a nephrologist.
Lifestyle Modifications That Support Kidney Health in Diabetes
In addition to medications, several lifestyle modifications have evidence supporting kidney function preservation in adults with diabetic kidney disease. These are not replacements for pharmacological therapy but important adjuncts that reduce the burden on already-stressed kidneys and address modifiable risk factors that accelerate DKD progression:
- Dietary protein restriction in advanced DKD: High dietary protein intake increases glomerular filtration rate and intraglomerular pressure — accelerating the hyperfiltration injury in already-damaged glomeruli. Current guidelines recommend modest protein restriction to 0.8 g/kg/day (the standard recommended daily allowance for adults) in adults with DKD — avoiding the high-protein diets often promoted for weight management, which may accelerate kidney disease in people already vulnerable. Adults on dialysis actually require higher protein intake (1.2–1.5 g/kg/day) to compensate for protein losses during dialysis treatment. A registered dietitian with kidney disease expertise should guide protein intake recommendations based on eGFR stage, dialysis status, and nutritional needs.
- Sodium restriction for blood pressure and fluid management: Dietary sodium restriction to below 2,300 mg/day (the current Dietary Guidelines for Americans recommendation) reduces blood pressure in adults with CKD — making antihypertensive medications more effective — and reduces fluid retention. In adults with advanced DKD and impaired sodium excretion, sodium restriction becomes increasingly important to prevent edema and hypertension that worsen kidney disease. Adults with DKD who consume high-sodium processed foods despite taking multiple antihypertensive medications often achieve significant blood pressure improvement with sodium restriction alone. Low-sodium dietary patterns that emphasize whole foods, vegetables, legumes, and whole grains (consistent with the DASH diet framework) also reduce the dietary acid load — contributing to metabolic acidosis prevention in CKD.
- Avoiding nephrotoxic medications and substances: Adults with DKD must avoid medications and substances that damage kidneys or reduce kidney blood flow: NSAIDs (ibuprofen, naproxen) — which constrict the afferent arteriole and reduce glomerular filtration, particularly dangerous in adults who are dehydrated or on ACE inhibitors/ARBs — should be avoided entirely. Contrast dye for imaging procedures requires special precautions in adults with reduced eGFR (pre-hydration, choice of iso-osmolar contrast agents, avoidance of high contrast volumes). Herbal supplements — many of which contain nephrotoxic compounds (aristolochic acid, found in many traditional herbal remedies, causes progressive nephropathy) — should be used with extreme caution and always disclosed to the treating physician. The complete diabetes monitoring schedule that coordinates kidney function testing with all other diabetes care is in our annual diabetes care checklist.
Sources: American Diabetes Association — Standards of Medical Care in Diabetes, kidney disease management and screening; NIDDK — diabetic kidney disease overview and progression; National Kidney Foundation — KDIGO 2022 clinical practice guideline for diabetes management in CKD; CDC — diabetic kidney disease prevalence and ESKD statistics; CREDENCE trial — canagliflozin reducing kidney failure and cardiovascular events by 30% in adults with DKD; DAPA-CKD trial — dapagliflozin reducing kidney disease progression by 39% regardless of diabetes status; RENAAL trial — losartan reducing kidney failure by 28% in Type 2 diabetes with macroalbuminuria; IDNT trial — irbesartan reducing kidney failure by 16% in Type 2 diabetes with nephropathy; FIDELIO-DKD and FIGARO-DKD — finerenone reducing DKD progression and cardiovascular events; glomerular hyperfiltration — afferent dilation, efferent constriction, and tubuloglomerular feedback; glomerular basement membrane thickening and mesangial expansion in diabetic nephropathy histology; podocyte loss as driver of albuminuria and eGFR decline; UACR microalbuminuria threshold (30 mg/g) for early DKD detection; eGFR decline rates in DKD (3–10 mL/min/year with poor control); sodium bicarbonate for metabolic acidosis slowing CKD progression; hyperkalemia risk with RAAS blockade in advanced CKD; tubulointerstitial fibrosis as primary determinant of eGFR trajectory; ACE inhibitor and ARB reducing albuminuria by 40–50% and progression to macroalbuminuria by 60–70%.
My doctor recommended I look into diabetic kidney disease: early warning signs and this article covered it perfectly. What I liked most was that the article didn’t just say what to avoid — it also gave alternatives. Appreciate the effort that went into researching and writing this — it shows.
Bookmarked this article on diabetic kidney disease: early warning signs immediately — going to reference it regularly. I appreciate that the article is careful about distinguishing between what is known and what is still being researched. Forwarding this to others in my support group who are dealing with similar issues.
Finally a resource that explains diabetic kidney disease: early warning signs in plain language. The section on managing this condition day-to-day was especially useful for planning. Shared this with three friends who are dealing with related issues. Very useful resource.