
Life on dialysis is something most people facing kidney failure can only partially imagine in advance — the treatment schedules, dietary changes, physical sensations, emotional adjustments, and practical limitations are difficult to convey until you are living them. Yet understanding what life on dialysis actually looks like in day-to-day practice can dramatically reduce anxiety, help patients make better modality choices before starting, and set realistic expectations that make the adjustment period more manageable. This guide describes life on dialysis from the patient’s perspective: what a typical day or week looks like on hemodialysis vs peritoneal dialysis, how the physical experience of dialysis changes over time, how dietary restrictions shape daily eating, what employment and travel on dialysis involve, the emotional and psychological dimensions of long-term dialysis, and what the research says about quality of life on each modality. For the technical details of how each treatment works, see the hemodialysis guide and the peritoneal dialysis guide; for the preparation process, see preparing for dialysis.

A Typical Week on In-Center Hemodialysis
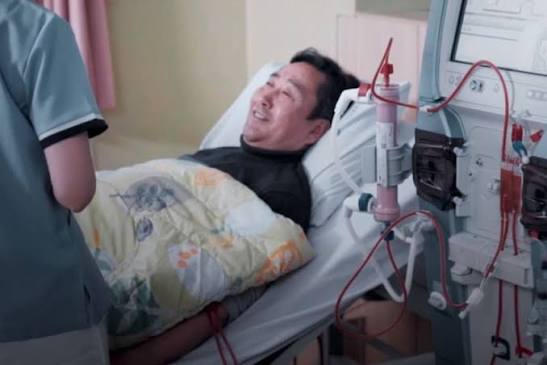
In-center hemodialysis (HD) structures the week around three treatment sessions, which most dialysis centers schedule on either a Monday-Wednesday-Friday or Tuesday-Thursday-Saturday pattern. Each session typically lasts 3.5–4 hours — but the total time commitment is longer: patients arrive 15–30 minutes before the session begins, spend time in the waiting area and then getting connected to the machine (blood pressure check, weight measurement, access examination, needle insertion or catheter connection), run for 3.5–4 hours, and then spend 20–30 minutes at the end being disconnected, having their access site dressed, and having their post-session blood pressure and weight recorded. Most patients spend 5–6 hours at or traveling to and from the dialysis center on each treatment day. The three weekly dialysis days are rigidly scheduled — missing a session causes uremic toxins and fluid to accumulate for an extra two or three days rather than the usual one-to-two, which can cause significant symptoms (fatigue, fluid retention, shortness of breath) and in extreme cases life-threatening hyperkalemia. The result is that dialysis days dominate the schedule: most in-center HD patients organize their work, family commitments, appointments, and activities around the three fixed treatment days. Early morning shifts (starting at 5–6 am) allow patients to complete treatment before a work or school day; afternoon shifts (1–2 pm) accommodate those with morning commitments; evening shifts (5–6 pm) are available at some centers. What happens during the session: most patients bring a phone, tablet, book, or headphones; some centers have individual televisions at each chair; patients can eat a small snack during the session (though eating can contribute to blood pressure changes during treatment in some patients). Many patients report feeling tired immediately after treatment — the rapid fluid and waste removal exerts a cardiovascular toll, and “post-dialysis fatigue” lasting several hours after a session is common, particularly in the first months. On the four non-dialysis days, patients typically feel progressively more symptomatic (more fatigue, more fluid retention) as uremic toxins accumulate; the day before a treatment session (particularly Sunday before a Monday session, or Thursday before a Friday-Saturday HD day) is commonly the worst day in the week. Over time, most patients adapt to this pattern, though it never fully feels “normal” — the physical constraints of in-center HD are real and ongoing. Despite these challenges, many patients live full and active lives on in-center HD, with work, family activities, travel, and social life adapted around the treatment schedule. The NIDDK provides a patient perspective guide at the NIDDK hemodialysis page.
A Typical Day on Peritoneal Dialysis at Home
Life on peritoneal dialysis (PD) looks very different from in-center hemodialysis: rather than three long clinic visits per week, PD patients perform treatment at home — either manually throughout the day (CAPD) or automatically at night while they sleep (APD). This difference in treatment schedule has profound implications for daily life. CAPD (Continuous Ambulatory Peritoneal Dialysis) involves three to five manual exchanges per day. A typical CAPD day begins when the patient gets up and performs the first exchange: they take their medication, connect the catheter transfer set to a new dialysate bag, drain the overnight dwell (the spent dialysate from the long overnight soak), fill with fresh dialysate, disconnect, and go about the morning. Each exchange takes 30–40 minutes of active time. The patient then carries the full peritoneal cavity of dialysate for 4–6 hours while going about their normal activities — working, driving, exercising, socializing — and performs the next exchange at midday, again in the early evening, and leaves an overnight long dwell in place before sleeping. CAPD patients do not need a machine, only a supply of dialysate bags, a transfer set, and a clean space to perform exchanges; many CAPD patients perform exchanges in a quiet clean space at work or at family members’ homes, maintaining an essentially normal daily schedule with the exchanges building into the day’s routine. The key discipline required is meticulous sterile technique at every connection and disconnection to prevent peritonitis; patients and their families learn this through intensive training and it becomes second nature over time. APD (Automated Peritoneal Dialysis) looks even less intrusive during the day: the patient connects to the cycler machine before sleep, the machine performs 4–8 exchanges automatically overnight (usually 8–10 hours), and the patient disconnects in the morning and goes through the day with a single daytime dwell (or with an empty abdomen, depending on the APD prescription). The daytime is essentially free of dialysis for APD patients — no exchanges, no equipment to carry, no interruptions to work or daily activities. The machine operates while the patient sleeps, though some patients find the machine sounds (soft beeping, fluid moving) slightly disruptive initially; most adapt quickly. APD patients on a home delivery schedule receive large shipments of supplies (dialysate bags, tubing sets, drain bags) delivered to the home every 2–4 weeks; storage space — typically several large boxes per week of use — is a practical consideration. The freedom and schedule flexibility of home PD are significant advantages for patients who want to maintain work, family activities, and a sense of normalcy. Both CAPD and APD patients are in close contact with their PD nurse (weekly or biweekly phone check-ins, monthly clinic visits) and check their daily weight, blood pressure, and urine output to monitor for fluid balance issues. The NKF’s resources on living with peritoneal dialysis are at the NKF kidney health page.
Diet and Fluid Management as a Dialysis Patient
Dietary restriction is one of the most pervasive day-to-day aspects of life on dialysis, shaping every meal, every restaurant choice, and every social food event. The specific restrictions differ meaningfully between hemodialysis and peritoneal dialysis — PD patients typically have less stringent limits — but both require ongoing attention to food choices that goes well beyond what most people experience with any other chronic condition. Hemodialysis dietary restrictions are the most demanding: because HD is performed only three times per week and waste products accumulate between sessions, strict limits on potassium, phosphorus, sodium, and fluid are essential to prevent life-threatening electrolyte abnormalities. Potassium must typically be limited to approximately 2,000 mg/day — eliminating or strictly limiting bananas, oranges, tomatoes, potatoes, avocados, dairy, nuts, beans, chocolate, and many other potassium-rich foods. Phosphorus must be limited to 800–1,000 mg/day alongside phosphate binder medications taken with every meal and snack; high-phosphorus foods include dairy products, processed meats, dark colas, nuts, seeds, whole grains, and beans, as well as virtually all processed foods (which contain phosphate additives absorbed at up to 100% efficiency, much higher than naturally occurring phosphorus). Sodium must be limited to under 2,000 mg/day primarily to control thirst and fluid intake. Fluid intake — from all beverages and food sources combined — is typically restricted to 1,000–1,500 mL/day to prevent dangerous fluid overload between sessions. For many HD patients, the dietary restrictions are among the most difficult aspects of dialysis life: social eating becomes complicated, favorite foods must be avoided, and every meal requires label-reading and planning. Working with a renal dietitian — ideally on an ongoing basis — is essential to developing practical strategies for managing restrictions while maintaining enjoyable and nutritionally adequate eating. Peritoneal dialysis dietary restrictions are generally less stringent: because PD provides continuous clearance, potassium, sodium, and fluid restrictions are usually much less strict or not required at all for patients with adequate residual kidney function. Phosphorus restriction and binders remain important. PD patients must consume adequate protein (1.2–1.3 g/kg/day) to compensate for protein losses into the dialysate, and must account for absorbed calories from glucose in the dialysate when managing weight. The practical experience of managing PD diet is more similar to a normal diet with some specific modifications, rather than the comprehensive restriction required in HD. Regardless of modality, dialysis patients benefit from tracking their daily weight, monitoring symptoms of fluid overload (swelling, shortness of breath, rapid weight gain), and communicating dietary questions to their renal dietitian — who remains a key ongoing member of the dialysis care team throughout treatment. The StatPearls resource on dialysis nutrition is at the StatPearls dialysis reference.
Working, Traveling, and Staying Active While on Dialysis
Maintaining employment, travel, and physical activity on dialysis is possible — and more common than many newly diagnosed patients realize — but requires planning and adaptation that varies significantly by treatment modality. Employment on dialysis: many dialysis patients continue to work, including full-time, though employment rates among dialysis patients are substantially lower than in the general population (approximately 30–50% depending on age, comorbidities, and modality), reflecting both the real physical burden of dialysis and access barriers. In-center HD patients who work typically work around the three fixed treatment days — early morning HD shifts allow work in the afternoon, evening HD shifts allow morning and afternoon work, and some patients work on non-HD days exclusively. The post-dialysis fatigue that affects many in-center HD patients can make working the same day as dialysis difficult; many patients describe the day after their last HD session (before the next treatment) as their best work day. Home PD patients — particularly those on APD — have the greatest employment flexibility, as treatment occurs overnight and does not restrict daytime hours; many APD patients work full-time without disclosing their dialysis status to employers. Home HD patients similarly benefit from flexible scheduling. Patients should discuss work capacity, occupational limitations (heavy lifting can stress AVF; construction or dirty work environments increase PD infection risk), and disability or insurance considerations with their social worker and healthcare team. Travel on dialysis: travel is possible but requires advance planning. In-center HD patients who travel domestically or internationally arrange “guest” dialysis sessions at dialysis centers near their destination — most centers (both in the US and internationally) accommodate traveling patients with a doctor’s referral and medical records; the dialysis travel nurse or social worker at the home center typically assists with arranging guest slots. Planning should begin 4–8 weeks before travel to allow confirmation of bookings. CAPD patients have the greatest travel freedom: dialysate supply can be arranged for delivery directly to the travel destination (cruise ships, hotels, apartments) in advance through the dialysis supply company; CAPD exchanges can be performed in any clean private space during travel. APD patients can travel with their cycler (most fit in a checked bag or a carry-on-compatible case) with pre-arranged supply delivery. Many dialysis patients travel internationally for weeks or months at a time; with adequate planning, travel is fully achievable. Physical activity on dialysis: exercise is strongly encouraged for dialysis patients, as physical activity improves cardiovascular fitness, muscle strength, energy levels, sleep quality, depression, and — in some studies — dialysis adequacy and survival. Most dialysis patients can exercise safely, with adaptations depending on modality: HD patients should avoid high-impact exercise immediately before or after sessions (when blood pressure may be less stable) but can exercise on non-HD days and during dialysis sessions (intradialytic exercise programs, in which patients use a stationary bike or perform resistance bands during treatment, are offered at some centers); PD patients should avoid high-intraabdominal-pressure activities (heavy straining, powerlifting, contact sports) that risk hernia formation, but can swim (with catheter exit site covered), cycle, walk, and engage in most aerobic activities. The KDIGO guidelines on exercise in CKD and dialysis are at the KDIGO CKD management guidelines.
Emotional and Psychological Life on Dialysis
The psychological dimensions of long-term dialysis are frequently underemphasized in clinical discussions but are as important to quality of life as the physical aspects. Depression and anxiety are substantially more common in dialysis patients than in the general population — affecting approximately 20–40% of dialysis patients depending on the study and diagnostic criteria used — and are associated with worse outcomes including higher hospitalization rates, lower dialysis adherence, and higher mortality. The reasons are multiple: the grief of losing kidney function and the prospect of lifetime dialysis; the loss of independence and the physical constraints of treatment; fatigue and reduced energy for activities that previously brought satisfaction; the multiple dietary and fluid restrictions that reduce one of life’s major social pleasures; changes in body image (fistula, catheter, fluid retention); financial stress (dialysis is expensive and may limit employment); and the ongoing uncertainty of long-term prognosis. Yet many dialysis patients adapt remarkably well over time, finding meaning and connection within the new reality of their health — particularly those with strong social support, access to psychological care, and a sense of agency and control over their treatment choices (which is one reason home therapy, which empowers patients, tends to be associated with better psychological outcomes). Common psychological challenges: grief and loss, particularly in the first months of dialysis; identity changes and adjusting to the “patient” role; relationship strain as dialysis affects partners, family, and social connections; sexual dysfunction (extremely common in dialysis patients, affecting both men and women, due to hormonal changes, fatigue, and medications, and rarely adequately addressed in clinical care); fear about the future (transplant prospects, complications, death); and existential questioning about the quality vs quantity of life being pursued. Accessing psychological support: most comprehensive dialysis centers have a social worker as a core team member, and patients should not hesitate to raise emotional or psychological concerns with any member of the dialysis care team. Formal psychological counseling or psychiatry referral should be offered when depression or anxiety is clinically significant; antidepressant medications can be used safely in most dialysis patients (with appropriate dose adjustments for renal clearance). Peer support programs — in which current dialysis patients with positive adaptation experiences mentor newly starting patients — are available through the National Kidney Foundation and many dialysis centers, and are associated with improved adjustment. The NKF kidney mental health resources are available at the NKF hemodialysis and support page. For patients exploring all treatment options including transplant, the overview is at the dialysis overview guide.
Sources: NIDDK Hemodialysis · KDIGO CKD Guidelines · National Kidney Foundation · StatPearls: Peritoneal Dialysis
Quality of Life on Dialysis: What the Research Shows and What Patients Report
Quality of life (QoL) research in dialysis patients consistently reveals a complex picture: dialysis substantially improves physical symptoms compared to untreated kidney failure, but average QoL scores across dialysis populations remain significantly below those of age-matched general population controls, reflecting the real burden of treatment, comorbid illness, fatigue, dietary restriction, and the psychological weight of chronic illness and limited life expectancy. Yet within dialysis populations, there is enormous variation — many patients report good or excellent quality of life, particularly those who are younger, more physically active, employed, on home dialysis, with strong social support and preserved residual kidney function — while others experience severe quality of life impairment due to multiple comorbidities, post-dialysis fatigue, depression, or inadequate social support. Comparing modalities by quality of life outcomes: home dialysis modalities — both peritoneal dialysis and home hemodialysis — are consistently associated with higher quality of life scores than in-center hemodialysis in observational studies. The most commonly cited reasons are greater schedule flexibility, greater sense of autonomy and control, fewer dietary restrictions (especially for PD), and the practical advantages of treating at home rather than traveling to a center three times per week. Home HD (particularly more frequent or nocturnal home HD) is associated with additional advantages including better sleep quality, better blood pressure control, improved sexual function, less fatigue, and in some studies, better hemoglobin and phosphorus control — all of which contribute to wellbeing. Daily short home HD (5–6 sessions per week) shows the strongest quality of life improvement among HD modalities, though it requires the highest patient commitment. Fatigue and energy: fatigue is the single most commonly reported symptom in dialysis patients, affecting 60–97% depending on how it is measured, and is the symptom patients most frequently identify as most limiting their quality of life. Post-dialysis fatigue in in-center HD — typically several hours of exhaustion following each session — is well-recognized but poorly understood; it appears to be related to rapid solute and fluid shifts, autonomic dysfunction, and possibly cytokine release during the session. Patients on more frequent or longer dialysis (home HD) typically report significantly less fatigue and better energy, likely because the more gradual clearance avoids the dramatic homeostatic swings of conventional three-weekly HD. Sleep quality: sleep disorders are extremely prevalent in dialysis patients — affecting 50–80% — including insomnia, restless legs syndrome, and sleep apnea (both obstructive and central). Sleep quality is consistently better in home PD and home HD patients than in-center HD patients in comparative studies. Many in-center HD patients on the early morning shift report chronic sleep deprivation from early wakeup times, compounded by the general sleep disruption of uremia. The NIDDK provides quality of life resources for kidney patients at the NIDDK kidney failure choices page.
A practical strategy many long-term dialysis patients adopt is deliberately choosing the modality and shift that best protects their highest-priority activities — whether that is daytime work, childcare, travel, or sleep — and then building the remaining schedule around treatment. Patients who approach dialysis as a structural constraint to plan around, rather than a disruption to react to, consistently report better adaptation and higher satisfaction than those who feel the schedule was imposed without their input. For all modalities, active engagement with the dialysis care team — asking questions, reporting symptoms, participating in goal-setting, and exercising choice wherever possible — is strongly associated with better outcomes and better quality of life. The dialysis patient overview covers the full decision framework for choosing between modalities.
I’ve been on in-center HD for six months and the post-dialysis fatigue is the hardest part for me. I feel fine going in but by the time I get home I’m exhausted for several hours. I wasn’t warned about this before starting. The section explaining why post-dialysis fatigue happens — the rapid fluid and solute shifts — helped me understand it’s not just weakness or being out of shape. I’m now considering asking about home HD or at least whether a different session timing might help. I also didn’t realize you could arrange dialysis at centers near travel destinations — that opens up the possibility of actually taking a vacation, which I had assumed was off the table.
The section on employment and home PD resonated with me a lot. I’m on APD and I work full-time — I’ve never disclosed my dialysis to my employer and my workdays are completely unaffected. I connect the cycler before bed, wake up, disconnect, and go about my day normally. The only visible sign at work is that I sometimes take a short break if I need to do a manual exchange, which I very rarely do. I wanted to leave this comment because a lot of newly diagnosed people assume dialysis means they can’t work, which in my experience is not true for APD patients who are otherwise well enough. The flexibility compared to in-center HD is enormous.
Alicia, post-dialysis fatigue is more common and more limiting than it’s often presented to patients before starting, and your instinct to ask about session timing and home HD is worth pursuing. Many patients find that evening sessions (so fatigue occurs during sleeping hours), or a switch to home HD with more frequent shorter sessions, significantly reduces the fatigue burden. James, thank you for sharing your experience — it’s a genuinely useful perspective for people facing this diagnosis. The APD-compatible-with-full-time-work reality is something many nephrologists don’t emphasize enough when presenting treatment choices. The combination of schedule flexibility and overnight treatment makes APD one of the most life-preserving treatment options for working-age patients.