

A urinalysis is one of the most information-dense routine laboratory tests in medicine. From a single urine sample, it can detect signs of kidney disease, urinary tract infection, diabetes, liver disease, and metabolic disorders — often before the patient has noticed any symptoms. Yet many people receive urinalysis results without understanding what the individual components mean or why certain findings matter.
A complete urinalysis consists of three distinct examinations: a physical exam of the urine’s appearance, a chemical (dipstick) exam that tests for up to ten different substances simultaneously, and a microscopic exam that identifies cells, casts, and crystals in the urine sediment. This guide explains each component, what the results reveal, and how to interpret findings in the context of common kidney and urinary conditions.
The Three Parts of a Urinalysis
Every complete urinalysis involves three separate evaluations that provide complementary information.
The physical examination assesses what can be observed directly: the color and clarity of the urine sample, its odor, and its specific gravity (a measure of how concentrated or dilute the urine is). These macroscopic properties provide a quick initial screen and often prompt further investigation.
The chemical (dipstick) examination uses a plastic strip embedded with multiple reagent pads that change color when specific substances are present in the urine. Most dipsticks test for protein, glucose, ketones, blood, pH, specific gravity, nitrite, leukocyte esterase, bilirubin, and urobilinogen — providing ten data points in under two minutes. The dipstick is a sensitive screen, but it is not specific — positive results require confirmation.
The microscopic examination examines a spun-down urine sediment under a microscope to identify red blood cells, white blood cells, epithelial cells, casts (cylindrical structures formed in the kidney tubules), crystals, bacteria, and yeast. This step is the most diagnostically specific part of the urinalysis and is typically performed when the dipstick shows an abnormality, or when kidney disease is clinically suspected.
What Urine Color and Appearance Tell You
Normal urine ranges from pale yellow to amber, depending on hydration status. The yellow color comes from urochrome, a pigment produced by the breakdown of hemoglobin. Well-hydrated individuals produce pale, dilute urine; those who are dehydrated produce deeper amber urine.
Colorless urine indicates very dilute urine — either from excessive fluid intake, or from conditions that impair the kidney’s ability to concentrate urine, such as diabetes insipidus or renal tubular disorders.
Dark amber, brown, or tea-colored urine can indicate severe dehydration, liver disease (where bilirubin spills into the urine), or myoglobinuria from rhabdomyolysis — the breakdown of muscle tissue that releases myoglobin into the bloodstream and then the urine. Rhabdomyolysis can cause acute kidney injury and is a medical emergency.
Red or pink urine most commonly suggests hematuria (blood in the urine), but it can also result from hemoglobinuria (hemolysis releasing free hemoglobin), myoglobinuria, or harmless causes such as eating beets or taking medications such as rifampin or phenazopyridine.
Cloudy or turbid urine suggests suspended material: white blood cells (pyuria from infection), bacteria, phosphate crystals, or heavy protein. Foamy urine — particularly foam that persists after voiding — suggests significant proteinuria, because protein lowers the surface tension of urine and causes it to foam like a detergent.
Specific Gravity — What It Measures
Specific gravity measures the density of urine relative to water, reflecting the total concentration of dissolved solutes. It is a proxy for the kidney’s ability to concentrate and dilute urine in response to the body’s hydration needs.
The normal range is 1.001 to 1.030. High specific gravity (above 1.020) indicates concentrated urine — the kidneys are retaining water, either appropriately in response to dehydration, or abnormally in conditions such as SIADH.
Low specific gravity (below 1.005) indicates very dilute urine — appropriate after drinking large amounts of fluid, or indicating an inability to concentrate urine as seen in diabetes insipidus or renal tubular dysfunction.
Fixed specific gravity at 1.010 — a condition called isosthenuria — means the kidneys can neither concentrate nor dilute urine, producing urine with the same tonicity as blood plasma. Isosthenuria is a marker of severely impaired tubular function and is seen in advanced CKD and acute tubular necrosis (ATN).
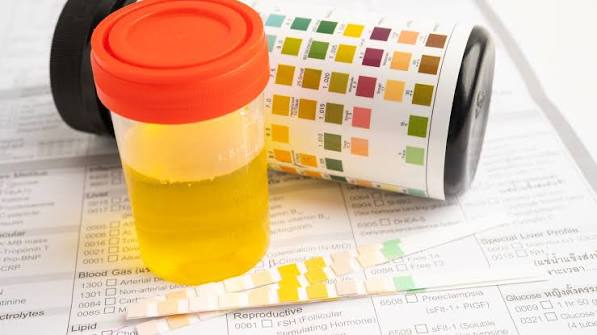
The Dipstick — Reading the Chemical Results
Protein is normally absent or present only in trace amounts. A positive dipstick for protein corresponds to approximately 300 mg of albumin per gram of creatinine — placing it in the A3 (severely increased) range. The dipstick completely misses the A1 and A2 ranges, which is why a urine albumin-to-creatinine ratio (ACR) is required for CKD screening in high-risk patients. A negative dipstick protein does not rule out clinically significant kidney damage. See the urine albumin test guide for full context.
Glucose is normally absent. Glucosuria suggests blood glucose has exceeded the renal threshold of approximately 180 mg/dL — as in poorly controlled diabetes — or that the tubular reabsorption threshold is abnormally low (pregnancy, Fanconi syndrome). SGLT-2 inhibitors intentionally cause glucosuria as their mechanism of action; a positive glucose in a patient taking these drugs is expected.
Ketones appear when the body metabolizes fat for energy: diabetic ketoacidosis (DKA), prolonged fasting, extreme low-carbohydrate dieting, or persistent vomiting. Positive ketones in a known diabetic should prompt checking blood glucose and pH.
Blood (heme) on the dipstick detects heme-containing compounds — intact red blood cells, free hemoglobin (from hemolysis), and myoglobin (from muscle breakdown). A positive dipstick blood must always be followed by microscopic examination to determine whether intact RBCs are present. If RBCs are seen, the finding is true hematuria; if no RBCs are found, the hemoglobin or myoglobin is dissolved from hemolysis or rhabdomyolysis. See the companion article on blood in urine test results for more detail.
Nitrite indicates gram-negative bacteria converting urinary nitrate to nitrite. A positive nitrite strongly suggests a bacterial UTI — but sensitivity is only 50 to 60 percent, because gram-positive organisms do not produce nitrite, and the bacteria require several hours of bladder dwell time to convert nitrate.
Leukocyte esterase (LE) is an enzyme released by white blood cells. A positive result indicates pyuria — WBCs in the urine — which signals infection or urinary tract inflammation. The LE test has a sensitivity of 75 to 96 percent for UTI and is more reliable than nitrite alone. False positives can occur from vaginal contamination or interstitial nephritis.
Bilirubin is normally absent from urine. Conjugated bilirubin in urine indicates liver disease or biliary obstruction. Urobilinogen elevation suggests increased bilirubin production (hemolysis) or decreased hepatic clearance.
Microscopic Exam — Casts, Cells, and Crystals
Red blood cells: Fewer than 3 RBCs per high-power field (hpf) is normal. More than 3 RBCs/hpf constitutes microscopic hematuria. The shape matters: dysmorphic RBCs (acanthocytes with irregular spiky projections) indicate glomerular origin — a finding specific to glomerulonephritis. Uniformly shaped RBCs suggest a non-glomerular source such as kidney stones, UTI, or bladder tumor.
White blood cells: Fewer than 5 WBCs/hpf is normal. More than 5 WBCs/hpf is pyuria, indicating inflammation in the urinary tract. Sterile pyuria — WBCs without detectable bacteria on culture — should raise the consideration of urinary tuberculosis, interstitial nephritis, chlamydia, or gonorrhea (which do not grow on standard urine cultures).
Casts are cylindrical structures formed when proteins or cells become embedded in a Tamm-Horsfall protein matrix within the renal tubule:
- Hyaline casts — pure protein; normal in small numbers in concentrated urine or after exercise.
- RBC casts — pathognomonic for glomerulonephritis; virtually diagnostic regardless of other findings.
- WBC casts — pyelonephritis or interstitial nephritis.
- Muddy brown granular casts — hallmark of acute tubular necrosis (ATN).
- Waxy and broad casts — advanced CKD with severely impaired urine flow.
- Fatty casts and oval fat bodies — lipiduria; marker of nephrotic syndrome.
Crystals reflect urine chemistry and may identify stone type or toxic exposure:
- Calcium oxalate (envelope or dumbbell shape) — most common; associated with stones or ethylene glycol poisoning.
- Uric acid (rhomboid, yellow-brown, in acidic urine) — gout, tumor lysis syndrome.
- Struvite (coffin-lid shape) — urea-splitting bacteria; staghorn stones.
- Cystine (flat hexagonal plates) — pathognomonic for cystinuria, a genetic condition causing recurrent cystine stones.
What the Results Don’t Tell You — Limitations
The dipstick protein test detects only heavy albumin leakage (A3 range, greater than 300 mg/g) and misses the A1 and A2 ranges where early kidney disease and the highest-impact intervention opportunity exist. A patient with an ACR of 100 mg/g — firmly in the A2 range, indicating established early diabetic nephropathy — will have a completely negative dipstick protein. Relying on the dipstick alone to screen for CKD in diabetic or hypertensive patients is inadequate; ACR testing is required. See the article on protein in urine for a complete discussion of proteinuria and its causes.
Contamination from vaginal secretions, perineal skin flora, or improper collection technique is one of the most common sources of urinalysis error. False-positive WBCs, bacteria, and epithelial cells are common from contaminated samples. The presence of many squamous epithelial cells on microscopy signals contamination, and a repeat midstream clean-catch sample should be requested before treating a presumed UTI based on a contaminated result.
No single urinalysis finding is diagnostic in isolation. RBC casts strongly suggest glomerulonephritis but require correlation with clinical history, blood tests (see the kidney function tests guide), and often kidney biopsy for definitive diagnosis. Pyuria with negative culture requires a broad differential including TB and interstitial nephritis. Every abnormal urinalysis finding is the beginning of a diagnostic workup, not the end.
When a Urinalysis Is Ordered
A urinalysis is appropriate in a broad range of clinical contexts: routine annual health screening (where it can detect early protein loss or microscopic hematuria before symptoms develop); suspected urinary tract infection (dysuria, urgency, frequency, flank pain, fever); suspected kidney disease (edema, hypertension, foamy urine, declining eGFR); pregnancy (preeclampsia and asymptomatic bacteriuria screening); preoperative evaluation; and the workup of acute kidney injury, where the cast pattern helps distinguish ATN, glomerulonephritis, interstitial nephritis, and prerenal causes.
How to Prepare for a Urinalysis
A first morning void provides the most concentrated urine sample and is optimal for detecting protein and casts. A midstream clean-catch specimen — where the first stream of urine is discarded before collecting the sample — reduces contamination from periurethral bacteria and skin cells. Vigorous exercise should be avoided within 24 hours, as exercise can transiently cause hematuria and proteinuria. If testing during menstruation is unavoidable, the clinician should be informed, as menstrual blood can contaminate the sample. No fasting is required.
Conclusion
A urinalysis is far more than a simple urine test. When all three components are examined and interpreted together, it provides a window into the health of the kidneys, the urinary tract, the liver, and the metabolic state of the body. Understanding what each finding means — and what it does not mean — allows patients to engage more meaningfully with their care and ensures that abnormal results are followed up appropriately.
For conditions identified on urinalysis, see the companion articles on protein in urine, blood in urine, kidney function tests, and what is chronic kidney disease.
Interpreting Urinalysis Results in Clinical Context
A urinalysis result sheet lists each parameter individually, but the real diagnostic work comes from reading the findings as a pattern rather than as isolated data points. Several combinations of findings are particularly informative and frequently encountered in clinical practice.
The UTI pattern is the most common urinalysis constellation: positive leukocyte esterase, positive nitrite, WBCs on microscopy (greater than 5/hpf), and bacteria visible on the spun sediment. This combination in a patient with dysuria, urgency, and frequency has a high positive predictive value for bacterial UTI and is sufficient to start empiric antibiotic therapy pending urine culture results. The culture is still important because it identifies the specific organism and its antibiotic sensitivities, which guides definitive treatment and identifies resistant organisms.
The glomerulonephritis pattern is one of the most important urinalysis findings in nephrology: proteinuria (positive dipstick) combined with hematuria (positive dipstick blood) and RBC casts on microscopy. This triad indicates active glomerular inflammation — the glomeruli are leaking both protein and red blood cells, and the RBC casts confirm that the bleeding originates from the kidney itself rather than the bladder or urethra. In this context, the clinician must proceed urgently to further evaluation: blood tests for creatinine, eGFR, complement levels, ANCA, anti-GBM antibodies, and ANA, along with nephrology referral and likely kidney biopsy for definitive diagnosis.
The nephrotic syndrome pattern combines heavy proteinuria (3+ or 4+ on dipstick, or ACR greater than 3,500 mg/g), lipiduria (oval fat bodies, fatty casts, Maltese crosses under polarized light), and typically minimal or no hematuria — the glomeruli are leaking large amounts of protein but the filtration barrier is not hemorrhaging. This contrasts with the nephritic pattern of the glomerulonephritis pattern above, where hematuria and RBC casts predominate. The distinction between nephrotic and nephritic urinalysis patterns guides the differential diagnosis and subsequent workup.
The ATN pattern is characterized by the muddy brown granular casts in the setting of acute kidney injury (rising creatinine). This pattern indicates that the renal tubular cells themselves are dying or severely injured — the muddy brown color comes from the hemosiderin pigment and cellular debris incorporated into the cast matrix. ATN is the most common cause of hospital-acquired acute kidney injury, and its urinalysis pattern helps distinguish it from prerenal azotemia (where the urinalysis is typically bland, with only concentrated urine and hyaline casts) and from glomerulonephritis (where RBC casts predominate).
The interstitial nephritis pattern classically shows WBCs, WBC casts, and eosinophils in the urine (though urine eosinophils have limited sensitivity and specificity in practice). Interstitial nephritis is most commonly drug-induced — associated with NSAIDs, penicillins, cephalosporins, proton pump inhibitors, and many other medications — and presents with acute kidney injury, often accompanied by fever, rash, and peripheral blood eosinophilia. Recognizing the pattern and identifying the offending drug is the key to treatment, as removing the causative agent often leads to recovery.
Urinalysis in Chronic Kidney Disease Monitoring
For patients with established chronic kidney disease, the urinalysis serves not just as a diagnostic tool but as a regular monitoring instrument. Changes in the urinalysis pattern over time can signal disease activity, progression, or the development of complications.
In diabetic kidney disease, the urinalysis may show worsening proteinuria as the ACR rises through the A2 and into the A3 range over years. The absence of hematuria in the early stages of diabetic nephropathy is typical — and its appearance should prompt evaluation for a superimposed cause such as a UTI, kidney stone, or bladder pathology, rather than being attributed to the diabetes itself.
In patients with IgA nephropathy — the most common form of glomerulonephritis worldwide — the urinalysis typically shows microscopic hematuria as a persistent finding, often with intermittent episodes of gross hematuria triggered by upper respiratory infections (a phenomenon called synpharyngitic hematuria, where the urine turns pink or red 1 to 2 days after the onset of a sore throat). Persistent microscopic hematuria with proteinuria in this population warrants nephrology evaluation and often kidney biopsy, even when creatinine and eGFR are still normal.
In lupus nephritis, urinalysis monitoring is used to track disease activity. Active lupus nephritis produces hematuria, proteinuria, and often RBC and WBC casts — a pattern that parallels histological activity on kidney biopsy. As immunosuppressive treatment achieves remission, the urinalysis improves: casts disappear, hematuria diminishes, and proteinuria decreases. A flare of lupus nephritis is often heralded by a return of active urinary sediment before creatinine has changed, making regular urinalysis an important early warning tool in lupus monitoring.
For patients being monitored after an episode of acute kidney injury, the urinalysis at the follow-up visit provides important information about recovery. Persistent granular casts suggest ongoing tubular stress; clearing of casts with improving creatinine suggests recovery of tubular function. New-onset proteinuria or hematuria at a follow-up visit after AKI raises the question of whether the AKI has unmasked or precipitated underlying glomerular disease that requires separate evaluation.
Special Considerations: Urine Collection and Timing
The interpretation of urinalysis results depends substantially on the conditions under which the sample was collected. Clinicians ordering a urinalysis should specify the collection method and timing, and patients should understand why these details matter.
A catheterized specimen avoids contamination entirely and is the gold standard for urine culture in patients who cannot provide a reliable clean-catch specimen — including patients who are confused, have urinary incontinence, or have anatomical barriers to clean voiding. The urinalysis from a catheterized specimen is more reliable for WBC and bacteria interpretation, though catheter insertion itself can introduce a small amount of blood and epithelial cells.
A suprapubic aspirate — obtained by inserting a needle directly through the abdominal wall into the bladder — is the most sterile urine specimen possible and is used in infants and in adults when absolute sterility is required for culture. Any growth from a suprapubic aspirate culture is considered significant, because the specimen bypasses all external contamination sources.
Urinalysis results can change rapidly in acutely ill patients. A patient presenting with flank pain and a normal urinalysis may develop hematuria over hours as a kidney stone moves. A patient with early pyelonephritis may have a relatively bland urinalysis at first presentation that shows increasing WBCs and WBC casts as the infection ascends into the renal parenchyma. When clinical suspicion is high and the urinalysis is inconclusive, repeating the test within 24 hours or sending the specimen for culture regardless of the dipstick result is appropriate.
When to Follow Up After an Abnormal Urinalysis
An abnormal urinalysis result is a starting point, not a final diagnosis. The appropriate follow-up depends on which findings are abnormal, their degree of abnormality, and the clinical context in which the test was performed.
Microscopic hematuria (more than 3 RBCs/hpf on two of three properly collected specimens) in an adult without an obvious benign explanation — such as vigorous exercise, menstruation, or an active UTI — warrants structured evaluation. In adults over 35 or in any adult with risk factors for urinary tract malignancy (smoking history, occupational chemical exposure, prior pelvic radiation, irritative voiding symptoms), the American Urological Association recommends cystoscopy and imaging of the upper urinary tract to exclude bladder and kidney cancer. In younger adults without risk factors, a nephrology evaluation to assess for glomerular causes (IgA nephropathy, thin basement membrane disease) is often appropriate, particularly when proteinuria accompanies the hematuria.
Proteinuria on dipstick (1+ or greater) should be quantified with a urine ACR rather than followed up with a repeat dipstick. If the ACR confirms A2 or A3 albuminuria on two of three tests, a full kidney evaluation including creatinine, eGFR, blood pressure measurement, and assessment for diabetes and hypertension is warranted. Proteinuria combined with hematuria — particularly in the setting of hypertension, edema, or elevated creatinine — raises the priority level significantly and should prompt nephrology referral without delay.
Glucosuria in a patient not known to have diabetes or to be taking SGLT-2 inhibitors warrants a fasting blood glucose and hemoglobin A1c measurement to screen for undiagnosed diabetes or impaired glucose tolerance. Isolated glucosuria with normal blood glucose suggests a low renal glucose threshold (renal glucosuria, a benign genetic condition in most cases) or Fanconi syndrome if accompanied by other findings such as phosphaturia, aminoaciduria, or bicarbonaturia.
Positive leukocyte esterase without urinary symptoms (asymptomatic pyuria) is a common finding, particularly in older women, where it often reflects perineal contamination, urethral inflammation, or the normal aging changes in the genitourinary epithelium. Treating asymptomatic pyuria in non-pregnant adults without additional findings is generally not indicated and may select for antibiotic-resistant organisms. Exceptions include pregnant women (where asymptomatic bacteriuria carries a risk of pyelonephritis and preterm birth and should always be treated) and patients who will undergo urologic instrumentation.
Ketonuria in a diabetic patient should be taken seriously regardless of the dipstick blood glucose, as ketones can be present even with near-normal blood glucose in certain forms of DKA. A blood ketone level and arterial or venous blood gas are more definitive than urine ketones for diagnosing DKA, since urine ketone tests measure acetoacetate (not beta-hydroxybutyrate, the predominant ketone in DKA), and may lag behind blood ketone levels during both the development and resolution of DKA.
Regardless of which finding is abnormal, the overarching principle is that the urinalysis result should be integrated with the full clinical picture before any action is taken. The test is a screening instrument, and its value is maximized when it is used to direct the next, more specific diagnostic step — rather than being over-interpreted or under-appreciated in isolation.
Sources: NIDDK — CKD Tests & Diagnosis | Mayo Clinic — Urinalysis | MedlinePlus — Urinalysis
This breakdown of urinalysis: what it can show is exactly what patients need before a specialist appointment. The practical tips made this immediately actionable, not just theoretical. Appreciate the effort that went into researching and writing this — it shows.
I shared this article on urinalysis: what it can show with my doctor and they appreciated the level of detail. The article answered questions I didn’t even know I had until I started reading. Will definitely be coming back to this site for more health information.
Really well-written article on urinalysis: what it can show. The connection between lifestyle choices and long-term outcomes is explained clearly here. Forwarding this to others in my support group who are dealing with similar issues.