
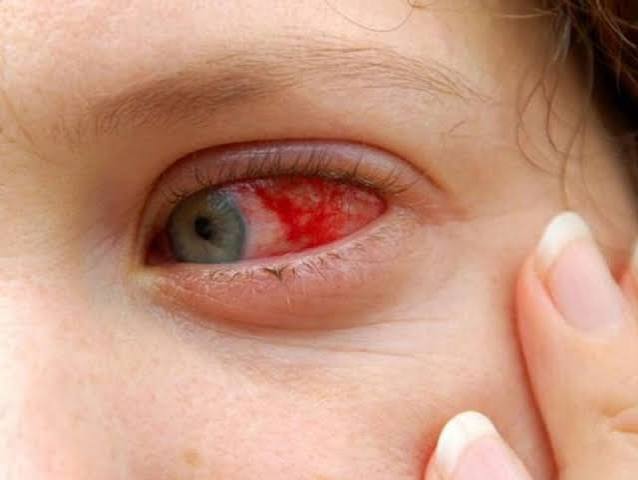
Diabetic retinopathy is simultaneously one of the most preventable and one of the most feared complications of diabetes — preventable because it develops slowly over years and responds dramatically to treatment when detected early, feared because late-stage diabetic retinopathy causes sudden, devastating vision loss that is often irreversible by the time the person notices any problem. The condition affects the retina — the light-sensitive tissue lining the back of the eye — through the progressive destruction of its intricate microvasculature, driven by chronically elevated blood glucose and compounded by hypertension, dyslipidemia, and the duration of diabetes. According to the CDC, diabetic retinopathy is the leading cause of new cases of legal blindness among working-age adults in the United States — yet large population studies consistently demonstrate that up to 98% of severe vision loss from diabetes could be prevented by timely treatment combined with good metabolic and blood pressure control. The challenge is that the disease is essentially silent until it is advanced: the person sees normally while significant, potentially irreversible damage is building in their retina, which is why the annual dilated eye examination — the single most effective intervention in this entire field — is so non-negotiably important for every adult with diabetes.
Approximately 34% of adults with diabetes in the United States have some degree of diabetic retinopathy — representing over 7 million Americans. Of these, approximately 1 in 12 adults with diabetic retinopathy has vision-threatening disease (proliferative retinopathy or clinically significant macular edema). The risk of retinopathy increases dramatically with duration of diabetes: after 20 years of Type 1 diabetes, nearly all patients have some degree of retinopathy. After 20 years of Type 2 diabetes, over 60% have retinopathy. Each 1% reduction in A1C is associated with a 35–40% reduction in retinopathy progression in Type 1 diabetes (DCCT) and a 37% reduction in microvascular complications (including retinopathy) in Type 2 diabetes (UKPDS).
How Diabetic Retinopathy Develops: The Pathophysiology
The retina is the most metabolically active tissue per unit volume in the entire human body — its extraordinary oxygen and glucose demands are served by a highly specialized microvasculature that is exquisitely sensitive to the vascular damage driven by hyperglycemia. The cascade of events leading from initial hyperglycemia to vision-threatening retinopathy unfolds through a sequence of cellular and structural changes that represent the convergence of all four major hyperglycemia-driven damage mechanisms:
- Pericyte loss — the earliest structural change: Pericytes are specialized contractile cells that wrap around retinal capillaries, regulating blood flow and maintaining capillary structural integrity. They are uniquely vulnerable to hyperglycemia because they absorb glucose independently of insulin, exposing them to the full effect of polyol pathway activation and sorbitol accumulation. Pericyte loss — detectable in retinal histological specimens — is the first structural change in diabetic retinopathy, preceding microaneurysm formation and any clinically visible retinal findings. As pericytes disappear, the capillary wall loses its structural support, the basement membrane thickens and weakens, and the remaining endothelial cells proliferate aberrantly to form the characteristic saccular outpouchings called microaneurysms.
- Blood-retinal barrier breakdown and vascular leakage: The blood-retinal barrier — maintained by the tight junctions between retinal endothelial cells — normally prevents plasma proteins and fluid from leaking into the retinal tissue. In diabetic retinopathy, protein kinase C (PKC) activation by hyperglycemia increases VEGF production, which directly phosphorylates occludin and other tight junction proteins, disrupting their sealing function. The result is increased vascular permeability — plasma proteins, lipids, and fluid leak from damaged capillaries into the surrounding retinal tissue. Lipid deposits (hard exudates) mark where plasma protein-rich fluid has leaked and concentrated; fluid accumulation in the macula (diabetic macular edema, DME) causes the direct central vision impairment that is the most common cause of vision loss in early and moderate diabetic retinopathy. DME can occur at any stage of retinopathy and does not require proliferative disease.
- Capillary occlusion and retinal ischemia: Progressive thickening of the capillary basement membrane, increased platelet aggregability (part of the prothrombotic state in diabetes), and reduced red blood cell deformability impair blood flow through retinal capillaries, causing progressive microvascular occlusion. As capillaries close, the retinal tissue they supplied becomes ischemic — appearing on ophthalmoscopy as cotton-wool spots (fluffy white patches representing infarction of the nerve fiber layer). Extensive capillary nonperfusion creates large areas of retinal ischemia that drive the next and most dangerous phase of the disease. Our diabetes complications: what adults should know guide covers the full spectrum of mechanisms driving all diabetes complications.
- VEGF-driven neovascularization — the transition to proliferative disease: The ischemic retina’s response to oxygen deprivation is to release VEGF (vascular endothelial growth factor) — a powerful angiogenic signal that stimulates the growth of new blood vessels to restore blood supply. Unfortunately, the new vessels that grow in proliferative diabetic retinopathy are pathological: they grow in disorganized networks from the disc and major arcades into the vitreous cavity, lack the pericyte coverage and tight junctions of normal retinal vessels, and are extremely fragile. These new vessels bleed easily — causing vitreous hemorrhage — and the fibrovascular tissue surrounding them contracts over time, causing tractional retinal detachment (physically pulling the retina away from the pigment epithelium). Both vitreous hemorrhage and tractional retinal detachment cause sudden, potentially permanent, severe vision loss. The A1C monitoring that directly affects retinopathy risk is covered in our A1C testing schedule guide.
The Stages of Diabetic Retinopathy: From Mild to Vision-Threatening
Diabetic retinopathy is classified into four stages by the Early Treatment Diabetic Retinopathy Study (ETDRS) grading system, which has been the international standard since the landmark clinical trials of the 1980s. Each stage represents increasing severity of retinal vascular damage and carries a different risk of vision-threatening progression:
- Mild non-proliferative diabetic retinopathy (NPDR): Mild NPDR is the earliest clinically detectable stage, defined by the presence of at least one microaneurysm visible on dilated fundus examination or retinal photography. At this stage, visual acuity is typically completely normal — the person sees normally despite the presence of pathological retinal changes. The 5-year risk of progressing to high-risk proliferative retinopathy from mild NPDR is approximately 5%, which is low but not negligible — and it increases dramatically if glucose and blood pressure are poorly controlled. The recommended examination interval for mild NPDR is annually (every 12 months), with intensive focus on improving all modifiable risk factors: A1C, blood pressure below 130/80 mmHg, and lipid control.
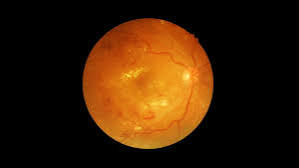
- Moderate non-proliferative diabetic retinopathy (NPDR): Moderate NPDR is characterized by more extensive retinal findings: multiple microaneurysms, dot-and-blot hemorrhages (small intraretinal bleeds from damaged capillaries), venous beading (irregular dilation and constriction of retinal veins, indicating ischemia), and cotton-wool spots (nerve fiber layer infarcts from capillary occlusion). Visual acuity may still be normal in the absence of macular edema, but the 5-year progression risk to high-risk proliferative retinopathy increases to approximately 12–27%. The examination interval typically shortens to every 6 months for moderate NPDR. Diabetic macular edema — the most common cause of vision impairment at this stage — requires prompt assessment with optical coherence tomography (OCT) to determine whether central-subfield macular thickness is elevated enough to warrant anti-VEGF treatment.
- Severe non-proliferative diabetic retinopathy (NPDR) — the “4-2-1” rule: Severe NPDR is defined by the presence of ANY of the following (the “4-2-1” rule): hemorrhages and microaneurysms in all 4 retinal quadrants, venous beading in 2 or more quadrants, or intraretinal microvascular abnormalities (IRMAs — shunts between arterioles and venules that bypass occluded capillary beds) in 1 or more quadrants. The 1-year risk of progressing to high-risk proliferative retinopathy from severe NPDR is approximately 15%, and the 5-year risk exceeds 50% without intervention. Examination intervals shorten to every 3–4 months. Many ophthalmologists discuss initiating panretinal laser photocoagulation or intravitreal anti-VEGF therapy at this stage to prevent the development of the high-risk proliferative stage.
- Proliferative diabetic retinopathy (PDR) — the vision-threatening stage: PDR is defined by the presence of neovascularization — abnormal new blood vessel growth visible on dilated fundus examination or retinal fluorescein angiography. High-risk PDR — defined by neovascularization at or within 1 disc diameter of the optic disc (NVD) larger than one-quarter disc area, or any NVD with vitreous hemorrhage, or neovascularization elsewhere (NVE) larger than one-half disc area with vitreous hemorrhage — carries a 5-year risk of severe vision loss exceeding 50% without treatment. PDR requires urgent treatment. Both panretinal laser photocoagulation (PRP) — which destroys peripheral ischemic retina to reduce VEGF production — and intravitreal anti-VEGF therapy (ranibizumab, bevacizumab, aflibercept) have demonstrated efficacy in reducing high-risk PDR progression and vitreous hemorrhage. The DRCR Protocol S trial demonstrated non-inferiority of ranibizumab to PRP for PDR, with better preservation of visual field and lower rates of DME development — but PRP remains appropriate in settings where anti-VEGF follow-up compliance cannot be assured. Our diabetes and eye health guide covers the full range of diabetic ocular complications. The complete diabetes monitoring schedule is in our annual diabetes care checklist.
Diabetic Macular Edema: The Most Common Cause of Vision Loss
Diabetic macular edema (DME) — swelling of the central retina caused by leakage from damaged retinal capillaries — is the most common cause of vision impairment from diabetic retinopathy and can occur at any stage of retinopathy, including mild NPDR. Because DME affects the macula — the central 5 degrees of the visual field responsible for reading, face recognition, and fine detail — its visual impact is immediate and profound even when peripheral retinal changes are limited:
- Center-involving DME — the threshold for anti-VEGF treatment: Center-involving DME (CI-DME) — in which fluid accumulation on optical coherence tomography (OCT) involves the central subfield of the macula (within 500 microns of the foveal center) — is the threshold that triggers immediate anti-VEGF treatment in most clinical guidelines. The DRCR Protocol T trial directly compared three anti-VEGF agents (aflibercept, bevacizumab, ranibizumab) for CI-DME and found that all three produced significant visual acuity gains over 2 years, with aflibercept showing superior outcomes in eyes with baseline visual acuity worse than 20/50. The standard treatment course is monthly injections for 5–6 months, followed by extension to longer injection intervals as the edema resolves — with treatment continuing until the OCT shows stable resolution without further injections. Adults with CI-DME should expect multiple injections per year during the active treatment phase and regular OCT monitoring to guide retreatment decisions.
- Non-center-involving DME and laser photocoagulation: DME that does not involve the foveal center — detected on OCT and clinical examination — is watched closely and may be treated with focal/grid laser photocoagulation targeting the leaking microaneurysms and capillaries responsible for the edema. Focal laser is less likely to cause visual acuity improvement than anti-VEGF therapy but may provide stable, long-lasting reduction in peripheral macular edema and is particularly appropriate for non-center-involving DME that poses a risk of foveal involvement without treatment. Steroid implants (fluocinolone acetonide, dexamethasone intravitreal implant) provide an alternative for adults with CI-DME who are pseudophakic (have had cataract surgery) and have not responded to multiple anti-VEGF injections, providing extended drug release over months with fewer injection visits.
- Systemic risk factor control as essential adjunctive treatment for DME: Anti-VEGF therapy treats the downstream consequence of hyperglycemia-driven retinal vascular damage, but it does not address the upstream drivers. Adults with CI-DME who achieve substantial A1C reduction during the treatment course have significantly better visual acuity outcomes than those whose glucose remains poorly controlled — because reducing the VEGF-driving stimulus of retinal ischemia makes the retina more responsive to anti-VEGF treatment and prolongs the intervals between injections. Similarly, blood pressure control (particularly the reduction of systemic hypertension, which directly elevates intraretinal hydrostatic pressure and worsens edema) and lipid control (elevated triglycerides are associated with more severe hard exudate deposition and macular lipid accumulation) both contribute to better DME treatment outcomes. Our blood pressure monitoring in diabetes guide and cholesterol monitoring in diabetes guide are directly relevant to DME management and outcomes.
How Diabetic Retinopathy Is Diagnosed
The diagnosis of diabetic retinopathy requires direct visualization of the retina — it cannot be detected from symptoms alone, blood tests, or indirect examination. The ADA recommends comprehensive dilated eye examination at Type 2 diabetes diagnosis (because many adults have had undiagnosed diabetes for years) and annually thereafter for adults with any degree of retinopathy, or every 1–2 years for adults who have had a completely normal retinal examination:
- Dilated fundus examination — the clinical standard: A comprehensive dilated fundus examination, performed by an ophthalmologist or optometrist with pupil dilation using topical mydriatic drops, allows direct visualization of the retinal vasculature, optic nerve, macula, and peripheral retina. The examination detects microaneurysms, intraretinal hemorrhages, hard exudates, cotton-wool spots, venous beading, IRMAs, disc neovascularization, and neovascularization elsewhere — the entire spectrum of diabetic retinopathy findings. The quality of dilated fundus examination by an experienced retinal specialist is the gold standard against which other screening modalities are compared.
- Retinal photography and telemedicine screening: Nonmydriatic retinal photography — which can be performed without pupil dilation using a wide-angle fundus camera — has been validated as an accurate screening tool for diabetic retinopathy and is increasingly deployed in primary care and endocrinology settings to expand access to retinal screening beyond what ophthalmology referral rates would achieve. The ADA endorses telemedicine diabetic retinopathy screening using validated camera systems in settings where access to dilated eye examination is limited. Critically, retinal photography screening detects retinopathy but cannot substitute for a comprehensive dilated examination with OCT when retinopathy is found — because photography alone misses DME in a significant proportion of cases without OCT confirmation.
- Optical coherence tomography (OCT) and OCT angiography: OCT — which creates high-resolution cross-sectional images of retinal layers using near-infrared light — is essential for detecting and quantifying DME, measuring changes in macular thickness in response to treatment, and identifying subclinical fluid accumulation before it causes visual acuity loss. OCT angiography (OCTA) — a newer, dye-free technique that images retinal and choroidal blood flow — detects microaneurysms and capillary nonperfusion with greater sensitivity than clinical examination and is increasingly used for research and for detecting early retinal vascular changes that precede visible retinopathy. OCTA cannot yet substitute for fluorescein angiography in staging PDR or guiding laser treatment, but it is transforming the ability to detect early retinopathy before it is visible on clinical examination. The National Eye Institute’s diabetic retinopathy information, the ADA’s eye complication resources, and the CDC’s diabetic retinopathy overview provide authoritative guidance on screening recommendations, staging, and treatment options.
Preventing Diabetic Retinopathy: Evidence-Based Strategies
The DCCT and UKPDS trials established the evidence base for retinopathy prevention with such clarity that no controversy remains: intensive glucose control and blood pressure control each independently reduce retinopathy incidence and progression by 25–76%, and their effects are additive. The challenge is applying this evidence to daily diabetes management decisions over many years:
- Glycemic control — the primary prevention lever: The DCCT demonstrated that intensive glucose control in Type 1 diabetes reduced the development of retinopathy by 76% and slowed progression by 54% over 6.5 years. The UKPDS demonstrated similar benefits in Type 2 diabetes: each 1% reduction in A1C reduced retinopathy complications by approximately 37%. The legacy effect is particularly important for retinopathy: adults who had intensive glucose control early in DCCT continued to have significantly lower retinopathy rates 10 years after the trial ended, even though the two groups’ A1C levels had converged — demonstrating that early glucose control produces persistent structural protection in the retina. The A1C monitoring schedule and targets for retinopathy prevention are covered in our A1C testing schedule guide.
- Blood pressure control — independent of glucose, equally powerful: The UKPDS demonstrated that tight blood pressure control (systolic below 150 mmHg, using either an ACE inhibitor or beta-blocker) reduced the risk of retinopathy progression by 34% and the need for laser treatment by 35% — effects comparable in magnitude to the glucose control benefit. Current guidelines target blood pressure below 130/80 mmHg in adults with diabetes and established complications. ACE inhibitors and ARBs may provide additional retinal protection beyond their blood pressure effects through direct inhibition of the renin-angiotensin system’s role in VEGF-mediated neovascularization. Our blood pressure monitoring in diabetes guide covers monitoring techniques and treatment targets.
- Lipid control and fenofibrate — a retina-specific benefit: The ACCORD-Eye substudy and the FIELD study both demonstrated that fenofibrate — a fibrate medication used primarily for elevated triglycerides — significantly reduced diabetic retinopathy progression and the need for laser photocoagulation, independent of its lipid-lowering effects. The mechanism is not fully understood but may involve direct anti-inflammatory and anti-angiogenic effects of fenofibrate on the retinal vasculature through PPAR-alpha activation. Fenofibrate is now listed in ADA Standards of Care as a consideration for slowing retinopathy progression in adults with mild to moderate NPDR who are already on statin therapy for lipid control. Our cholesterol monitoring in diabetes guide covers the complete lipid management framework. The comprehensive annual monitoring coordinating retinal examinations with all other diabetes care is in our annual diabetes care checklist.
When to Seek Urgent Eye Care
Adults with diabetes should seek same-day or emergency ophthalmologic evaluation for any of the following: sudden new floaters or flashes of light (which may indicate vitreous hemorrhage or retinal tear), a sudden curtain or shadow across the visual field (which may indicate retinal detachment), sudden significant decrease in visual acuity in one or both eyes, or any new distortion of straight lines (metamorphopsia, which suggests acute macular changes). These symptoms represent vision-threatening emergencies in which hours matter — delayed evaluation can mean the difference between surgical success and permanent vision loss. Adults who experience a vitreous hemorrhage that clears spontaneously should still have an urgent retinal evaluation because the underlying proliferative retinopathy that caused it requires treatment even after the blood clears. Do not wait for a scheduled annual examination if any of these warning signs develop.
Sources: American Diabetes Association — Standards of Medical Care in Diabetes, diabetic retinopathy screening and treatment; National Eye Institute (NEI) — diabetic retinopathy information; CDC — diabetic retinopathy as leading cause of blindness in working-age adults; DCCT — 76% reduction in retinopathy development with intensive glucose control in Type 1 diabetes; UKPDS — 37% reduction in microvascular complications per 1% A1C reduction; blood pressure control reducing retinopathy progression by 34% (UKPDS); legacy effect of early glucose control on long-term retinopathy risk (DCCT/EDIC); ETDRS (Early Treatment Diabetic Retinopathy Study) staging system and laser photocoagulation evidence; diabetic retinopathy prevalence — 34% of adults with diabetes in the United States; proliferative retinopathy 5-year vision loss risk exceeding 50% without treatment; DRCR Protocol T — anti-VEGF comparison (aflibercept, bevacizumab, ranibizumab) for diabetic macular edema; DRCR Protocol S — ranibizumab non-inferiority to panretinal laser for proliferative retinopathy; ACCORD-Eye and FIELD studies — fenofibrate reducing retinopathy progression; OCT angiography for early retinopathy detection; telemedicine retinal photography screening validation; pericyte loss as earliest retinopathy structural change; blood-retinal barrier breakdown and VEGF-mediated vascular permeability; polyol pathway sorbitol accumulation in retinal pericytes.
Thank you for covering diabetic retinopathy so thoroughly without being overly technical. The practical tips made this immediately actionable, not just theoretical. Keep up this kind of thorough health journalism — it genuinely helps patients like me.
Really well-written article on diabetic retinopathy. The connection between lifestyle choices and long-term outcomes is explained clearly here. Appreciate the effort that went into researching and writing this — it shows.
I never fully understood diabetic retinopathy until I read this. This is the kind of evidence-based writing that actually changes how people approach their health. Appreciate the effort that went into researching and writing this — it shows.