
Vomiting blood — medically called hematemesis — is one of the most alarming symptoms a person can experience, and for good reason: it indicates active bleeding somewhere in the upper gastrointestinal tract (esophagus, stomach, or duodenum) and constitutes a medical emergency until proven otherwise. The blood may appear as bright red material, indicating active bleeding, or as dark brown “coffee ground” material, indicating that the blood has been in the stomach long enough to undergo partial digestion by gastric acid. Either presentation demands immediate medical evaluation — the underlying cause ranges from relatively manageable (a Mallory-Weiss tear from forceful vomiting) to life-threatening (ruptured esophageal varices in cirrhosis or a bleeding peptic ulcer).
Upper gastrointestinal bleeding (UGIB) — the broader category that includes hematemesis — accounts for approximately 100,000 hospitalizations annually in the United States and carries an in-hospital mortality of five to fourteen percent depending on the cause and severity. Rapid triage and risk stratification are essential: the Glasgow-Blatchford score and the Rockall score are validated risk tools that help clinicians identify patients who can be safely managed as outpatients versus those requiring urgent endoscopy and hospital admission. Understanding the causes of vomiting blood, recognizing the warning signs that indicate the most dangerous presentations, and knowing what to do when it occurs are essential pieces of health literacy for adults at risk.
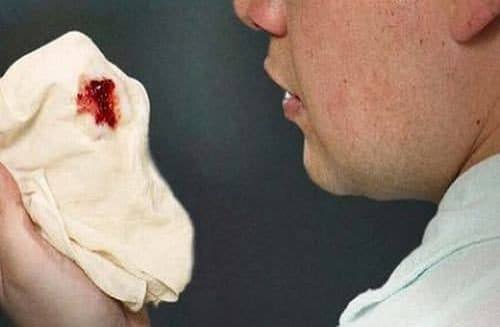
Causes of Vomiting Blood — From Mallory-Weiss Tears to Variceal Hemorrhage
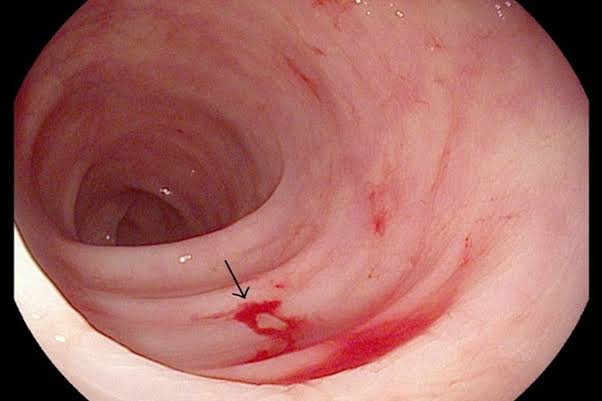
Peptic ulcer disease is the most common cause of upper gastrointestinal bleeding overall, accounting for approximately forty percent of cases. Ulcers in the stomach (gastric ulcers) or duodenum (duodenal ulcers) bleed when the ulcer erodes into a submucosal artery — a process that produces brisk, arterial hemorrhage. The most common underlying causes of peptic ulcers are Helicobacter pylori infection, which undermines the mucosal barrier through urease-mediated ammonia production and inflammatory cell recruitment, and chronic NSAID use, which suppresses prostaglandin synthesis and compromises the protective gastric mucus layer. Ulcers caused by H. pylori can be cured by eradication of the bacterium with antibiotics; NSAID-induced ulcers require stopping the causative drug and treating with proton pump inhibitors (PPIs). When ulcers have eroded a visible vessel, endoscopic hemostasis — injection, thermal coagulation, or mechanical hemoclip placement — is highly effective at controlling bleeding, with rebleeding rates substantially reduced by PPI infusion after endoscopy.
Esophageal varices — dilated venous collaterals in the esophagus caused by portal hypertension in cirrhosis — are responsible for approximately ten to twenty percent of upper GI bleeding cases but account for a disproportionate share of mortality. Variceal hemorrhage is brisk, high-volume, and difficult to control; patients with known cirrhosis who vomit blood should be presumed to have variceal bleeding until endoscopy proves otherwise. As discussed in the article on liver function and coagulopathy, the impaired hemostasis of cirrhosis compounds the variceal bleeding risk. Management combines pharmacological reduction of portal pressure (terlipressin or octreotide), prophylactic antibiotics, and urgent endoscopic band ligation — with TIPS as rescue therapy for refractory bleeding. Gastric varices are less common than esophageal varices but bleed more massively when they rupture, and their management — often requiring cyanoacrylate glue injection or TIPS — is more complex than esophageal varices.
Mallory-Weiss syndrome — a longitudinal mucosal tear at the gastroesophageal junction caused by the shearing forces of forceful or repeated vomiting — produces hematemesis that is typically less severe than ulcer or variceal bleeding. It classically follows a bout of retching or vomiting from any cause — alcohol excess, pregnancy-related nausea, gastroenteritis, or violent coughing — and is identified on endoscopy as a linear mucosal laceration. Most Mallory-Weiss tears stop bleeding spontaneously; endoscopic treatment is reserved for actively bleeding tears or those with high-risk features. Severe forceful retching — as in Boerhaave syndrome (esophageal perforation) — produces a more severe clinical picture with mediastinal contamination and requires surgical management, though this is far less common than a Mallory-Weiss tear.
Other Important Causes — Gastritis, Dieulafoy Lesions, and Vascular Malformations
Acute erosive gastritis — diffuse mucosal inflammation and superficial erosions without a discrete ulcer — causes upper GI bleeding through oozing from multiple erosions rather than arterial hemorrhage from a single vessel. Common causes include alcohol (which directly damages gastric epithelium), NSAIDs, severe physiological stress (stress ulceration in critically ill patients — ICU patients on mechanical ventilation, major burn victims, or patients with severe head injuries), and, less commonly, bile reflux. The bleeding from erosive gastritis is usually less brisk than from a peptic ulcer, and endoscopy reveals a diffusely erythematous, friable, or erosive mucosa rather than a discrete bleeding vessel. Treatment focuses on the underlying cause — alcohol cessation, stopping NSAIDs, stress ulcer prophylaxis in at-risk ICU patients — alongside acid suppression with PPIs.
Dieulafoy lesions — an abnormally large submucosal artery that intermittently erodes through the overlying mucosa without forming an ulcer — are an uncommon but important cause of recurrent, massive upper GI bleeding that can be diagnostically elusive. Because the artery bleeds episodically and the overlying mucosa is otherwise normal in appearance, Dieulafoy lesions may be missed on a first endoscopy if they are not actively bleeding at the time. They most commonly occur in the proximal stomach within six centimeters of the gastroesophageal junction. Endoscopic identification during an active bleeding episode allows definitive treatment with injection, thermal coagulation, or hemoclip placement; over-the-scope clips are particularly effective for these lesions. Angiographic embolization is an alternative for lesions that cannot be identified or controlled endoscopically.
What to Do When Someone Vomits Blood — Emergency Response
Vomiting blood requires emergency evaluation — call emergency services (911 in the US) or go directly to an emergency department without delay. While waiting for help or transport: lay the person on their side (recovery position) to prevent aspiration of blood; do not give anything to eat or drink; and monitor breathing and consciousness. The priority in the emergency department is simultaneous resuscitation and risk stratification — large-bore intravenous access, blood typing and crossmatching, complete blood count, coagulation tests, liver function tests, and urea/creatinine measurement. The urea-to-creatinine ratio is elevated in upper GI bleeding because blood protein is digested and absorbed as urea — this distinguishes upper from lower GI bleeding when the source is not immediately obvious.
Blood transfusion thresholds in upper GI bleeding have been refined by clinical trial evidence: a restrictive transfusion strategy targeting a hemoglobin threshold of 7 g/dL (rather than the traditional 10 g/dL) has been shown to improve outcomes in patients with upper GI bleeding, partly because overtransfusion increases portal pressure and may worsen variceal bleeding. Intravenous PPI therapy — typically a bolus of esomeprazole or pantoprazole followed by continuous infusion — is started empirically before endoscopy in suspected peptic ulcer bleeding to reduce gastric acid exposure and stabilize clots on bleeding vessels, improving endoscopic conditions and reducing the need for endoscopic intervention. For suspected variceal bleeding, terlipressin or octreotide is started immediately to reduce portal pressure, alongside antibiotics and careful fluid resuscitation to avoid volume overload that worsens portal hypertension.
Upper endoscopy should be performed within twenty-four hours of presentation for most upper GI bleeding patients and within twelve hours for those with high-risk features (hemodynamic instability, active hematemesis, known varices, or a high Glasgow-Blatchford score). Endoscopy simultaneously diagnoses the cause of bleeding and allows immediate therapeutic intervention — injection, thermal therapy, or mechanical hemostasis for ulcers; band ligation or glue injection for varices. The endoscopic finding guides further management: high-risk ulcer stigmata (active bleeding, visible vessel, or adherent clot) require inpatient observation and continued PPI therapy; low-risk findings (clean ulcer base, flat pigmented spot) allow early discharge and oral PPI continuation. Patients with cirrhosis and variceal bleeding require ICU-level care, and discharge planning must include enrollment in secondary prophylaxis programs. Post-bleeding management also involves addressing risk factors for recurrence — H. pylori eradication, cessation of NSAIDs, and optimization of anticoagulation if anticoagulants contributed.
Frequently Asked Questions About Vomiting Blood
Is all vomited blood life-threatening?
Not necessarily, but all hematemesis requires emergency evaluation because the degree of danger cannot be reliably assessed without endoscopy. Small amounts of bright red blood after forceful vomiting may represent a Mallory-Weiss tear, which often stops bleeding spontaneously. Coffee-ground material from a small, slowly oozing gastric erosion may reflect a self-limited process. However, the only way to distinguish these lower-risk scenarios from life-threatening variceal hemorrhage or a bleeding duodenal ulcer — both of which can escalate rapidly — is through clinical assessment and endoscopy in an appropriate medical setting. Delaying evaluation because the initial volume seems small is a dangerous approach.
How is vomiting blood different from coughing blood?
Hematemesis (vomiting blood) originates from the upper gastrointestinal tract (esophagus, stomach, duodenum) and the blood is expelled by vomiting — it may be mixed with food material and may have a coffee-ground appearance from acid digestion. Hemoptysis (coughing blood) originates from the lower respiratory tract (lungs, bronchi) and the blood is expelled by coughing — it is typically bright red and frothy, mixed with sputum rather than food, and accompanied by respiratory symptoms such as cough, breathlessness, or chest pain. The distinction matters clinically because the causes, investigations, and treatments are completely different. In cases of uncertainty, a history of the exact mechanism of expulsion and the presence or absence of respiratory symptoms usually allows reliable differentiation.
Can alcohol cause vomiting blood even without cirrhosis?
Yes. Alcohol can cause vomiting of blood through several mechanisms that do not require cirrhosis: direct toxic injury to the gastric mucosa causing erosive gastritis or hemorrhagic gastritis; Mallory-Weiss tears from violent retching; and peptic ulcer disease exacerbated by alcohol’s effect on gastric acid secretion and mucosal protection. In patients with alcohol-related liver disease or cirrhosis, variceal hemorrhage is an additional risk. Even in a person without known liver disease, vomiting blood after heavy alcohol use should not be attributed to “just alcohol” without medical evaluation — it represents a gastrointestinal emergency requiring proper diagnosis regardless of the surrounding alcohol context.
Sources: NIDDK — GI Bleeding · ACG — Upper GI Bleeding · Mayo Clinic — Vomiting Blood
Rebleeding Risk and Long-Term Management After Upper GI Bleeding
The risk of rebleeding after an episode of upper gastrointestinal bleeding is a central concern in post-acute management. For peptic ulcer bleeding, the risk of rebleeding within thirty days is approximately twenty percent without secondary prevention — reduced to approximately five percent with high-dose PPI therapy and H. pylori eradication (when applicable). Patients who rebleed after successful initial endoscopic hemostasis should undergo repeat endoscopy before proceeding to angiographic embolization or surgery, as endoscopy successfully controls rebleeding in approximately seventy-five percent of cases. In the small proportion of patients who fail both endoscopic and angiographic approaches, surgical gastrotomy with vessel ligation remains a lifesaving option.
For variceal bleeding, rebleeding rates without secondary prophylaxis approach sixty to seventy percent within one year — reflecting the underlying portal hypertension that drives the condition. Secondary prophylaxis with non-selective beta-blockers (propranolol, carvedilol, or nadolol) combined with regular endoscopic band ligation sessions every two to four weeks until variceal obliteration is the standard post-bleeding regimen. Patients who develop refractory variceal bleeding or who are poor candidates for repeated endoscopy should be evaluated for TIPS — which is more effective than pharmacological and endoscopic secondary prophylaxis at preventing rebleeding. The assessment of all variceal bleed survivors for liver transplantation candidacy is essential, since transplantation not only eliminates the variceal bleeding risk by resolving the portal hypertension but also treats the underlying cirrhosis responsible for multiple other complications including ascites and coagulopathy.
Angiodysplasia and Vascular Ectasias — Less Common Upper GI Bleeding Sources
Gastrointestinal angiodysplasias — small, dilated, thin-walled blood vessels in the mucosa and submucosa — are an important cause of chronic, recurrent upper and lower GI bleeding, particularly in elderly patients and those with systemic conditions including chronic kidney disease (hemodialysis patients have a particularly high prevalence), hereditary hemorrhagic telangiectasia (Osler-Weber-Rendu syndrome), and aortic stenosis (Heyde’s syndrome — a triad of aortic stenosis, angiodysplasia, and GI bleeding from acquired von Willebrand factor deficiency). Angiodysplasias may be single or multiple, often produce intermittent rather than continuous bleeding, and may be difficult to detect on endoscopy if they are not actively bleeding at the time of examination.
Gastric antral vascular ectasia (GAVE) — also called “watermelon stomach” from the characteristic endoscopic appearance of longitudinal red stripes in the gastric antrum — is a distinct vascular lesion most commonly associated with portal hypertension from cirrhosis (though it also occurs in autoimmune conditions including scleroderma). GAVE produces chronic, oozing upper GI bleeding that presents as anemia requiring repeated blood transfusions rather than acute hematemesis; it is a significant cause of transfusion-dependent anemia in cirrhotic patients. Argon plasma coagulation (APC) is the most effective endoscopic treatment for GAVE, typically requiring multiple sessions to achieve adequate lesion ablation. Unlike esophageal varices (which are driven by portal hypertension and improve with TIPS), GAVE does not reliably improve with portal pressure reduction — making endoscopic ablation rather than TIPS the appropriate treatment strategy.
Upper GI Bleeding in Patients on Anticoagulants and Antiplatelet Agents
The management of upper GI bleeding in patients taking anticoagulant or antiplatelet medications presents a clinical dilemma — the medications that caused or contributed to the bleeding are often prescribed for serious conditions (atrial fibrillation, recent myocardial infarction, mechanical heart valves, venous thromboembolism) where their cessation carries its own risks. Direct oral anticoagulants (DOACs — apixaban, rivaroxaban, dabigatran, edoxaban) are increasingly common causes of upper GI bleeding; specific reversal agents exist for dabigatran (idarucizumab) and the factor Xa inhibitors (andexanet alfa) and are used in life-threatening bleeding. Warfarin is reversed with four-factor prothrombin complex concentrate (PCC) — which provides faster and more complete reversal than fresh frozen plasma in the acute setting — with vitamin K given concurrently for sustained reversal.
After the acute bleed is controlled, the decision about when and whether to restart anticoagulation requires individualized risk-benefit analysis. For most patients with high-risk indications for anticoagulation (mechanical heart valves, atrial fibrillation with CHA₂DS₂-VASc score ≥ 2, recent venous thromboembolism), the risk of restarting anticoagulation seven to fourteen days after a successfully treated upper GI bleed is outweighed by the thrombotic risk of prolonged anticoagulant cessation. Concurrent treatment of the underlying GI lesion — H. pylori eradication, PPI therapy, and cessation of NSAIDs — reduces the risk of recurrent GI bleeding after anticoagulation is resumed. This decision should be made collaboratively between gastroenterology and the specialty managing the anticoagulation indication (cardiology, hematology, or vascular medicine), with the patient’s informed participation. The long-term prevention of gastrointestinal bleeding in patients requiring anticoagulation or antiplatelet therapy is increasingly recognized as an important component of cardiovascular risk management, alongside anticoagulant dose optimization, gastroprotective PPI co-prescription, and avoidance of concomitant NSAID use.
Preventing Upper GI Bleeding — Risk Factor Management
The majority of upper GI bleeding events are preventable. H. pylori eradication dramatically reduces the incidence of peptic ulcer disease and its associated bleeding risk — population-level test-and-treat strategies for H. pylori have been shown to reduce gastric cancer incidence alongside ulcer complications in high-prevalence regions. In patients who require chronic NSAID therapy for arthritis or other conditions, co-prescription of a PPI at a standard dose reduces NSAID-related upper GI bleeding risk by approximately fifty to sixty percent; switching to a COX-2 selective inhibitor (celecoxib) where clinically appropriate provides some additional gastroprotection, though residual risk remains. The lowest effective NSAID dose for the shortest necessary duration minimizes gastrointestinal risk in patients who require these medications.
Alcohol reduction or cessation is one of the most impactful preventive measures for upper GI bleeding because it simultaneously reduces the risk of Mallory-Weiss tears, erosive gastritis, peptic ulceration, and — critically — the development of cirrhosis and portal hypertension that underlies variceal hemorrhage. Patients with established cirrhosis should undergo screening endoscopy at diagnosis to assess for varices, and those with medium to large varices should receive primary prophylaxis with non-selective beta-blockers or endoscopic band ligation to prevent a first bleed. Primary prophylaxis has been shown to reduce the risk of first variceal hemorrhage from approximately thirty percent at two years without treatment to approximately fifteen percent with treatment — a substantial and clinically meaningful reduction. Recognizing the broader landscape of upper GI symptoms that may precede bleeding — including persistent indigestion, early satiety, epigastric pain, unexplained anemia, and pale stool — and seeking timely evaluation for these symptoms creates additional opportunities to identify and treat conditions before bleeding occurs. A comprehensive approach to digestive health, including awareness of when symptoms require prompt attention, is outlined in the article on liver and digestive health warning signs.
For patients who have experienced an episode of vomiting blood and are in recovery, several follow-up priorities are important regardless of the underlying cause. Confirming H. pylori eradication with a stool antigen test or urea breath test four to eight weeks after completing antibiotics ensures that the most treatable common precipitant has been successfully addressed. Repeat endoscopy at six to eight weeks is recommended for gastric ulcers to confirm healing and, critically, to obtain biopsies from any residual ulcer to exclude gastric malignancy — which can present as a benign-appearing ulcer on initial endoscopy. Patients with cirrhosis who have survived variceal bleeding should attend regular follow-up for assessment of liver function, monitoring of MELD score, and transplantation evaluation, since the development of variceal hemorrhage substantially worsens prognosis and accelerates the timeline for transplant consideration. Iron deficiency anemia — a common consequence of GI blood loss — should be treated with oral iron supplementation and monitored to resolution, with repeat endoscopy if anemia recurs or fails to correct despite adequate iron supplementation. A structured approach to post-bleeding follow-up — combining H. pylori eradication confirmation, ulcer healing assessment, anemia treatment, and risk factor modification — substantially reduces the risk of recurrence and prevents the most serious outcomes of upper gastrointestinal bleeding in the long term.
Upper gastrointestinal bleeding, while frightening, is one of the digestive emergencies with the most clearly established and effective treatment pathways. From rapid risk stratification to targeted endoscopic hemostasis to post-procedure secondary prevention, the management of hematemesis has been transformed over the past three decades by advances in endoscopic technology, pharmacology, and intensive care. A patient who reaches a hospital quickly, receives appropriate resuscitation and early endoscopy, and follows the recommended secondary prevention regimen has a high probability of surviving the acute episode without recurrence — outcomes that depend critically on prompt recognition of the symptom, timely activation of emergency services, and access to a center with twenty-four-hour endoscopy capability. Awareness of the warning signs that distinguish upper GI bleeding from less serious symptoms — bright red or coffee-ground vomit, black tarry stools, dizziness, and syncope — and the willingness to act immediately on those signs remain the most powerful determinants of outcome at the patient level.