Men who have sex with men, especially with HIV co-infection
Post-Treatment Monitoring: What Comes After?
Monitoring after treatment differs significantly depending on which infection — and the degree of liver damage — is involved.
For hepatitis B, monitoring is lifelong regardless of whether treatment is initiated. Patients not meeting treatment criteria require regular surveillance (typically 6–12 monthly HBV DNA and liver function tests) for transitions to more active phases. Patients on treatment require monitoring for drug efficacy and resistance. HCC surveillance (6-monthly ultrasound) is recommended for all patients with cirrhosis, and for HBsAg-positive patients with additional HCC risk factors (age, family history, high viral load, HBeAg positivity) even without cirrhosis. FibroScan assessments track fibrosis over time.
For hepatitis C, a confirmed SVR12 result effectively ends the specialist monitoring requirement for most patients without advanced fibrosis — they can be discharged from hepatology. The exception is patients with established cirrhosis (F4) or advanced fibrosis (F3), who require ongoing 6-monthly HCC surveillance even after viral cure, because the cirrhotic liver retains elevated HCC risk despite HCV elimination. Patients with ongoing HCV exposure risk (e.g., continued injection drug use) require periodic HCV RNA retesting for reinfection.
Frequently Asked Questions
Which is more serious — hepatitis B or hepatitis C?
Both can cause serious liver disease, cirrhosis, and liver cancer, but they differ in their treatability. Hepatitis C is curable with a short course of direct-acting antivirals, meaning the long-term liver complications can be entirely prevented if HCV is diagnosed and treated early. Hepatitis B cannot currently be cured — treatment suppresses viral activity but must be continued indefinitely, and long-term monitoring is always required. In terms of global burden, HBV causes more deaths than HCV annually (884,000 versus 399,000 per WHO 2019 estimates), partly due to HCC risk and partly due to the greater number of people affected. However, for any individual diagnosed with HCV, the immediate treatment priority is compelling — cure is achievable and the window is open at any fibrosis stage.
If I’m vaccinated against hepatitis B, am I also protected against hepatitis C?
No. The hepatitis B vaccine provides no protection against hepatitis C. They are completely different viruses requiring separate prevention strategies. HCV has no vaccine, so prevention relies on avoiding exposure through blood-to-blood contact. Having received the HBV vaccine does not reduce your HCV risk in any way, and vice versa.
Can hepatitis B turn into hepatitis C?
No. HBV and HCV are entirely different viruses — hepatitis B cannot transform into or cause hepatitis C. They are transmitted independently and cause separate infections. A person can have both at the same time (co-infection), which does worsen liver disease outcomes, but this occurs through separate transmission events, not through one infection “turning into” the other.
Does curing hepatitis C also treat hepatitis B?
No — and importantly, treating hepatitis C with direct-acting antivirals can actually trigger hepatitis B reactivation in patients with past HBV infection. The FDA and other regulatory bodies have issued warnings about this. Before starting DAA therapy for HCV, all patients should be tested for HBsAg and anti-HBc to assess HBV status. Patients with active HBV will need concurrent antiviral prophylaxis or treatment during HCV DAA therapy to prevent reactivation.
Do both hepatitis B and C show symptoms?
Both infections are typically asymptomatic in the early and middle stages of chronic infection — which is why both require active screening rather than symptom-based diagnosis. Acute hepatitis B symptoms (fatigue, jaundice, abdominal pain, nausea) occur in around 30–50% of adults with acute HBV, and are more commonly recognised than acute HCV (which is symptomatic in only 15–20% of cases). In chronic infection, both can cause fatigue and right upper quadrant discomfort, and both can cause significant liver damage with no symptoms until cirrhosis develops. Neither infection should be dismissed because “I don’t feel sick.”
Is there a combined test for both hepatitis B and C?
Yes — many clinical settings offer combined hepatitis B and C screening panels, and WHO-approved rapid diagnostic tests (RDTs) that test for both HBsAg (hepatitis B) and anti-HCV (hepatitis C) simultaneously from a single fingerprick blood sample are increasingly available, particularly in community and harm reduction settings. If you are asking your GP or sexual health clinic for hepatitis testing, ask specifically for both HBV and HCV to be included — in some settings these are ordered separately and one may be omitted if not explicitly requested.
After curing hepatitis C, should I get the hepatitis B vaccine?
If you are not immune to hepatitis B (anti-HBs negative, anti-HBc negative — meaning no past exposure and no vaccination), then yes — hepatitis B vaccination is recommended regardless of your HCV status. Recovering from HCV does not confer any protection against HBV. Given the ongoing liver vulnerability in a post-HCV liver (especially if any fibrosis has developed), preventing a second hepatotropic viral infection is an important additional liver health measure. Check your HBV immunity status with your clinician at the time of HCV assessment or after SVR.
The Shared Outcome: Why Both Matter
Despite their biological, epidemiological, and therapeutic differences, hepatitis B and hepatitis C converge in their long-term consequence: both are major causes of liver cirrhosis, liver failure, and liver cancer, and both remain massively underdiagnosed globally. Together, they account for approximately 1.1 million deaths per year — the vast majority of which are preventable either through vaccination (HBV), treatment (HCV), or both.
The global health argument for action on both is clear. For HBV: universal infant vaccination, completion of catch-up programmes in unvaccinated adults, and engagement of the hundreds of millions with chronic HBV into monitoring and treatment programmes. For HCV: expanding access to testing and the existing cure — a cure that achieves over 95% success rates and is already proven, available, and awaiting delivery to the millions who have not yet been found. Understanding the differences between these two infections is not just academic — it defines which intervention applies, and knowing that can mean the difference between early diagnosis and decades of unrecognised liver damage.
Have You Been Tested?
If you have risk factors for either hepatitis B or C — or have simply never been tested — speak to your GP. Both infections are diagnosed with a blood test. HBV is preventable with a vaccine. HCV is curable with an 8–12 week course of tablets. Knowing your status is the first and most important step.
Medical Disclaimer: This article is for educational purposes only and does not substitute for personalised medical advice. Testing, vaccination, and treatment decisions for hepatitis B or C should be made in consultation with a qualified clinician who can assess your individual risk factors, medical history, and current medications.
Men who have sex with men, especially with HIV co-infection
Post-Treatment Monitoring: What Comes After?
Monitoring after treatment differs significantly depending on which infection — and the degree of liver damage — is involved.
For hepatitis B, monitoring is lifelong regardless of whether treatment is initiated. Patients not meeting treatment criteria require regular surveillance (typically 6–12 monthly HBV DNA and liver function tests) for transitions to more active phases. Patients on treatment require monitoring for drug efficacy and resistance. HCC surveillance (6-monthly ultrasound) is recommended for all patients with cirrhosis, and for HBsAg-positive patients with additional HCC risk factors (age, family history, high viral load, HBeAg positivity) even without cirrhosis. FibroScan assessments track fibrosis over time.
For hepatitis C, a confirmed SVR12 result effectively ends the specialist monitoring requirement for most patients without advanced fibrosis — they can be discharged from hepatology. The exception is patients with established cirrhosis (F4) or advanced fibrosis (F3), who require ongoing 6-monthly HCC surveillance even after viral cure, because the cirrhotic liver retains elevated HCC risk despite HCV elimination. Patients with ongoing HCV exposure risk (e.g., continued injection drug use) require periodic HCV RNA retesting for reinfection.
Frequently Asked Questions
Which is more serious — hepatitis B or hepatitis C?
Both can cause serious liver disease, cirrhosis, and liver cancer, but they differ in their treatability. Hepatitis C is curable with a short course of direct-acting antivirals, meaning the long-term liver complications can be entirely prevented if HCV is diagnosed and treated early. Hepatitis B cannot currently be cured — treatment suppresses viral activity but must be continued indefinitely, and long-term monitoring is always required. In terms of global burden, HBV causes more deaths than HCV annually (884,000 versus 399,000 per WHO 2019 estimates), partly due to HCC risk and partly due to the greater number of people affected. However, for any individual diagnosed with HCV, the immediate treatment priority is compelling — cure is achievable and the window is open at any fibrosis stage.
If I’m vaccinated against hepatitis B, am I also protected against hepatitis C?
No. The hepatitis B vaccine provides no protection against hepatitis C. They are completely different viruses requiring separate prevention strategies. HCV has no vaccine, so prevention relies on avoiding exposure through blood-to-blood contact. Having received the HBV vaccine does not reduce your HCV risk in any way, and vice versa.
Can hepatitis B turn into hepatitis C?
No. HBV and HCV are entirely different viruses — hepatitis B cannot transform into or cause hepatitis C. They are transmitted independently and cause separate infections. A person can have both at the same time (co-infection), which does worsen liver disease outcomes, but this occurs through separate transmission events, not through one infection “turning into” the other.
Does curing hepatitis C also treat hepatitis B?
No — and importantly, treating hepatitis C with direct-acting antivirals can actually trigger hepatitis B reactivation in patients with past HBV infection. The FDA and other regulatory bodies have issued warnings about this. Before starting DAA therapy for HCV, all patients should be tested for HBsAg and anti-HBc to assess HBV status. Patients with active HBV will need concurrent antiviral prophylaxis or treatment during HCV DAA therapy to prevent reactivation.
Do both hepatitis B and C show symptoms?
Both infections are typically asymptomatic in the early and middle stages of chronic infection — which is why both require active screening rather than symptom-based diagnosis. Acute hepatitis B symptoms (fatigue, jaundice, abdominal pain, nausea) occur in around 30–50% of adults with acute HBV, and are more commonly recognised than acute HCV (which is symptomatic in only 15–20% of cases). In chronic infection, both can cause fatigue and right upper quadrant discomfort, and both can cause significant liver damage with no symptoms until cirrhosis develops. Neither infection should be dismissed because “I don’t feel sick.”
Is there a combined test for both hepatitis B and C?
Yes — many clinical settings offer combined hepatitis B and C screening panels, and WHO-approved rapid diagnostic tests (RDTs) that test for both HBsAg (hepatitis B) and anti-HCV (hepatitis C) simultaneously from a single fingerprick blood sample are increasingly available, particularly in community and harm reduction settings. If you are asking your GP or sexual health clinic for hepatitis testing, ask specifically for both HBV and HCV to be included — in some settings these are ordered separately and one may be omitted if not explicitly requested.
After curing hepatitis C, should I get the hepatitis B vaccine?
If you are not immune to hepatitis B (anti-HBs negative, anti-HBc negative — meaning no past exposure and no vaccination), then yes — hepatitis B vaccination is recommended regardless of your HCV status. Recovering from HCV does not confer any protection against HBV. Given the ongoing liver vulnerability in a post-HCV liver (especially if any fibrosis has developed), preventing a second hepatotropic viral infection is an important additional liver health measure. Check your HBV immunity status with your clinician at the time of HCV assessment or after SVR.
The Shared Outcome: Why Both Matter
Despite their biological, epidemiological, and therapeutic differences, hepatitis B and hepatitis C converge in their long-term consequence: both are major causes of liver cirrhosis, liver failure, and liver cancer, and both remain massively underdiagnosed globally. Together, they account for approximately 1.1 million deaths per year — the vast majority of which are preventable either through vaccination (HBV), treatment (HCV), or both.
The global health argument for action on both is clear. For HBV: universal infant vaccination, completion of catch-up programmes in unvaccinated adults, and engagement of the hundreds of millions with chronic HBV into monitoring and treatment programmes. For HCV: expanding access to testing and the existing cure — a cure that achieves over 95% success rates and is already proven, available, and awaiting delivery to the millions who have not yet been found. Understanding the differences between these two infections is not just academic — it defines which intervention applies, and knowing that can mean the difference between early diagnosis and decades of unrecognised liver damage.
Have You Been Tested?
If you have risk factors for either hepatitis B or C — or have simply never been tested — speak to your GP. Both infections are diagnosed with a blood test. HBV is preventable with a vaccine. HCV is curable with an 8–12 week course of tablets. Knowing your status is the first and most important step.
Medical Disclaimer: This article is for educational purposes only and does not substitute for personalised medical advice. Testing, vaccination, and treatment decisions for hepatitis B or C should be made in consultation with a qualified clinician who can assess your individual risk factors, medical history, and current medications.
Hepatitis B and hepatitis C are both bloodborne viral liver infections — but they differ fundamentally in their virology, transmission routes, available prevention, and treatment outcomes. HBV has a vaccine but no cure; HCV has a cure but no vaccine.
Hepatitis B vs Hepatitis C: Key Differences Explained
Hepatitis B and hepatitis C are the two most common causes of chronic viral liver disease worldwide, together affecting an estimated 354 million people globally. Both are bloodborne viruses that can cause progressive liver damage, cirrhosis, and hepatocellular carcinoma (HCC) — and both are dramatically underdiagnosed. Yet despite these similarities, hepatitis B (HBV) and hepatitis C (HCV) are fundamentally different viruses, with distinct biology, transmission risks, prevention strategies, and treatment outcomes. Understanding the differences matters both for individual health decisions — knowing who needs testing, vaccination, or treatment — and for understanding the global liver health landscape.
The headline contrast: hepatitis B has a highly effective vaccine but no cure; hepatitis C has a cure (direct-acting antivirals that eliminate the virus in over 95% of patients) but no vaccine. This single sentence captures the essential asymmetry between the two infections and explains why global control strategies differ — one depends primarily on prevention through immunisation, the other depends on testing and treating as many people as possible.
296Mpeople with chronic HBV globally
58Mpeople with chronic HCV globally
VaccineHBV: yes (95% effective) — HCV: none
CureHBV: no functional cure — HCV: >95% SVR rate
The Viruses: How HBV and HCV Differ Biologically
The biological differences between HBV and HCV explain many of the clinical contrasts between the two infections, including why one is curable and the other is not.
Hepatitis B virus (HBV) is a partially double-stranded DNA virus belonging to the Hepadnaviridae family. Its most clinically significant feature is its ability to establish a persistent intranuclear reservoir in infected hepatocytes in the form of covalently closed circular DNA (cccDNA). cccDNA acts as a template for viral transcription that is not targeted by current antiviral drugs — it persists in the nucleus of infected liver cells indefinitely, explaining why HBV cannot currently be cured with antivirals alone. Even when HBV surface antigen (HBsAg) becomes undetectable and the infection appears resolved clinically, cccDNA remains in hepatocytes and can reactivate under immunosuppression. HBV has ten genotypes (A through J), though genotype does not substantially alter clinical management in the current therapeutic landscape.
Hepatitis C virus (HCV) is a single-stranded RNA virus belonging to the Flaviviridae family. Unlike HBV, HCV does not integrate into the host genome and does not establish a nuclear DNA reservoir. It replicates as an RNA virus in the cytoplasm of hepatocytes, and when antiviral therapy eliminates HCV RNA from the circulation, there is no persistent reservoir to drive relapse — this is why direct-acting antivirals can achieve functional cure. HCV exists in six major genotypes (1–6), with genotype 1 predominating in Western countries. HCV’s high replication rate and error-prone RNA polymerase generate significant genetic diversity, which has complicated vaccine development but does not prevent antiviral cure.
Transmission: Similarities and Differences
Both HBV and HCV are bloodborne viruses, but the efficiency of transmission by different routes differs significantly between them — a distinction with important implications for who is at risk and what precautions matter.
Route
Hepatitis B (HBV)
Hepatitis C (HCV)
Blood-to-blood (e.g. injection drug use)
High risk — efficient transmission via shared needles/equipment
High risk — primary route of new HCV infections in high-income countries
Sexual transmission
Efficient — HBV is 50–100x more infectious than HIV sexually; main route in low-prevalence countries
Low efficiency in heterosexual relationships (<1%/year); higher risk in MSM with HIV co-infection
Perinatal (mother to child)
High risk without prophylaxis (~90% if HBeAg positive) — effectively prevented by birth-dose vaccine + HBIG
~5% risk — no approved prophylaxis; treat mother before pregnancy if possible
Household contact
Possible via shared razors, toothbrushes, or other blood-contaminated items; also via close contact in early childhood
The key practical takeaway: HBV is substantially more infectious than HCV by the sexual route, making it the predominant infection in sexual health and perinatal contexts. HCV is the predominant infection among people who inject drugs in high-income countries. Both are transmitted through healthcare settings with inadequate infection control, and both were spread through blood transfusions before systematic screening was introduced in the early 1990s.
Prevention: The Vaccine Asymmetry
One of the most clinically significant differences between HBV and HCV is the availability — and absence — of vaccines.
Hepatitis B vaccine is one of the most effective vaccines in clinical use, achieving protective antibody levels (anti-HBs ≥10 mIU/mL) in over 95% of healthy adults and over 98% of infants. Universal infant vaccination programmes, now in place in most countries, have reduced HBV prevalence dramatically in vaccinated cohorts. The birth-dose vaccine, given within 24 hours of delivery alongside hepatitis B immunoglobulin (HBIG) for infants of HBsAg-positive mothers, prevents over 90% of perinatal transmission. Adults who have not been vaccinated should receive catch-up vaccination — three doses over six months, or two doses of HEPLISAV-B (available in the US) over one month.
Hepatitis C vaccine does not currently exist. Despite decades of research, developing an HCV vaccine has proven extremely challenging due to the virus’s extraordinary genetic diversity, its ability to evolve rapidly under immune pressure, and the absence of broadly neutralising antibodies after natural infection (most people who clear HCV spontaneously do not develop lasting protective immunity). Prevention of HCV therefore relies on harm reduction (sterile needle programmes, opioid agonist therapy), infection control in healthcare settings, and treatment of infected individuals to eliminate transmission — which is why the WHO’s HCV elimination strategy centres on testing and treating rather than vaccination.
Hepatitis B and C share similar long-term complications — fibrosis, cirrhosis, and liver cancer — but differ in transmission efficiency, prevention strategies, and treatment outcomes. Understanding the distinctions helps patients and clinicians identify the right screening and management approach.
Natural History: How Each Infection Progresses
Both HBV and HCV can establish chronic infections that silently damage the liver over decades, but their natural histories differ in important ways.
Hepatitis B natural history is determined significantly by the age at which infection occurs. Adults infected with HBV clear the infection spontaneously in approximately 90–95% of cases — only 5–10% develop chronic infection. By contrast, infants infected at birth (perinatal transmission) develop chronic infection in 90% of cases, and children infected in early childhood (ages 1–5) have a 25–50% risk of chronicity. This age-at-infection pattern reflects immature immune function in early life and explains why HBV burden is so heavily concentrated in regions where perinatal transmission is common (particularly sub-Saharan Africa and East Asia). Chronic HBV progresses through defined phases (immune tolerant, immune active, immune control, reactivation), with the risk of cirrhosis and HCC determined by cumulative inflammation and viral activity over decades.
Hepatitis C natural history follows a different pattern: regardless of age at infection, 75–85% of acute HCV infections progress to chronic infection. Spontaneous clearance of HCV (which occurs in 15–25% of cases) is more common in women, in those with certain immune gene variants, and in acute symptomatic infections. Chronic HCV progresses more slowly than chronic HBV in terms of the timeline to cirrhosis, but the absence of immune-mediated phases means the fibrosis trajectory, while variable, does not have the same periods of relative quiescence seen in HBV’s immune tolerant phase. Key accelerators of fibrosis progression in both infections include alcohol use, obesity, HIV co-infection, age, and male sex.
Both infections carry substantial risk of hepatocellular carcinoma (HCC) once cirrhosis develops. In HBV, HCC risk is higher than in HCV-related cirrhosis, and HCC can occur in HBV patients without cirrhosis (through direct oncogenic mechanisms related to HBV DNA integration into the host genome) — which is why HCC surveillance in HBV is initiated based on viral and fibrosis markers rather than cirrhosis alone. In HCV, HCC risk is primarily confined to patients with F3–F4 fibrosis, though it does not return to zero after HCV is cured in patients with established cirrhosis.
Testing: How to Diagnose Each Infection
The testing pathways for HBV and HCV share some structural similarities — both use serological markers as the initial screen — but differ significantly in what the tests mean and how results are interpreted.
Hepatitis B testing uses a panel of serological markers: HBsAg (surface antigen — positive in active infection); anti-HBs (surface antibody — positive after vaccination or recovery); anti-HBc IgM (core antibody IgM — positive in acute HBV); anti-HBc IgG (core antibody IgG — positive in past or current infection). Initial screening typically uses HBsAg. If positive, further tests include HBeAg/anti-HBe (to assess viral replication phase), HBV DNA (viral load), and liver function tests and FibroScan for liver staging. A full description of the HBV testing pathway is available in the hepatitis B guide.
Hepatitis C testing uses a two-step pathway: anti-HCV antibody (screening — positive if exposed to HCV at any point, including cleared infections) followed by HCV RNA NAAT (confirms active current infection). The critical distinction: a positive anti-HCV antibody does not mean active infection, only past exposure. Only a positive HCV RNA confirms active HCV. People who have been cured of HCV after DAA treatment will have a positive anti-HCV antibody for life but a negative HCV RNA — they do not need re-treatment. The full testing pathway for HCV is explained in the hepatitis C guide.
Quick Testing Guide
HBV screen: HBsAg blood test — ask your GP
HCV screen: Anti-HCV antibody blood test → if positive, HCV RNA to confirm active infection
Both: Recommended for anyone with risk factors; US guidelines recommend one-time HCV testing for all adults 18–79
Both negative + not vaccinated for HBV: Get the HBV vaccine series
Treatment: The Fundamental Difference
Treatment is where HBV and HCV diverge most dramatically, and understanding this difference is central to appreciating why global liver health strategies for the two infections look so different.
Hepatitis B treatment suppresses viral replication and reduces liver damage but does not eliminate the virus. The goal of treatment is to maintain HBV DNA suppression (ideally to undetectable levels) using oral nucleotide/nucleoside analogues — tenofovir disoproxil fumarate (TDF), tenofovir alafenamide (TAF), or entecavir. These antivirals are highly effective at suppressing HBV replication and dramatically reduce the risk of cirrhosis progression and HCC, but they must be taken indefinitely for most patients because stopping therapy leads to viral rebound. Functional cure — defined as sustained HBsAg loss after a finite treatment course — occurs spontaneously in only around 1% of patients per year of treatment and remains a rare outcome. HBsAg loss is the treatment milestone analogous to HCV cure, but for most patients it remains an aspiration rather than an achievable goal with current therapies. This is why novel therapies targeting HBV cccDNA (CAMs, RNAi, therapeutic vaccines) are under active investigation.
Hepatitis C treatment is curative. Direct-acting antivirals (DAAs) — particularly the pangenotypic regimens sofosbuvir/velpatasvir (Epclusa) and glecaprevir/pibrentasvir (Mavyret) — achieve sustained virological response (SVR12, equivalent to cure) in over 95% of patients. Treatment duration is 8–12 weeks. After SVR12, there is no viral reservoir to drive relapse — the cure is durable. The transformation in HCV treatment since 2014 is one of the most dramatic therapeutic advances in modern medicine: where interferon-based regimens once required 48 weeks of injections with severe side effects and 40–80% success rates, modern DAA regimens are 8–12 weeks of well-tolerated tablets with >95% success rates across all genotypes.
Sofosbuvir/velpatasvir or glecaprevir/pibrentasvir (8–12 weeks)
Transmission efficiency (sexual)
High (50–100x more infectious than HIV sexually)
Low in heterosexual couples (<1%/year)
Perinatal transmission
~90% without prophylaxis (HBeAg+ mothers)
~5%
Spontaneous clearance of acute infection
~90–95% in adults; ~5–10% become chronic
~15–25%; 75–85% become chronic
HCC risk without cirrhosis
Yes — HBV DNA integration enables direct oncogenesis
Rare — HCC risk primarily linked to cirrhosis
Global burden
~296 million chronic infections
~58 million chronic infections
Co-infection possible
Yes — HBV and HCV can co-exist
Yes — HBV and HCV can co-exist
Can You Have Both Hepatitis B and Hepatitis C?
Yes. HBV-HCV co-infection is a recognised clinical entity, more common than might be expected given the overlap in risk populations. People who inject drugs and those in regions with high HBV endemicity are at elevated risk of dual infection. HBV-HCV co-infection has several important clinical implications:
Accelerated liver disease progression: Dual infection is associated with faster fibrosis progression, higher HCC incidence, and worse prognosis than either infection alone. The two viruses appear to have complex interactions — one typically dominates replication at a given time, and the dominant virus can shift over time.
DAA treatment can trigger HBV reactivation: One of the most important clinical discoveries since pangenotypic DAA therapy became widespread is that treating HCV in patients with past HBV infection (HBsAg-negative, anti-HBc-positive — meaning HBV has been cleared but cccDNA persists) can cause HBV reactivation. When HCV is eliminated by DAAs, the immune suppression that HCV exerts on HBV replication is removed, allowing latent HBV to reactivate. Regulatory agencies in the US (FDA) and elsewhere have issued warnings about this risk. Current guidance recommends HBsAg and anti-HBc testing before initiating HCV DAA therapy, and antiviral prophylaxis for patients with active HBV infection or those at significant reactivation risk. This interaction is another reason why a comprehensive pre-treatment assessment — covering both HBV and HCV serology — is essential before starting HCV treatment.
Who Should Be Tested — and For Which?
Understanding what hepatitis is and which type affects you requires knowing which test to ask for. The risk profiles for HBV and HCV overlap significantly but are not identical. Both infections should be considered in the following groups:
Test for BOTH HBV (HBsAg) and HCV (anti-HCV + HCV RNA) in:
People who have ever injected drugs (current or past)
People born in countries with intermediate or high HBV or HCV prevalence
People living with HIV
People who have received blood transfusions or organ transplants before 1992–1993
People on haemodialysis
People with unexplained abnormal liver function tests or liver disease
People with chronic liver disease, cirrhosis, or HCC
Test primarily for HBV in:
Unvaccinated adults (test before offering vaccination — if already exposed, vaccination is not needed)
Men who have sex with men, especially with HIV co-infection
Post-Treatment Monitoring: What Comes After?
Monitoring after treatment differs significantly depending on which infection — and the degree of liver damage — is involved.
For hepatitis B, monitoring is lifelong regardless of whether treatment is initiated. Patients not meeting treatment criteria require regular surveillance (typically 6–12 monthly HBV DNA and liver function tests) for transitions to more active phases. Patients on treatment require monitoring for drug efficacy and resistance. HCC surveillance (6-monthly ultrasound) is recommended for all patients with cirrhosis, and for HBsAg-positive patients with additional HCC risk factors (age, family history, high viral load, HBeAg positivity) even without cirrhosis. FibroScan assessments track fibrosis over time.
For hepatitis C, a confirmed SVR12 result effectively ends the specialist monitoring requirement for most patients without advanced fibrosis — they can be discharged from hepatology. The exception is patients with established cirrhosis (F4) or advanced fibrosis (F3), who require ongoing 6-monthly HCC surveillance even after viral cure, because the cirrhotic liver retains elevated HCC risk despite HCV elimination. Patients with ongoing HCV exposure risk (e.g., continued injection drug use) require periodic HCV RNA retesting for reinfection.
Frequently Asked Questions
Which is more serious — hepatitis B or hepatitis C?
Both can cause serious liver disease, cirrhosis, and liver cancer, but they differ in their treatability. Hepatitis C is curable with a short course of direct-acting antivirals, meaning the long-term liver complications can be entirely prevented if HCV is diagnosed and treated early. Hepatitis B cannot currently be cured — treatment suppresses viral activity but must be continued indefinitely, and long-term monitoring is always required. In terms of global burden, HBV causes more deaths than HCV annually (884,000 versus 399,000 per WHO 2019 estimates), partly due to HCC risk and partly due to the greater number of people affected. However, for any individual diagnosed with HCV, the immediate treatment priority is compelling — cure is achievable and the window is open at any fibrosis stage.
If I’m vaccinated against hepatitis B, am I also protected against hepatitis C?
No. The hepatitis B vaccine provides no protection against hepatitis C. They are completely different viruses requiring separate prevention strategies. HCV has no vaccine, so prevention relies on avoiding exposure through blood-to-blood contact. Having received the HBV vaccine does not reduce your HCV risk in any way, and vice versa.
Can hepatitis B turn into hepatitis C?
No. HBV and HCV are entirely different viruses — hepatitis B cannot transform into or cause hepatitis C. They are transmitted independently and cause separate infections. A person can have both at the same time (co-infection), which does worsen liver disease outcomes, but this occurs through separate transmission events, not through one infection “turning into” the other.
Does curing hepatitis C also treat hepatitis B?
No — and importantly, treating hepatitis C with direct-acting antivirals can actually trigger hepatitis B reactivation in patients with past HBV infection. The FDA and other regulatory bodies have issued warnings about this. Before starting DAA therapy for HCV, all patients should be tested for HBsAg and anti-HBc to assess HBV status. Patients with active HBV will need concurrent antiviral prophylaxis or treatment during HCV DAA therapy to prevent reactivation.
Do both hepatitis B and C show symptoms?
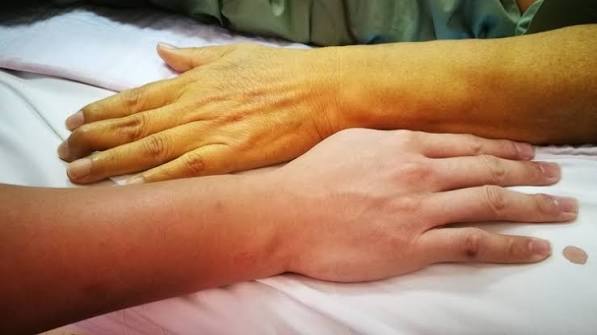
Both infections are typically asymptomatic in the early and middle stages of chronic infection — which is why both require active screening rather than symptom-based diagnosis. Acute hepatitis B symptoms (fatigue, jaundice, abdominal pain, nausea) occur in around 30–50% of adults with acute HBV, and are more commonly recognised than acute HCV (which is symptomatic in only 15–20% of cases). In chronic infection, both can cause fatigue and right upper quadrant discomfort, and both can cause significant liver damage with no symptoms until cirrhosis develops. Neither infection should be dismissed because “I don’t feel sick.”
Is there a combined test for both hepatitis B and C?
Yes — many clinical settings offer combined hepatitis B and C screening panels, and WHO-approved rapid diagnostic tests (RDTs) that test for both HBsAg (hepatitis B) and anti-HCV (hepatitis C) simultaneously from a single fingerprick blood sample are increasingly available, particularly in community and harm reduction settings. If you are asking your GP or sexual health clinic for hepatitis testing, ask specifically for both HBV and HCV to be included — in some settings these are ordered separately and one may be omitted if not explicitly requested.
After curing hepatitis C, should I get the hepatitis B vaccine?
If you are not immune to hepatitis B (anti-HBs negative, anti-HBc negative — meaning no past exposure and no vaccination), then yes — hepatitis B vaccination is recommended regardless of your HCV status. Recovering from HCV does not confer any protection against HBV. Given the ongoing liver vulnerability in a post-HCV liver (especially if any fibrosis has developed), preventing a second hepatotropic viral infection is an important additional liver health measure. Check your HBV immunity status with your clinician at the time of HCV assessment or after SVR.
The Shared Outcome: Why Both Matter
Despite their biological, epidemiological, and therapeutic differences, hepatitis B and hepatitis C converge in their long-term consequence: both are major causes of liver cirrhosis, liver failure, and liver cancer, and both remain massively underdiagnosed globally. Together, they account for approximately 1.1 million deaths per year — the vast majority of which are preventable either through vaccination (HBV), treatment (HCV), or both.
The global health argument for action on both is clear. For HBV: universal infant vaccination, completion of catch-up programmes in unvaccinated adults, and engagement of the hundreds of millions with chronic HBV into monitoring and treatment programmes. For HCV: expanding access to testing and the existing cure — a cure that achieves over 95% success rates and is already proven, available, and awaiting delivery to the millions who have not yet been found. Understanding the differences between these two infections is not just academic — it defines which intervention applies, and knowing that can mean the difference between early diagnosis and decades of unrecognised liver damage.
Have You Been Tested?
If you have risk factors for either hepatitis B or C — or have simply never been tested — speak to your GP. Both infections are diagnosed with a blood test. HBV is preventable with a vaccine. HCV is curable with an 8–12 week course of tablets. Knowing your status is the first and most important step.
Medical Disclaimer: This article is for educational purposes only and does not substitute for personalised medical advice. Testing, vaccination, and treatment decisions for hepatitis B or C should be made in consultation with a qualified clinician who can assess your individual risk factors, medical history, and current medications.
3 thoughts on “Hepatitis B vs Hepatitis C: Key Differences Explained”
David K. says:
The comparison table is brilliant. I’ve been trying to explain to my elderly parents — both of whom grew up in a country with high hepatitis prevalence — why they need to be checked for both and what the difference is between them. This article gives me exactly what I need to share with them. The point about DAA treatment for HCV potentially triggering HBV reactivation is something I had never heard before and seems really important.
Thank you for sharing that context, David. The HBV reactivation risk during HCV treatment is something that has become better understood only in the last several years as pangenotypic DAA therapy became widespread — it’s not yet universally known even among patients, which is exactly why it needs to be included in resources like this. For your parents, the key first step is that simple HBsAg blood test (for HBV) and anti-HCV antibody test (for HCV) — both from a single GP appointment. If either comes back positive there are clear pathways from there. Good luck to them.
Very useful for understanding why public health messaging for these two infections is so different. The vaccine vs cure asymmetry is something I keep trying to explain to people — I’ll be linking this article from now on.

The comparison table is brilliant. I’ve been trying to explain to my elderly parents — both of whom grew up in a country with high hepatitis prevalence — why they need to be checked for both and what the difference is between them. This article gives me exactly what I need to share with them. The point about DAA treatment for HCV potentially triggering HBV reactivation is something I had never heard before and seems really important.
Thank you for sharing that context, David. The HBV reactivation risk during HCV treatment is something that has become better understood only in the last several years as pangenotypic DAA therapy became widespread — it’s not yet universally known even among patients, which is exactly why it needs to be included in resources like this. For your parents, the key first step is that simple HBsAg blood test (for HBV) and anti-HCV antibody test (for HCV) — both from a single GP appointment. If either comes back positive there are clear pathways from there. Good luck to them.
Very useful for understanding why public health messaging for these two infections is so different. The vaccine vs cure asymmetry is something I keep trying to explain to people — I’ll be linking this article from now on.